

Lag-screw fixation
1. General considerations
Introduction
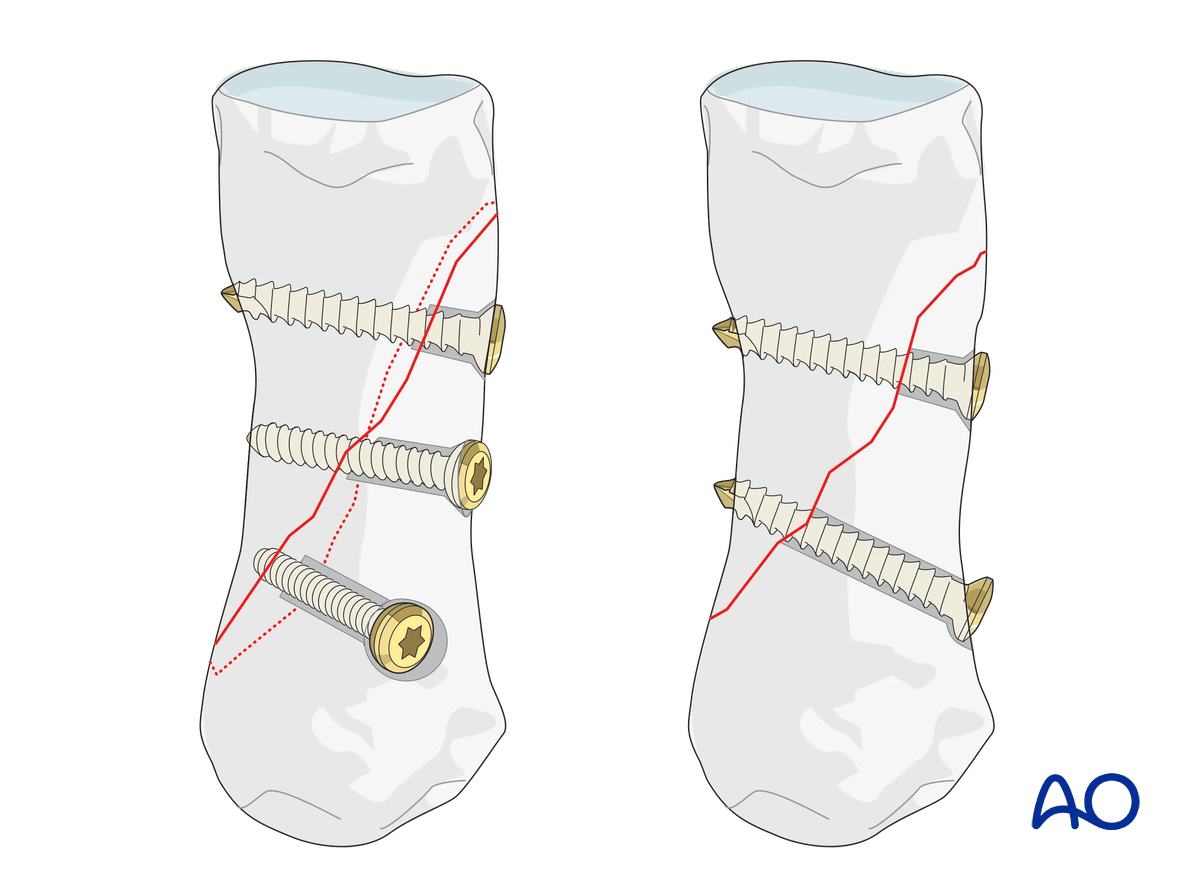
Treatment of long oblique and spiral fractures is similar. The difference is in the screw insertion in relation to the fracture plane, which is monoplanar in the long oblique fractures. In spiral fractures, the fracture plane is helical; therefore, each screw is inserted in a slightly different direction.
Indirect reduction is achieved by traction and digital manipulation. Usually, these fractures are unstable.
In a long fracture, fixation with two or more lag screws is usually sufficient, and a neutralization plate is not necessary.
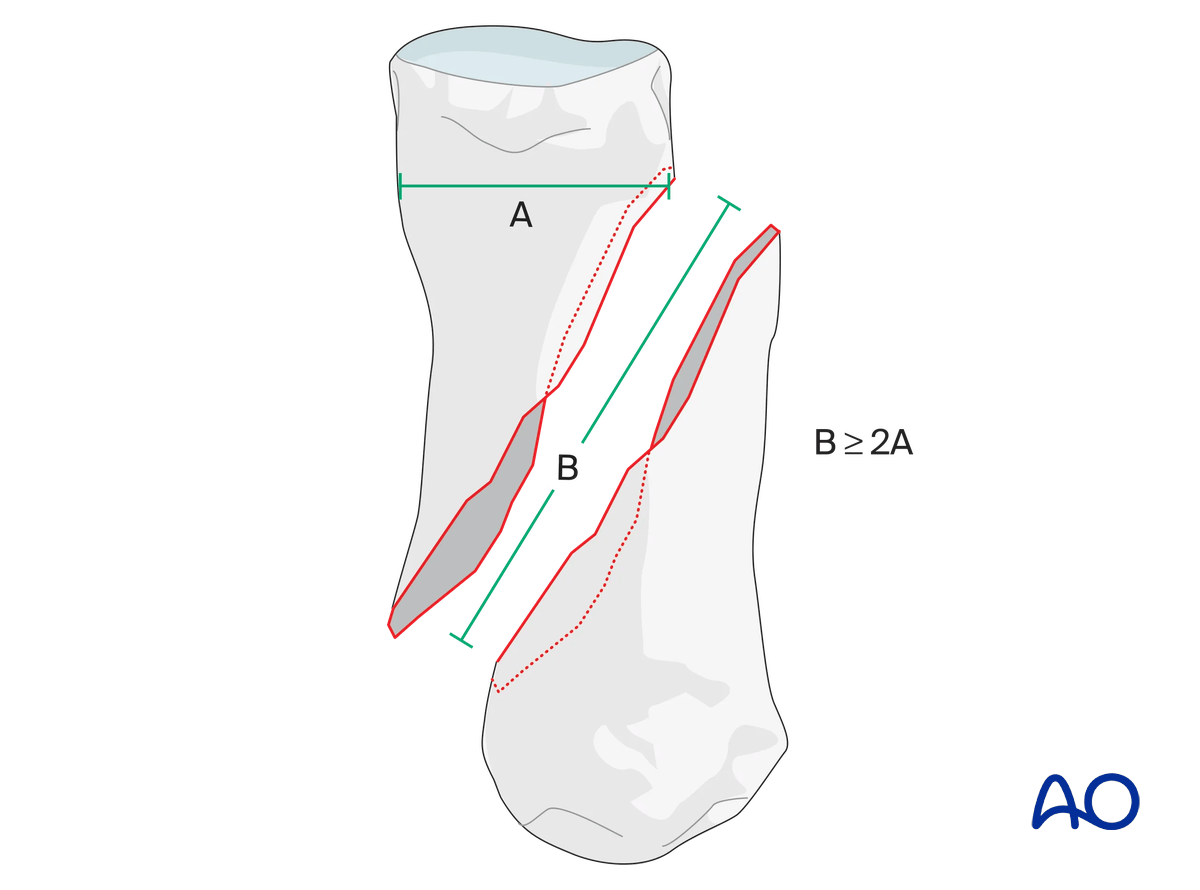
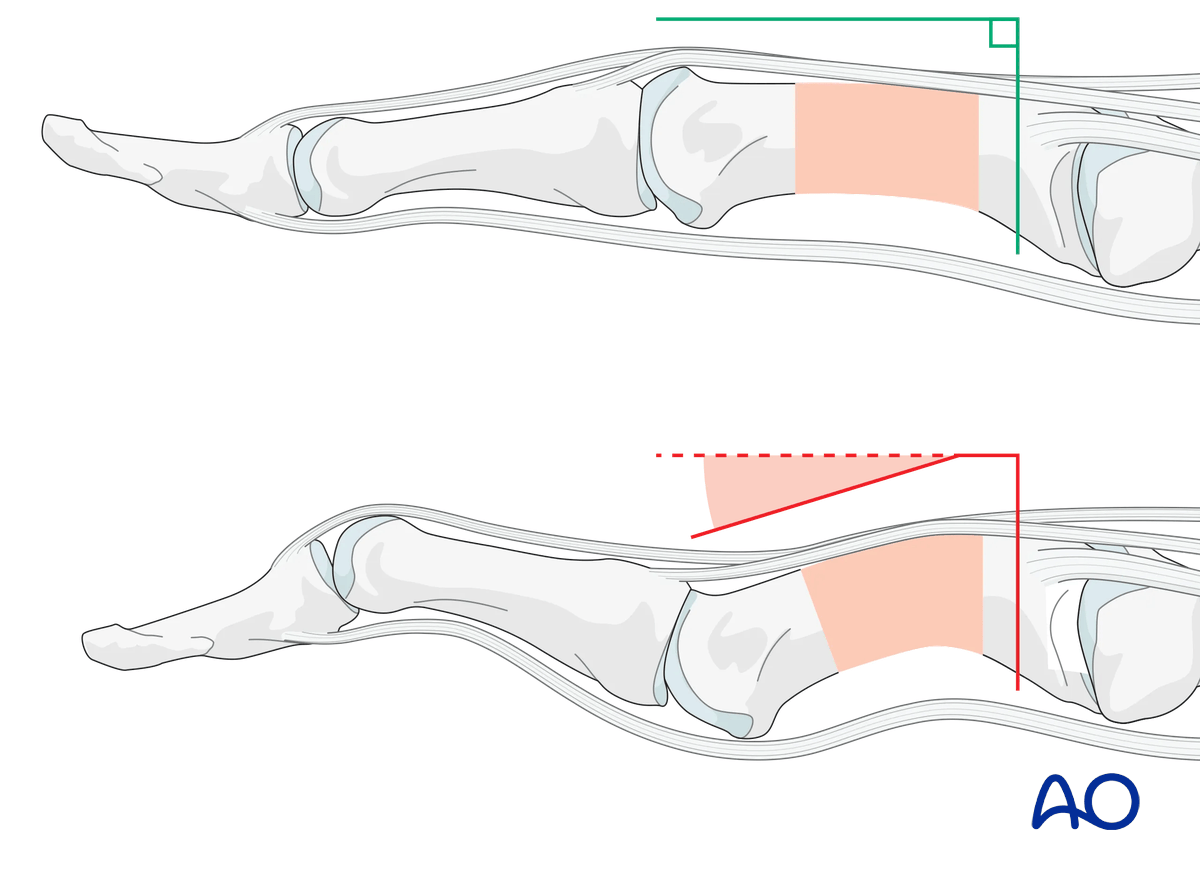
A good rule is the following: The fracture line (B) should be at least twice the length of the diameter of the metacarpal diaphysis (A), ie, B ≥ 2A for interfragmentary lag screws to provide sufficient fixation and stability.
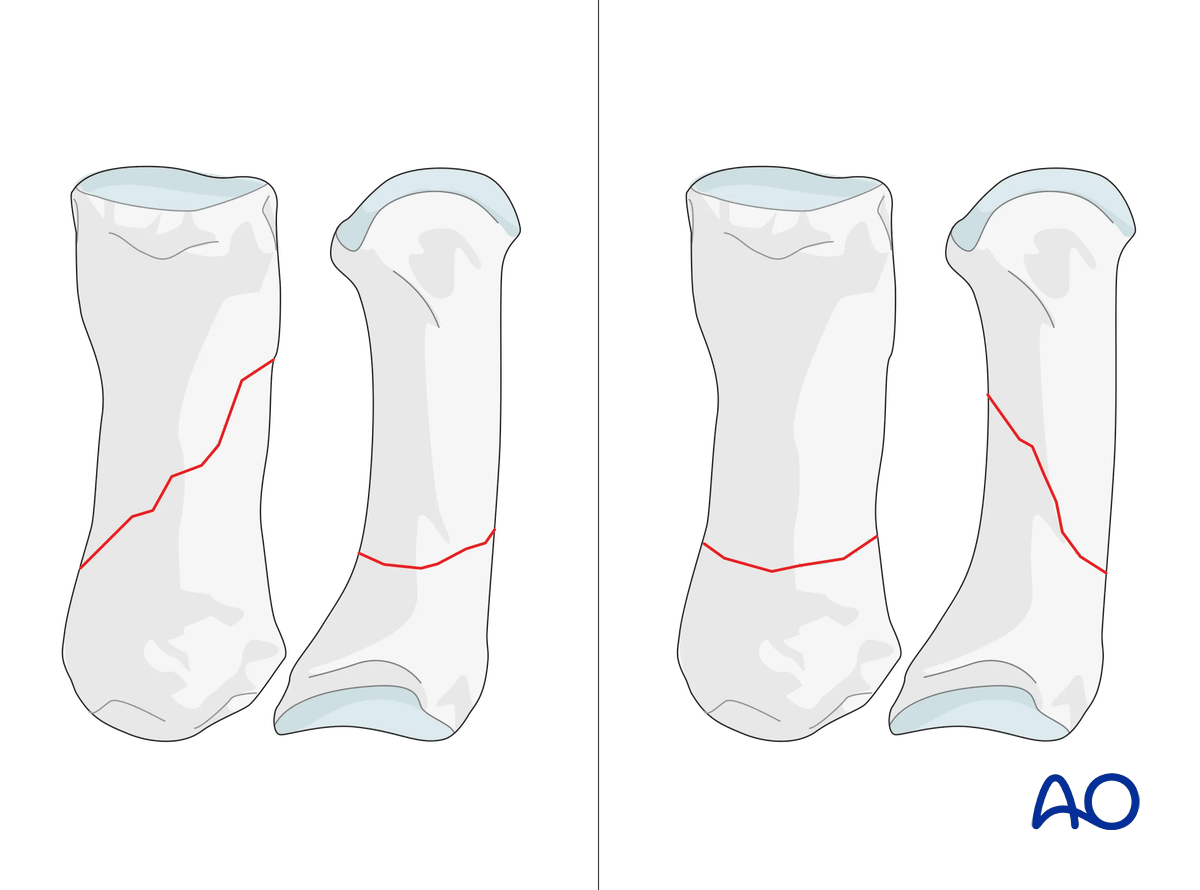
Fracture plane
Obliquity of the fracture is possible either in the plane visible in the AP view or the lateral view. Always confirm the fracture configuration with views in both planes.
2. Patient preparation
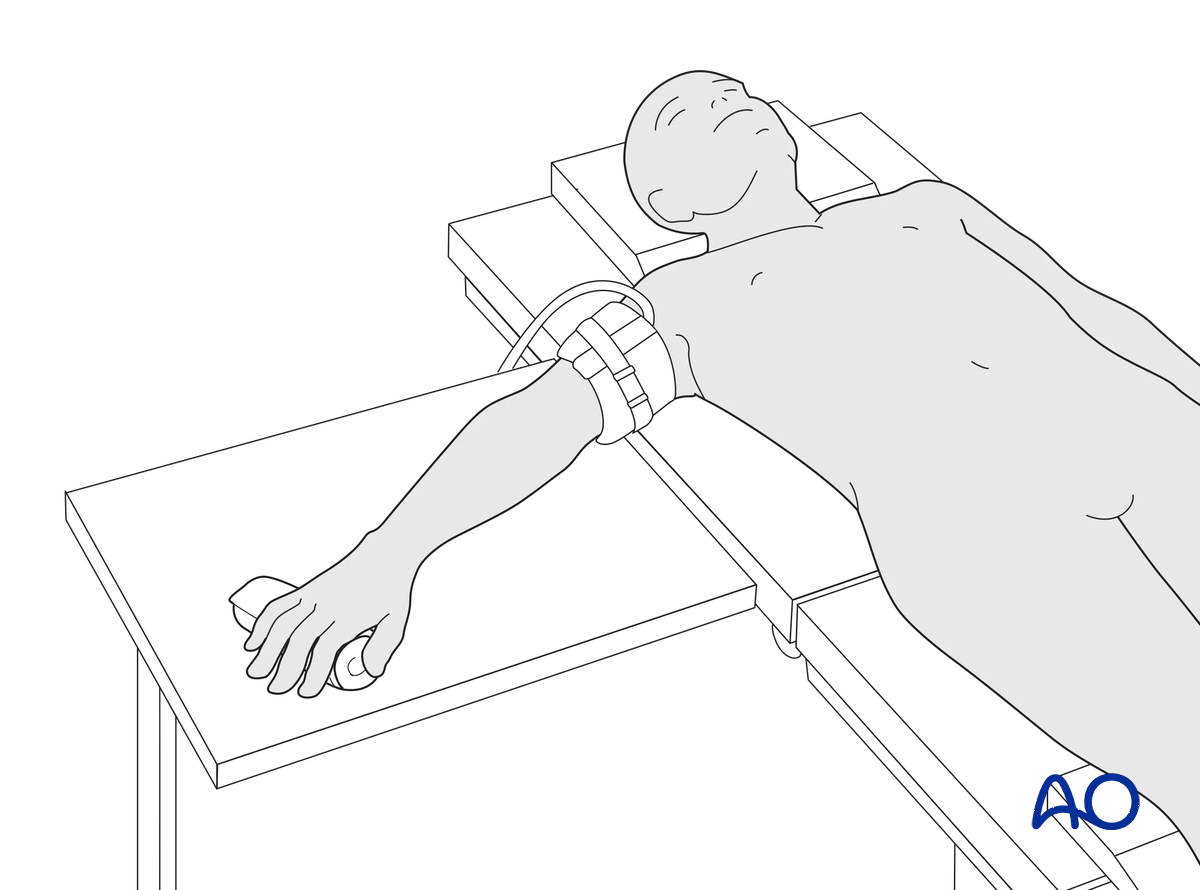
This procedure is usually performed with the patient in a supine position with the arm on a radiolucent side table.
3. Approach
For this procedure, the following approach may be used:
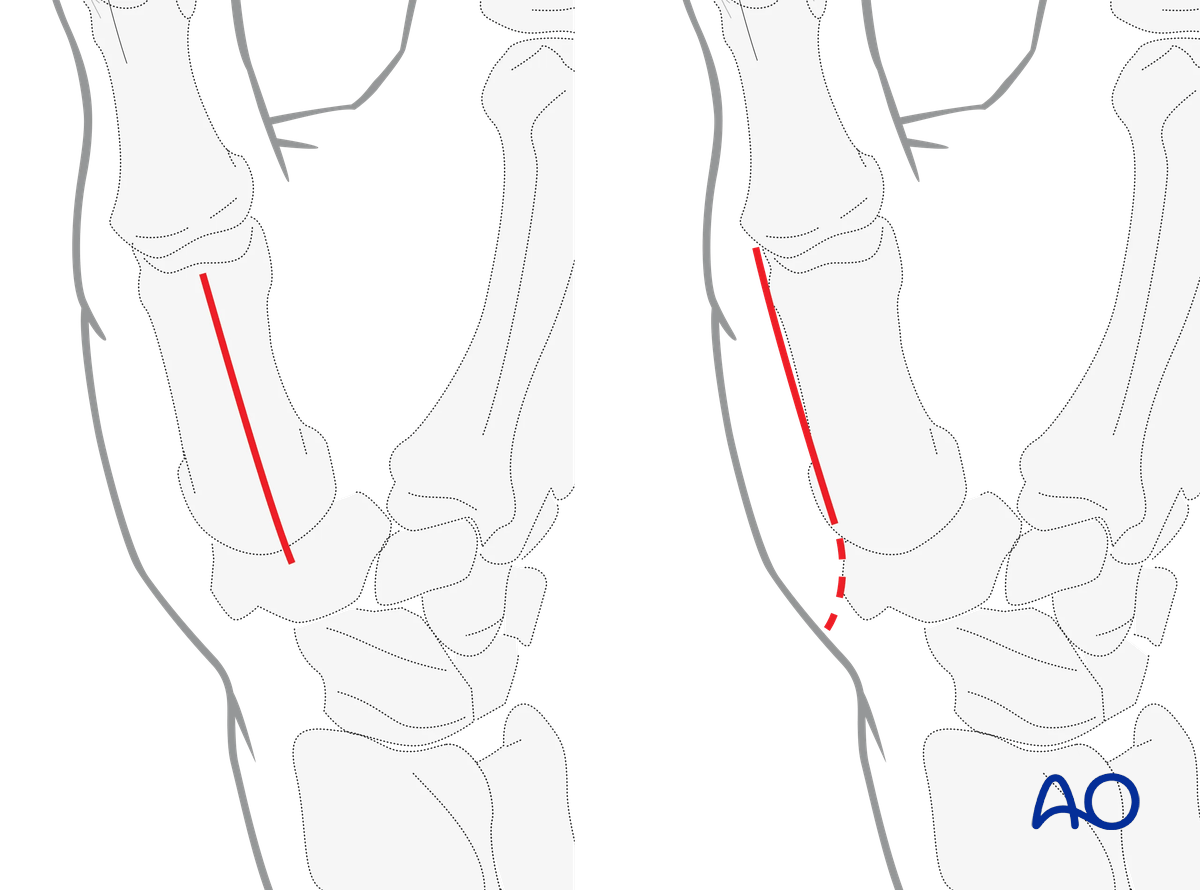
4. Reduction
Any axial displacement should be reduced to gain full length of the metacarpal.
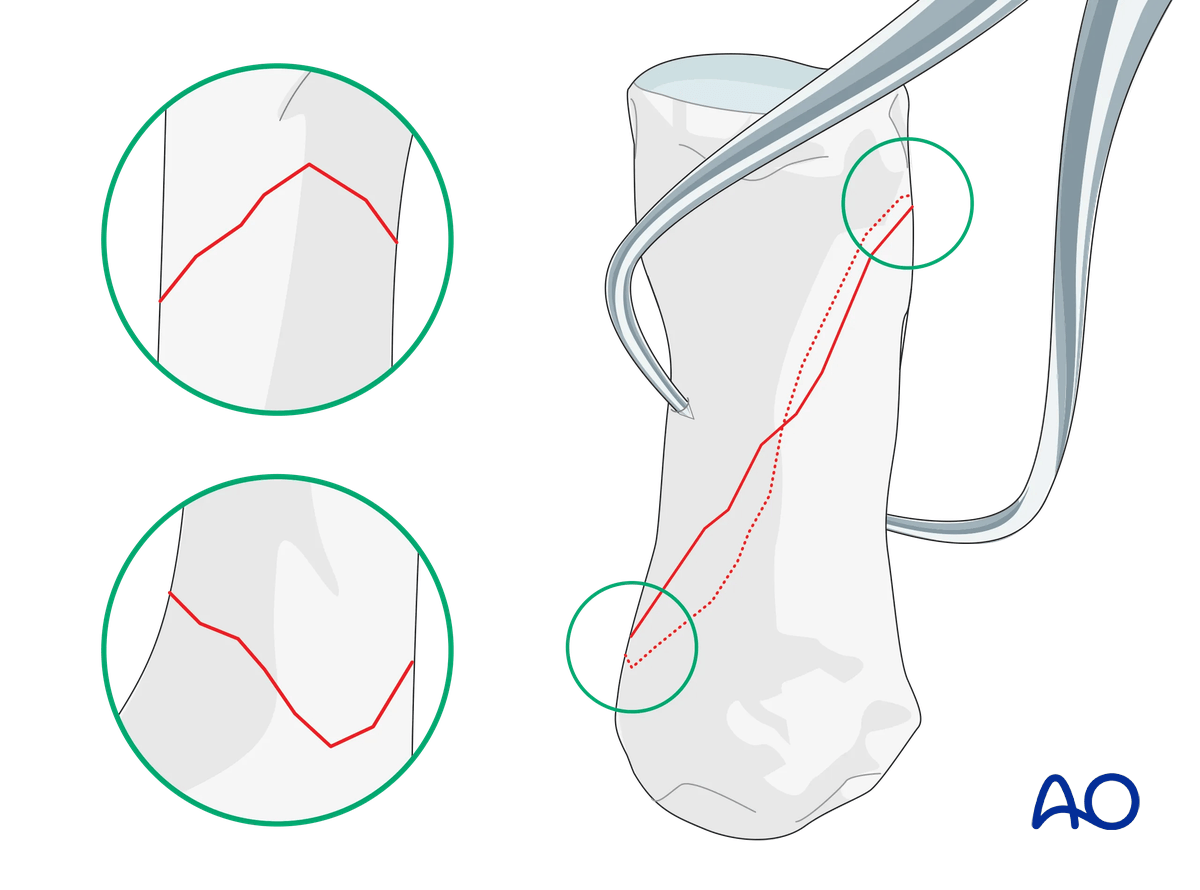
Visualizing the fracture
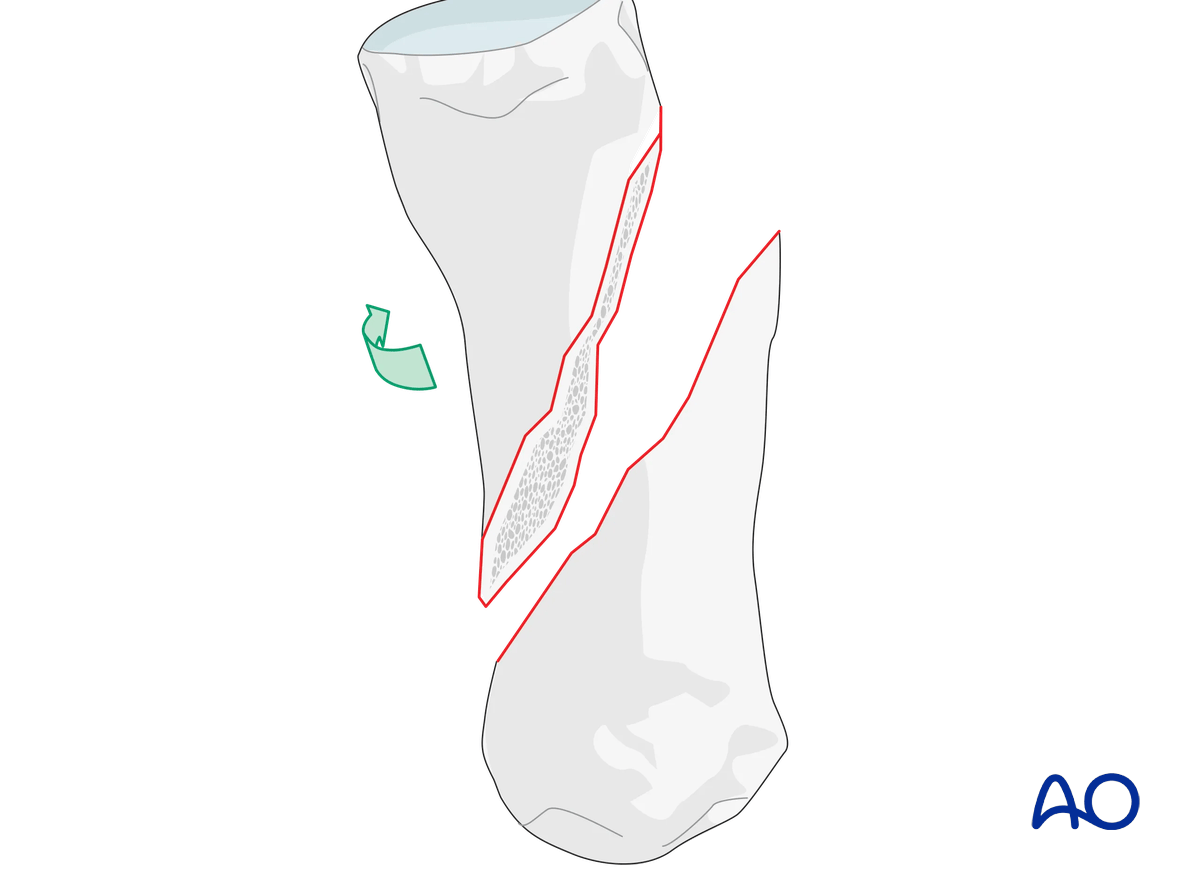
Rotate the finger and open the fracture for good direct visualization.
Determine the exact geometry of the fracture. This is very important for later screw placement.
Indirect reduction by traction
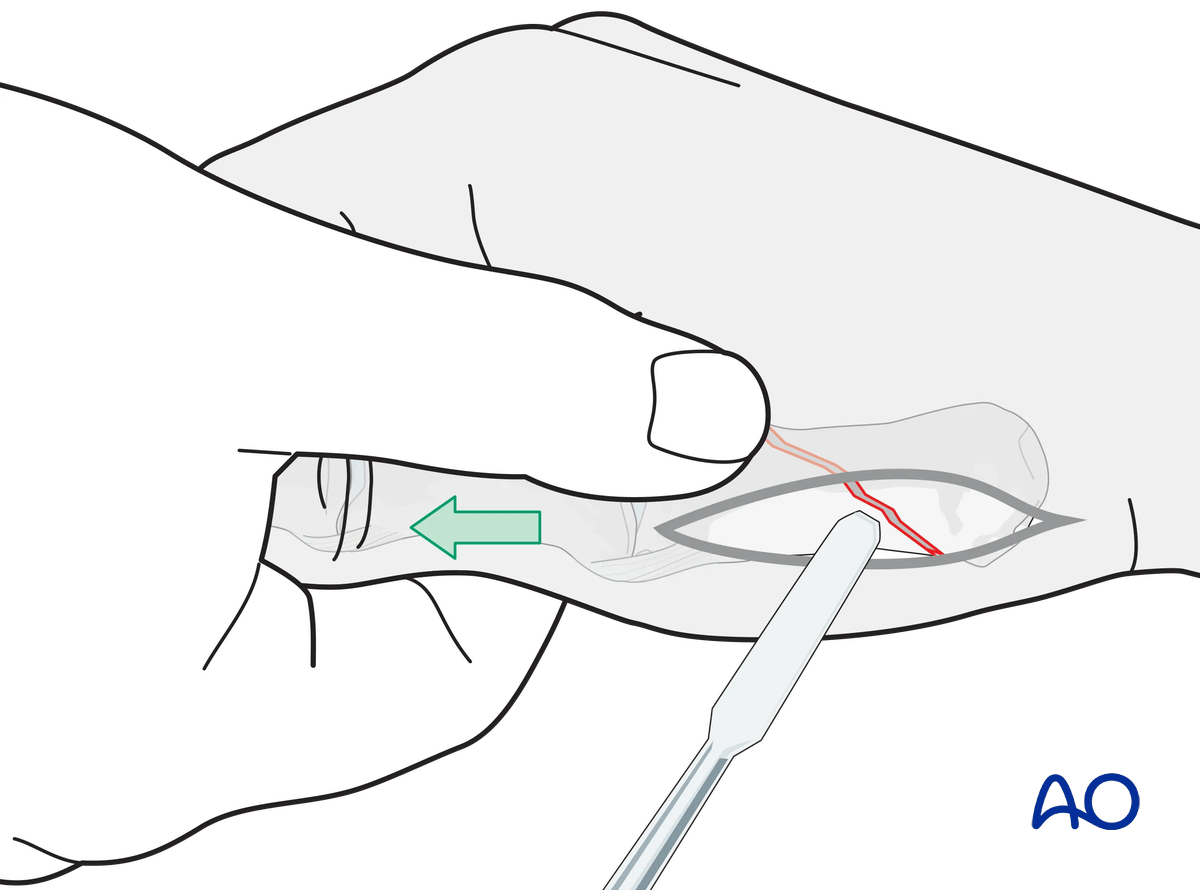
An assistant exerts traction while the surgeon reduces the fracture using pressure from a periosteal elevator or a dental pick.
Direct reduction
Gently use pointed reduction forceps to reduce the fracture anatomically.
Confirm reduction visually and with an image intensifier.
It is mandatory to confirm that the apex of each fracture fragment has been properly reduced; otherwise, malrotation may result.
Preliminary fixation
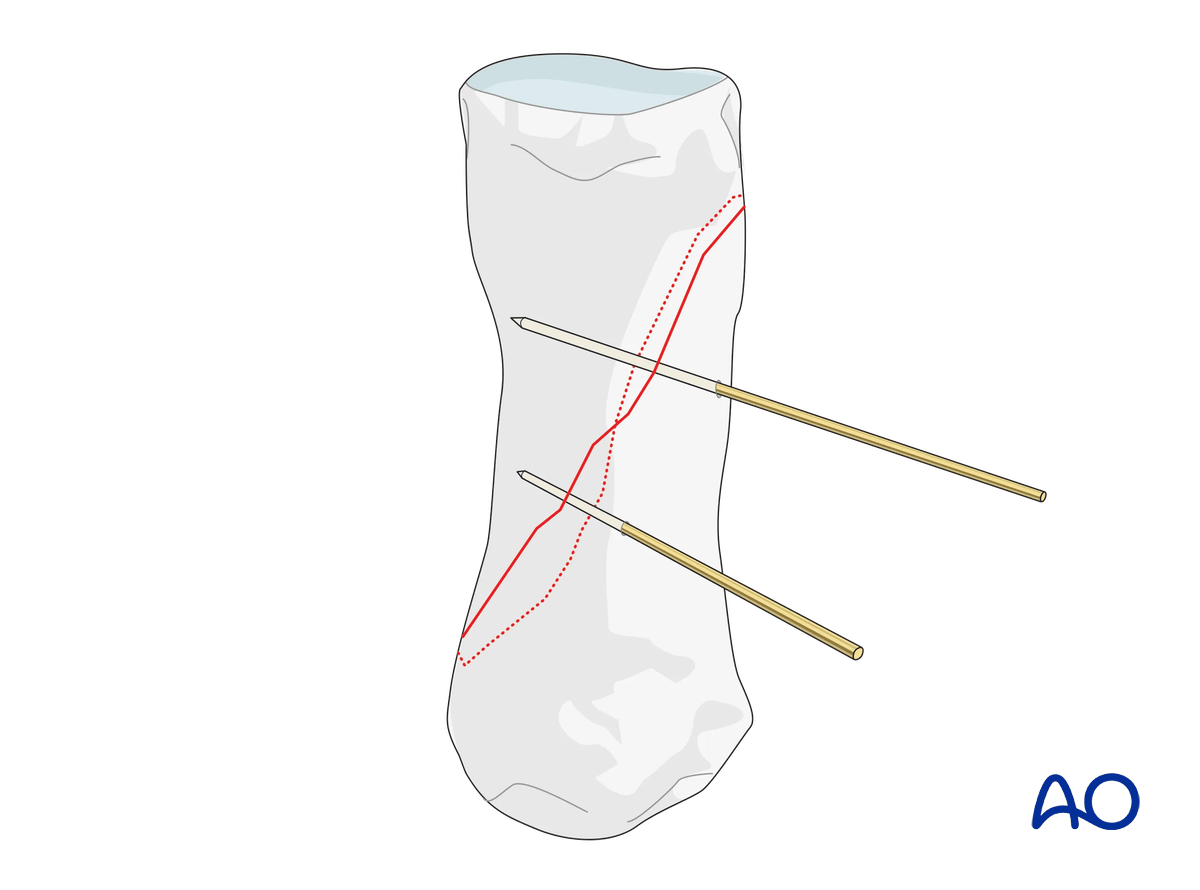
Provisionally hold the reduction with either two K-wires or one K-wire and reduction forceps. Be careful to place them in such a way that they will not conflict with later screw placement.
5. Checking alignment
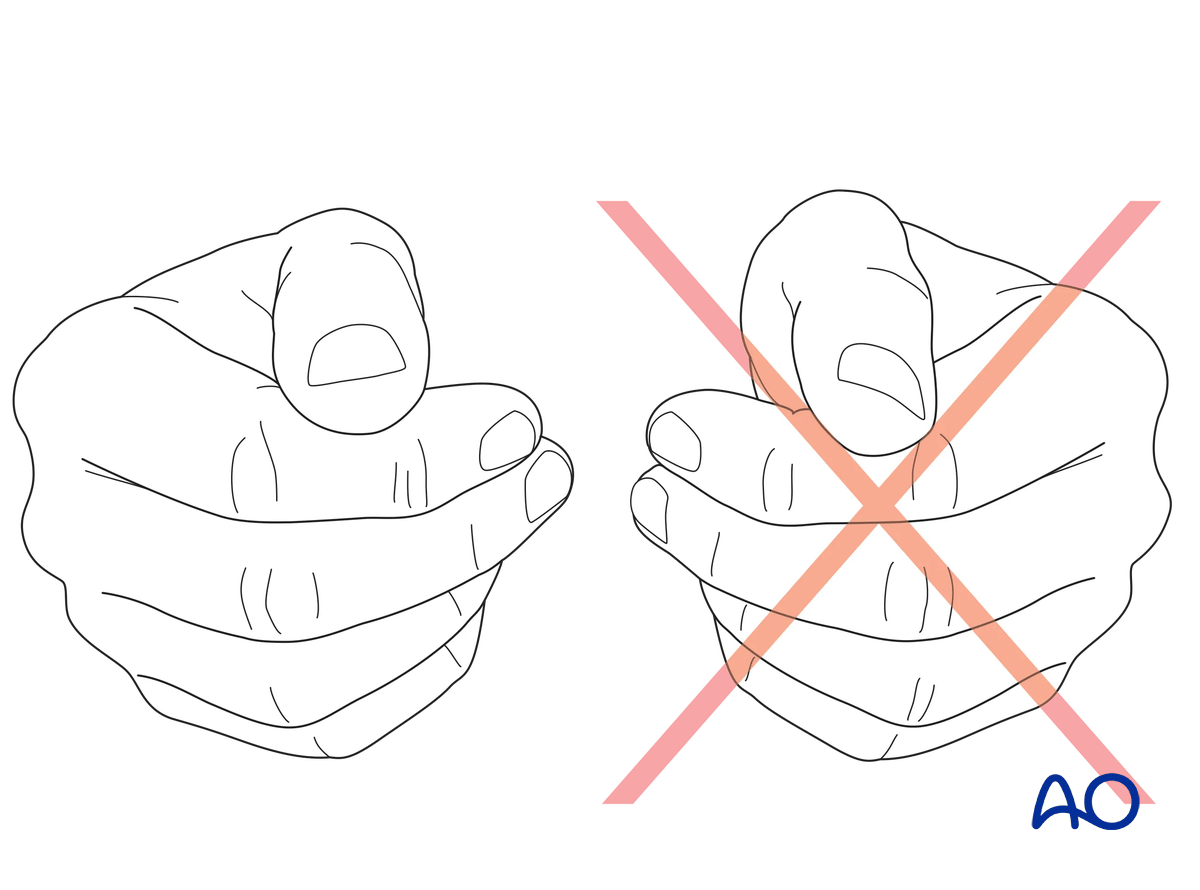
Confirm correct rotational reduction by inspecting the thumb nail plate in relation to the index finger. Compare it to the contralateral side if necessary.
6. Screw fixation
Each lag screw must be inserted perpendicularly to the fracture plane.
In spiral fractures, the result is that the screws follow a helical disposition.
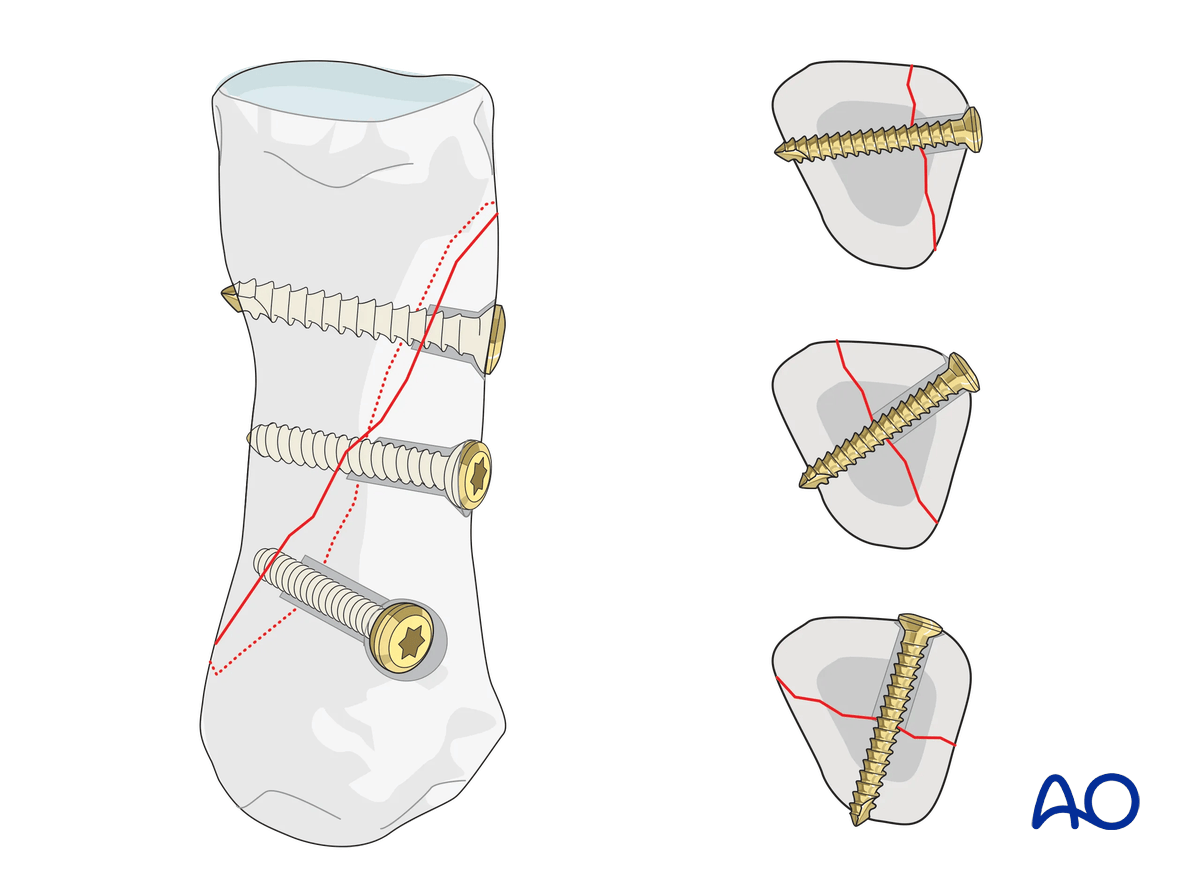
If the fracture length permits, insert three lag screws. Generally, they should be inserted at equal intervals.
Start with inserting the middle screw.
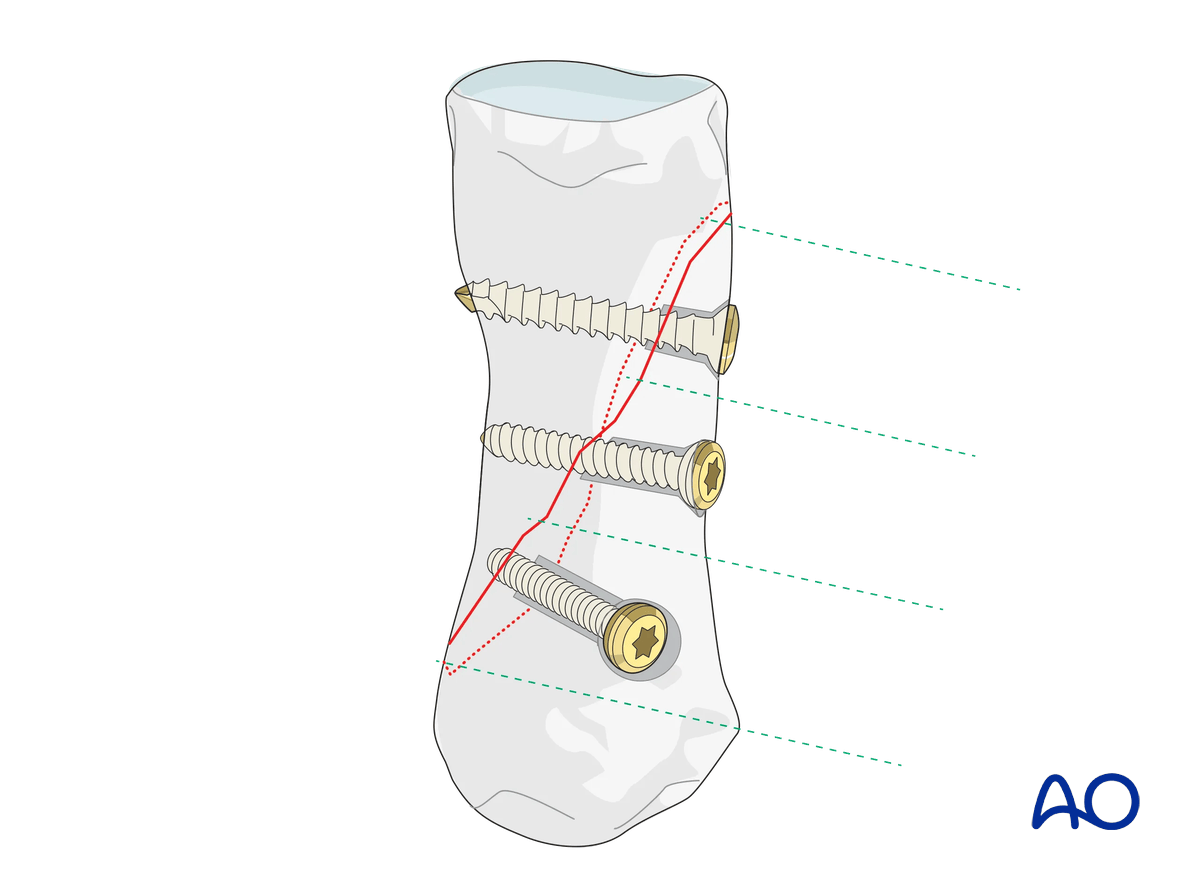
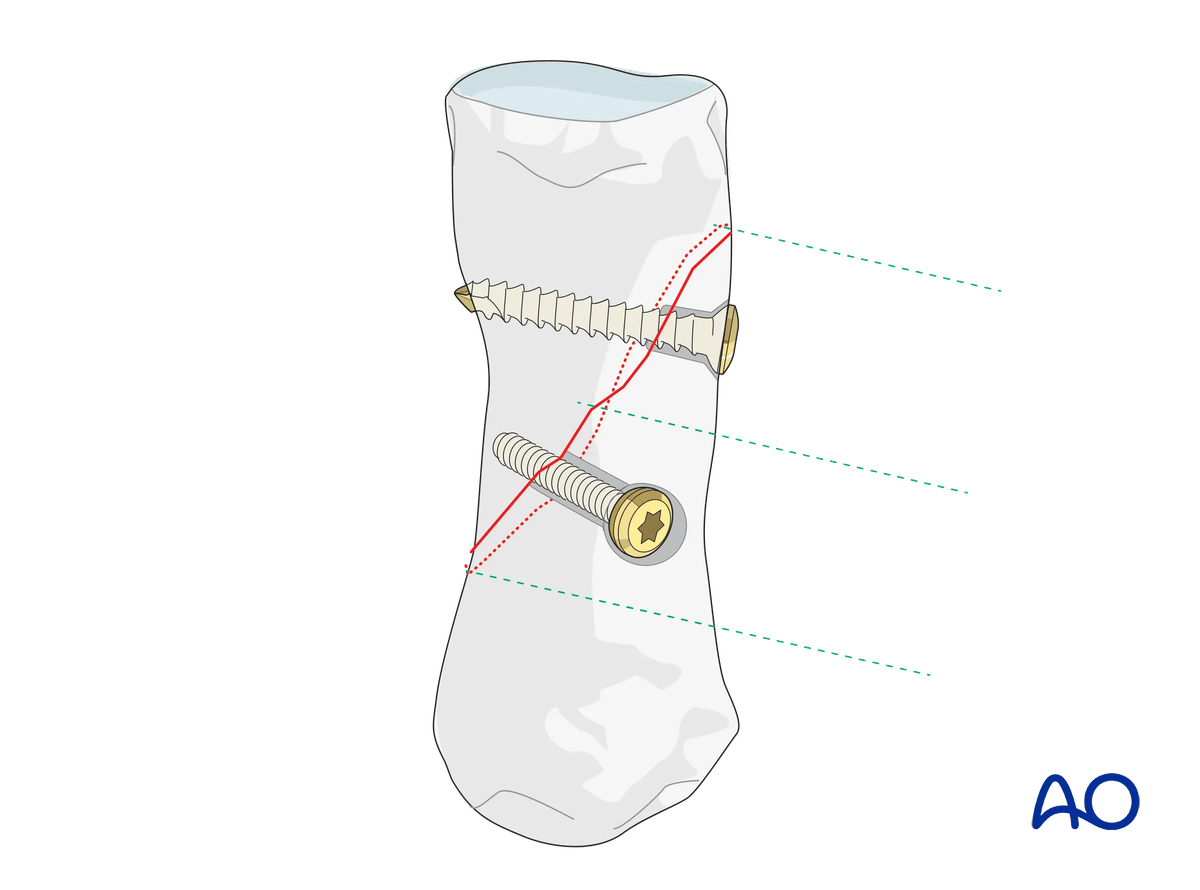
If the fragment is too short to allow for the insertion of three screws, use two screws, but recognize that this is a less stable construct. If in doubt, add a neutralization plate.
Insert both screws before fully tightening them.
Insert them as perpendicularly to the fracture plane as possible, either in an antegrade or retrograde fashion.
Screw-size selection
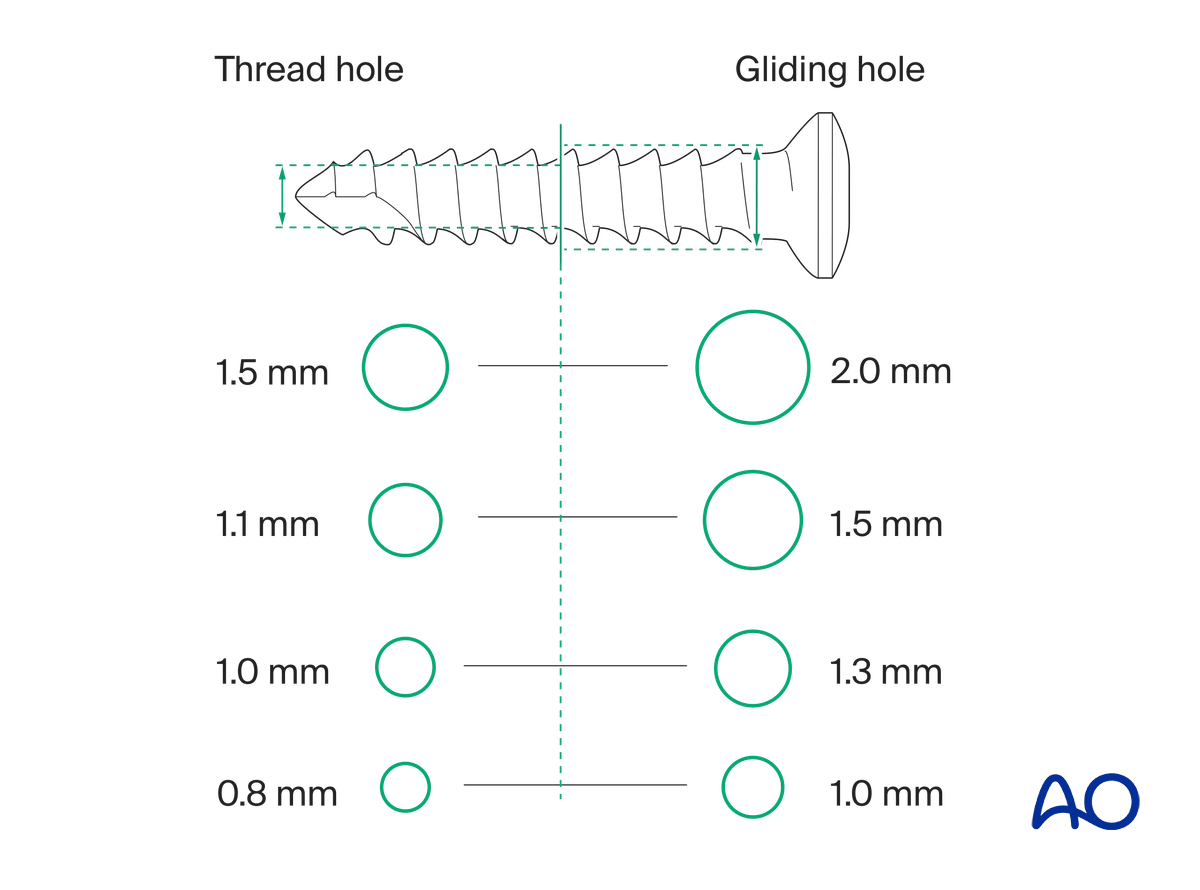
The exact size of the diameter of the screws used will be determined by the fragment size and the fracture configuration.
The various gliding and thread hole drill sizes for different screws are illustrated here.
Screw length pitfalls
- Too short screws do not have enough threads to engage the cortex properly. This problem increases when self-tapping screws are used due to the geometry of their tip.
- Too long screws endanger soft tissues, especially tendons and neurovascular structures. With self-tapping screws, the cutting flutes are especially dangerous, and great care has to be taken that the flutes do not protrude beyond the cortical surface.
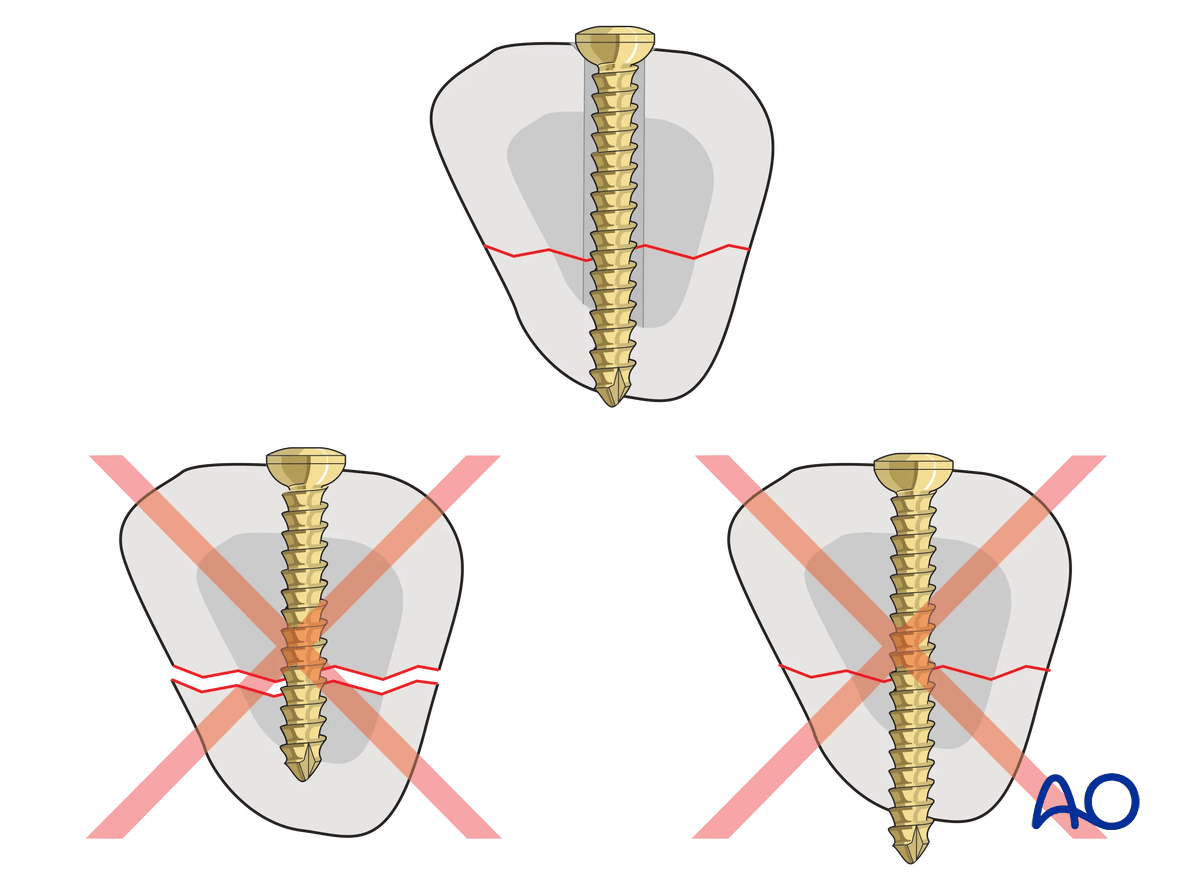
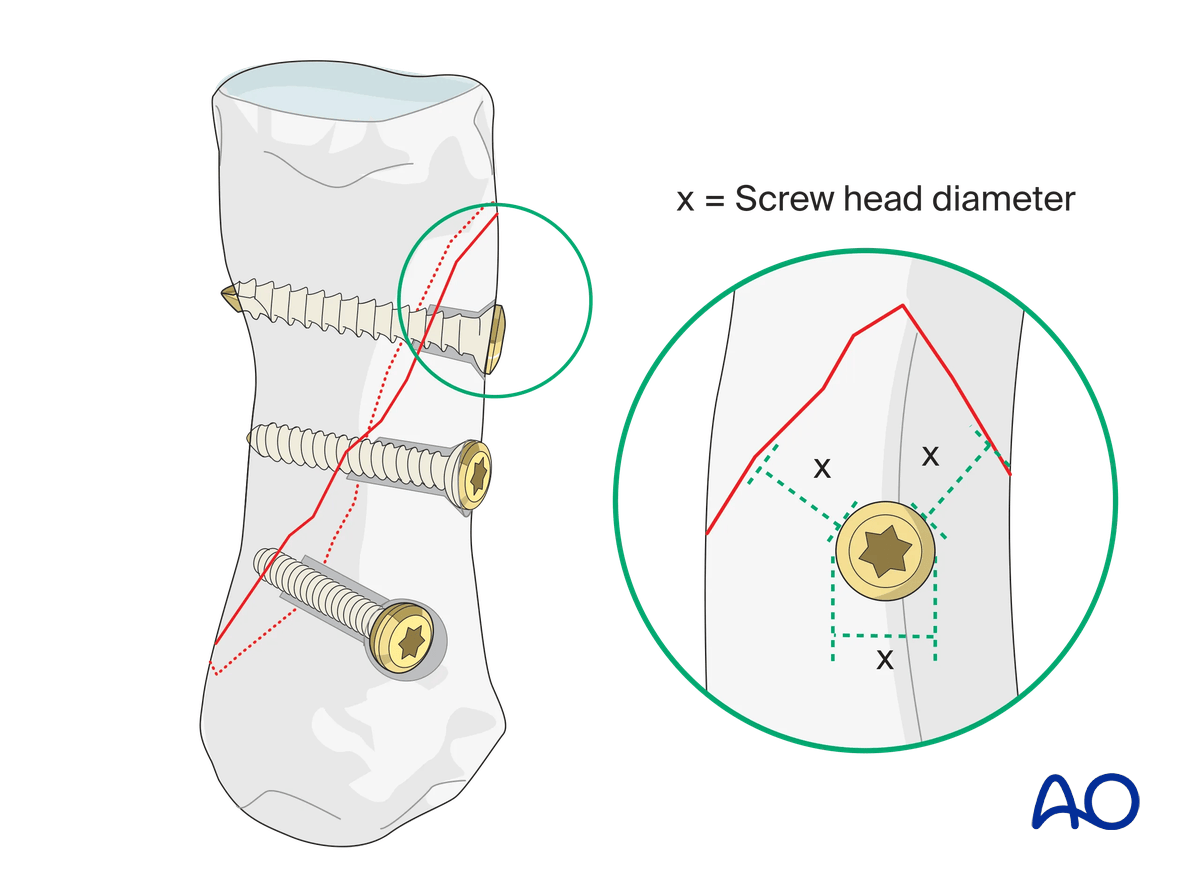
Pitfall: screw too close to the fracture
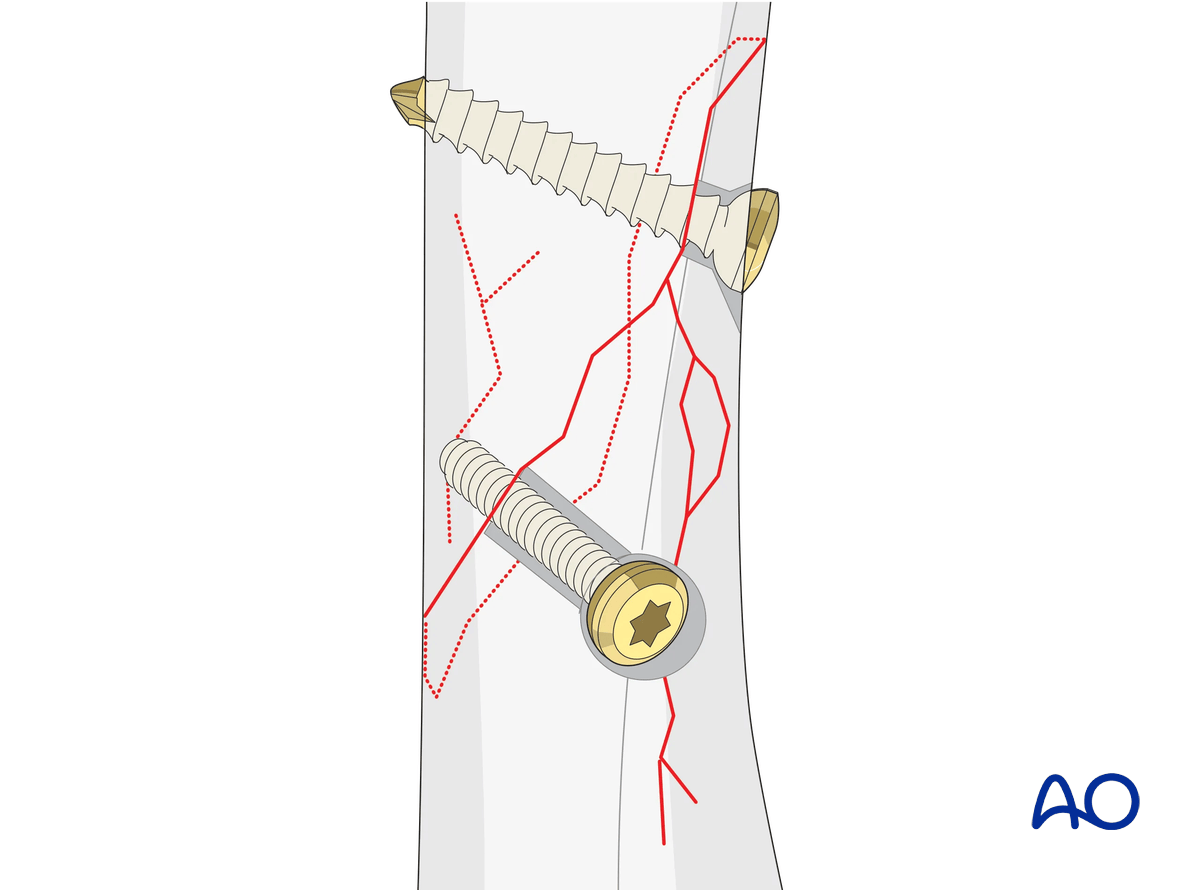
Pitfall: beware of fissure lines
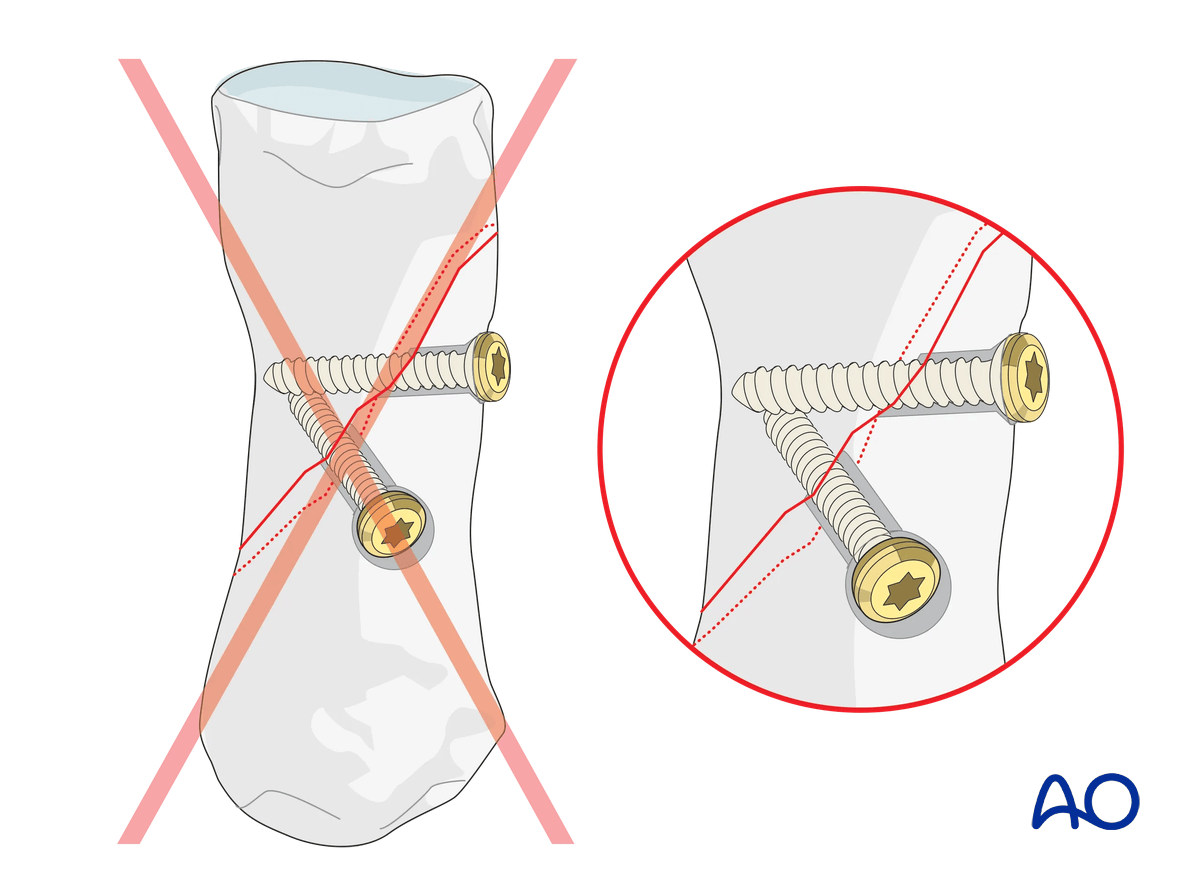
Pitfall: screw convergence
7. Final assessment
Confirm correct rotational alignment by clinical examination.
Image intensification may be used to confirm anatomical reduction and correct placement of implants in two views.
8. Aftercare
Healing phases
The aftercare can be divided into four phases of healing:
- Inflammatory phase (week 1–3)
- Early repair phase (week 4–6)
- Late repair and early tissue remodeling phase (week 7–12)
- Remodeling and reintegration phase (week 13 onwards)
Full details on each healing phase can be found in the chapter Postoperative treatment of thumb injuries.
Postoperative care
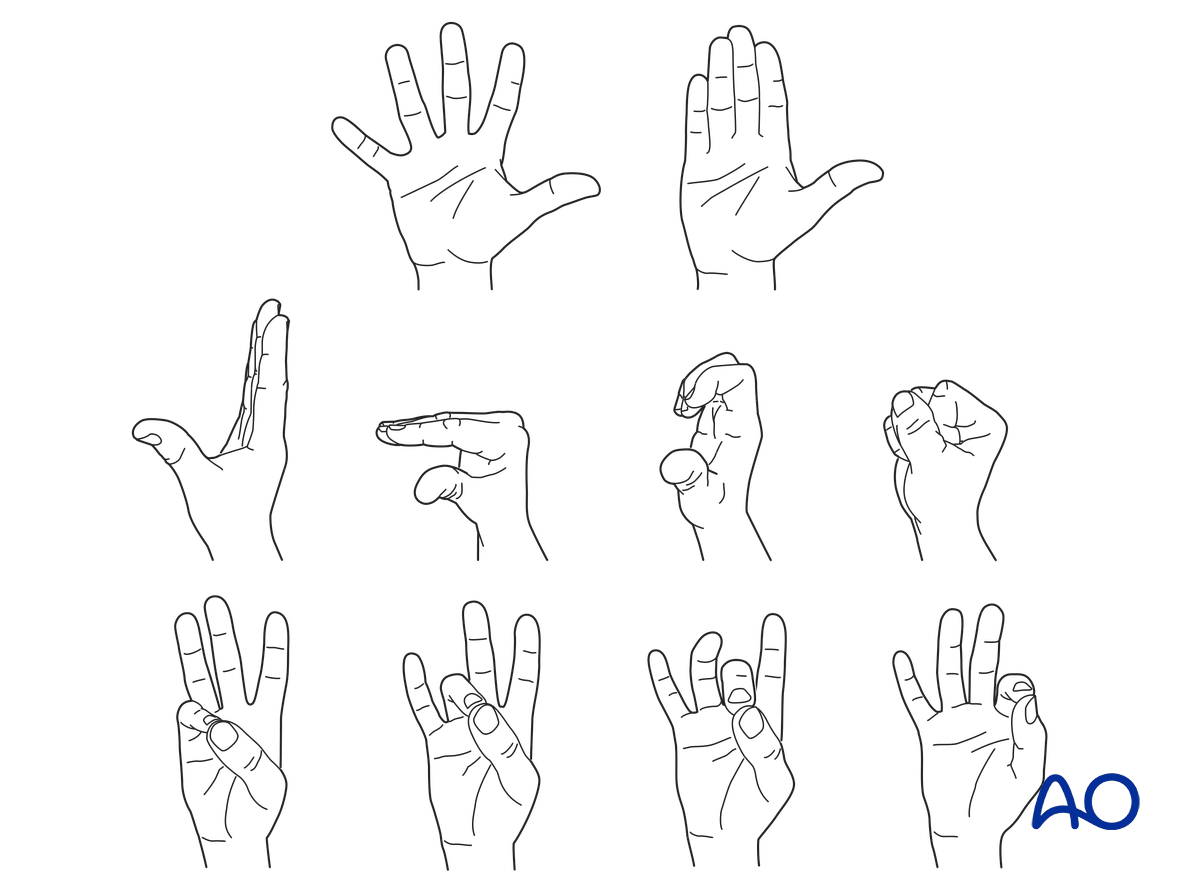
Early range of motion, without load bearing, in the hand is important for optimal outcome.
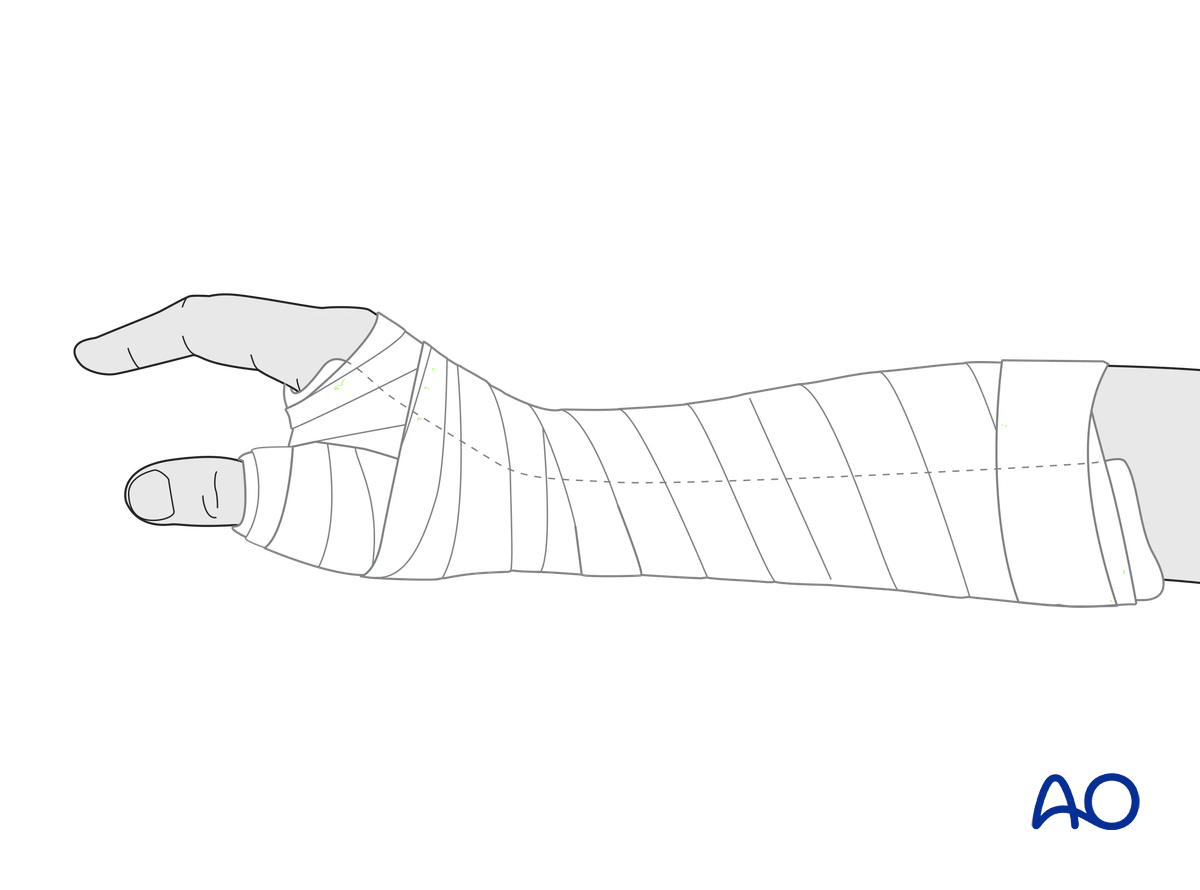
Immediately postoperatively, a temporary plaster splint is applied. This also helps with swelling and pain control.
The plaster splint can be switched to a custom-made thermoplastic splint after a week. The splint should be worn until fracture healing has been confirmed.
Hand therapy should be initiated as soon as possible.
The arm should be actively elevated to help reduce any swelling.
Mobilization
To prevent joint stiffness, the patient should be instructed to begin active motion (flexion and extension) of all nonimmobilized joints of the hand immediately after surgery.
In compliant patients with stable fixation, the splint can be removed under the supervision of a hand therapist, and early active motion exercises started after a few days.
Weight bearing should be avoided until fracture healing is confirmed.
Follow-up
The surgical wound is checked as necessary depending on soft tissue status. The wound is monitored for evidence of infection.
To allow for early joint mobilization and to prevent wound dehiscence, leave the sutures for 2 weeks.
Confirm fracture healing clinically and radiologically after about 5–6 weeks (depending on the fracture configuration).


