Supine patient position
1. Introduction
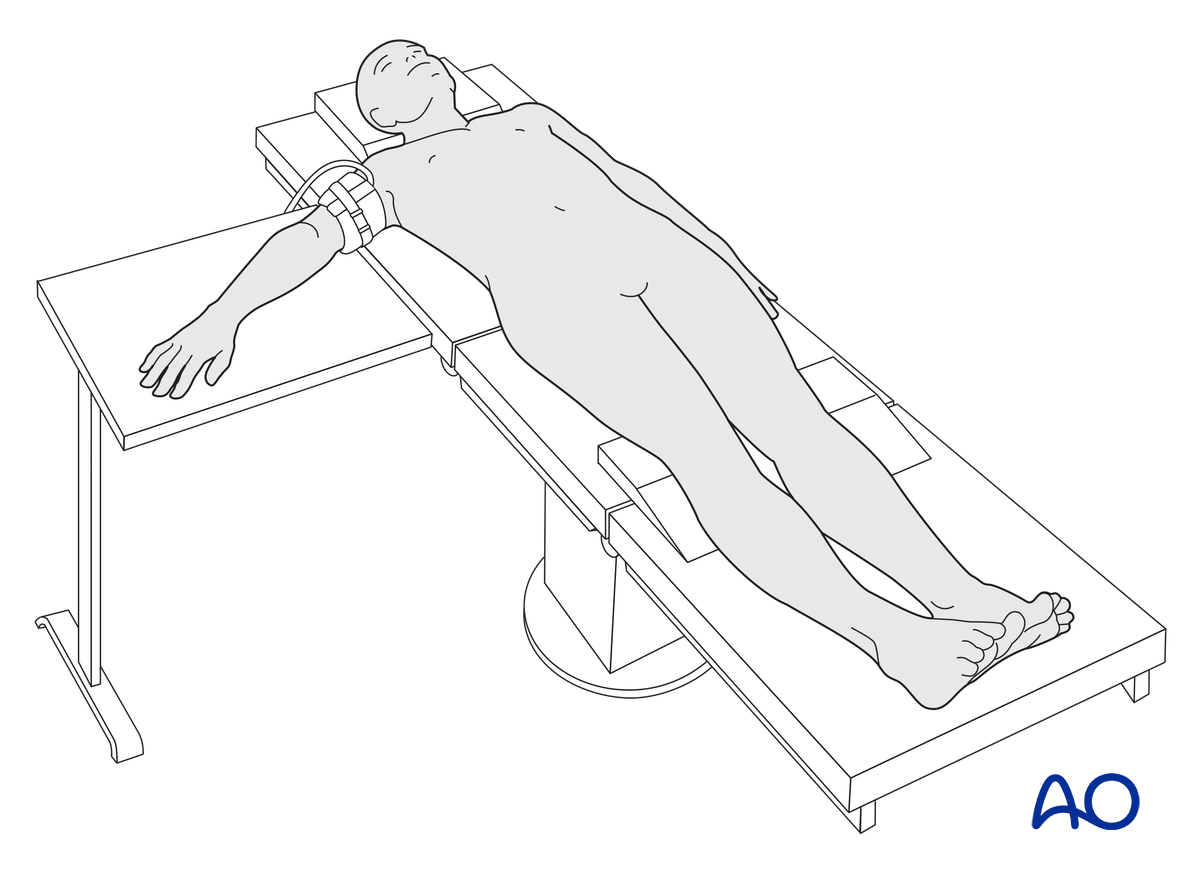
The patient is usually in a supine position with the arm on a radiolucent hand table.
2. Preoperative preparation
For surgery, the operating surgeon needs to confirm:
- Details of the patient (including a signed consent form, comorbidities, including allergies)
- Patient positioning
- Side and site of the fracture
- Ensure that the operative site is marked
- Type of operation planned (percutaneous or open approach)
- Need for a tourniquet
- Condition of the soft tissues
- Implants to be used
- Appropriate antibiotic and thromboprophylaxis
- Need for postoperative splintage
3. Anesthesia
- General anesthesia
- Regional nerve block
- Combination of nerve block and light general anesthesia
Alternatively, the patient stays awake with local anesthesia (WALANT) without a tourniquet. This allows active movement of the hand and fingers during the operation, especially to check for alignment.
- Lalonde DH, Wong A. Dosage of local anesthesia in wide awake hand surgery. J Hand Surg Am. 2013 Oct;38(10):2025–2028.
- Joukhadar N, Lalonde DH. How to Minimize the Pain of Local Anesthetic Injection for Wide Awake Surgery. Plast Reconstr Surg Glob Open. 2021 Aug4;9(8):e3730.
- Lalonde DH. Wide awake hand surgery. Stuttgart, New York: Georg Thieme; 2011.
4. Patient positioning
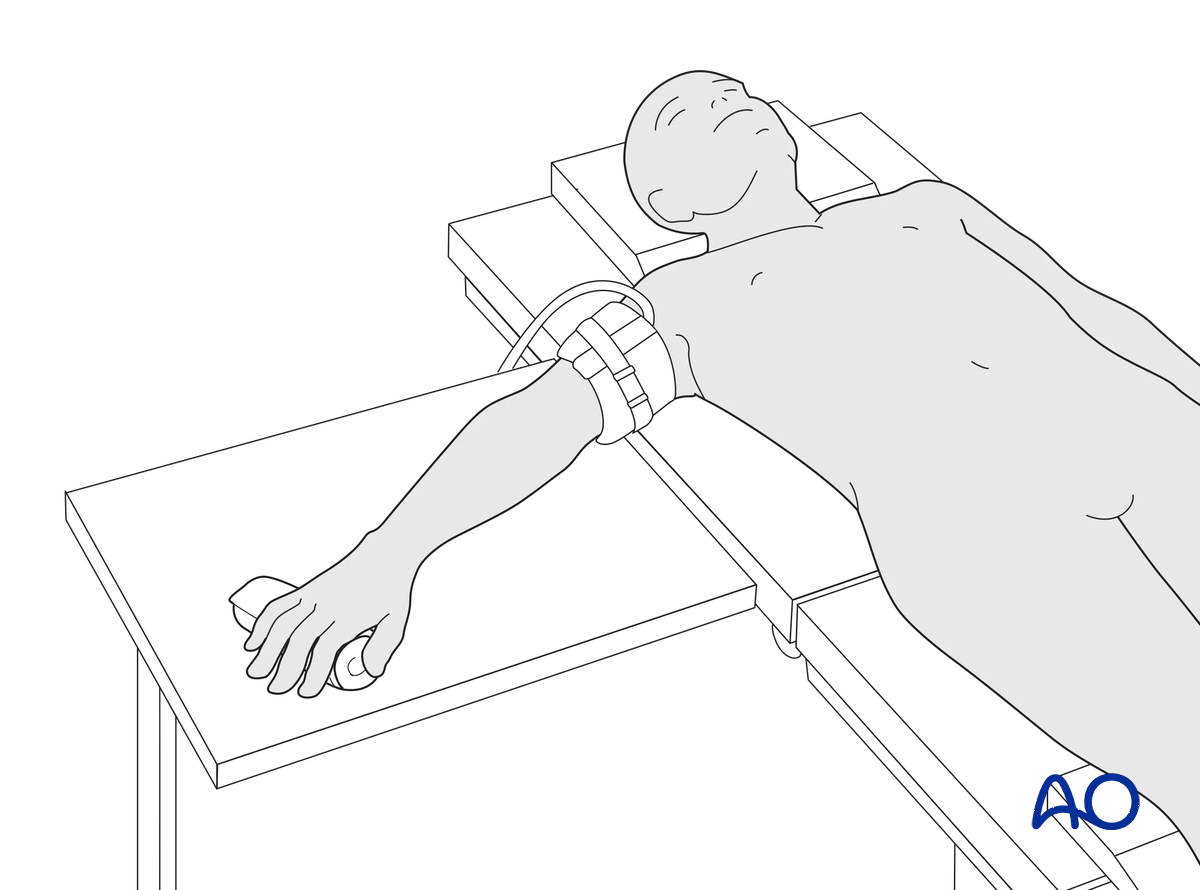
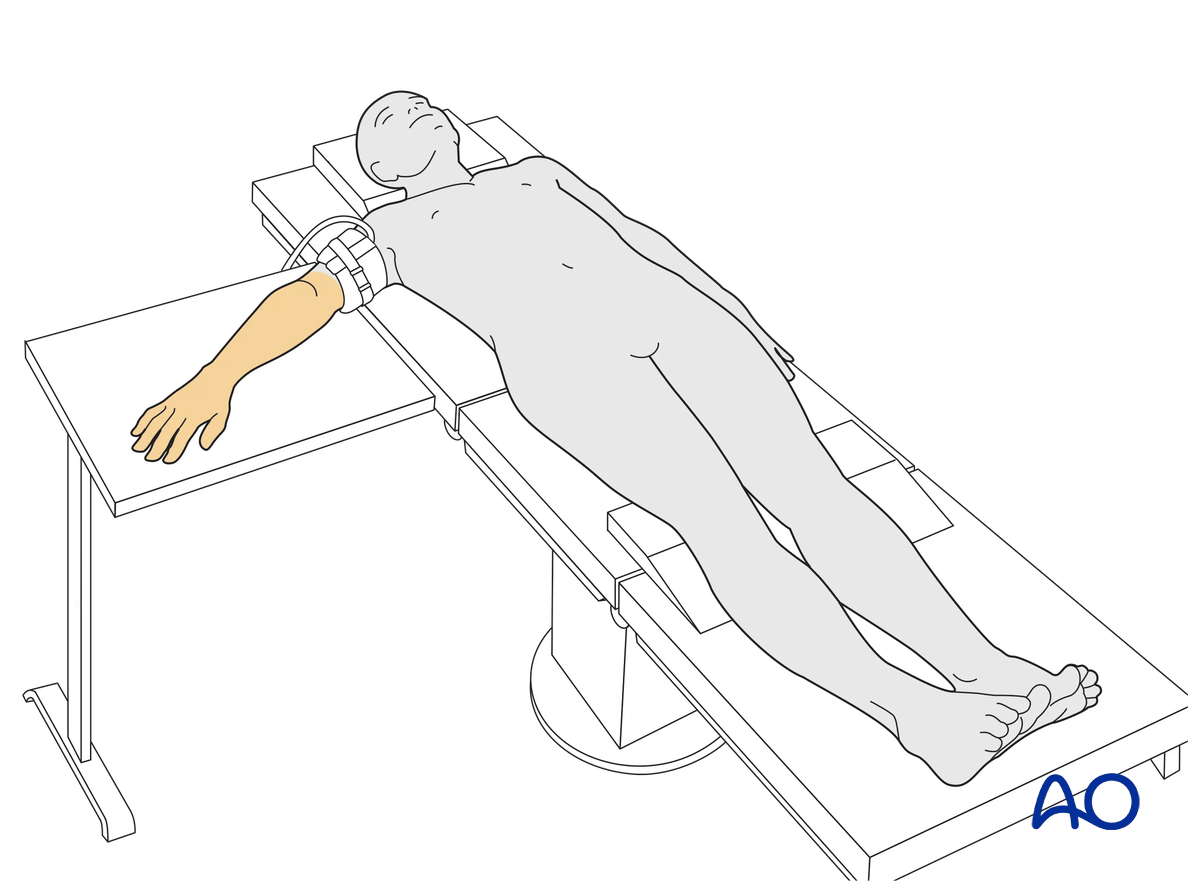
Position the patient supine and place the forearm on the radiolucent hand table.
As the hand tends to be semisupinated, rotate the shoulder to allow the hand to be placed in an appropriate pronated position for a dorsal approach.
Supinate the forearm for a palmar approach.
In some cases, a combined dorsal and palmar approach may be required.
Exsanguination and a pneumatic tourniquet are recommended.
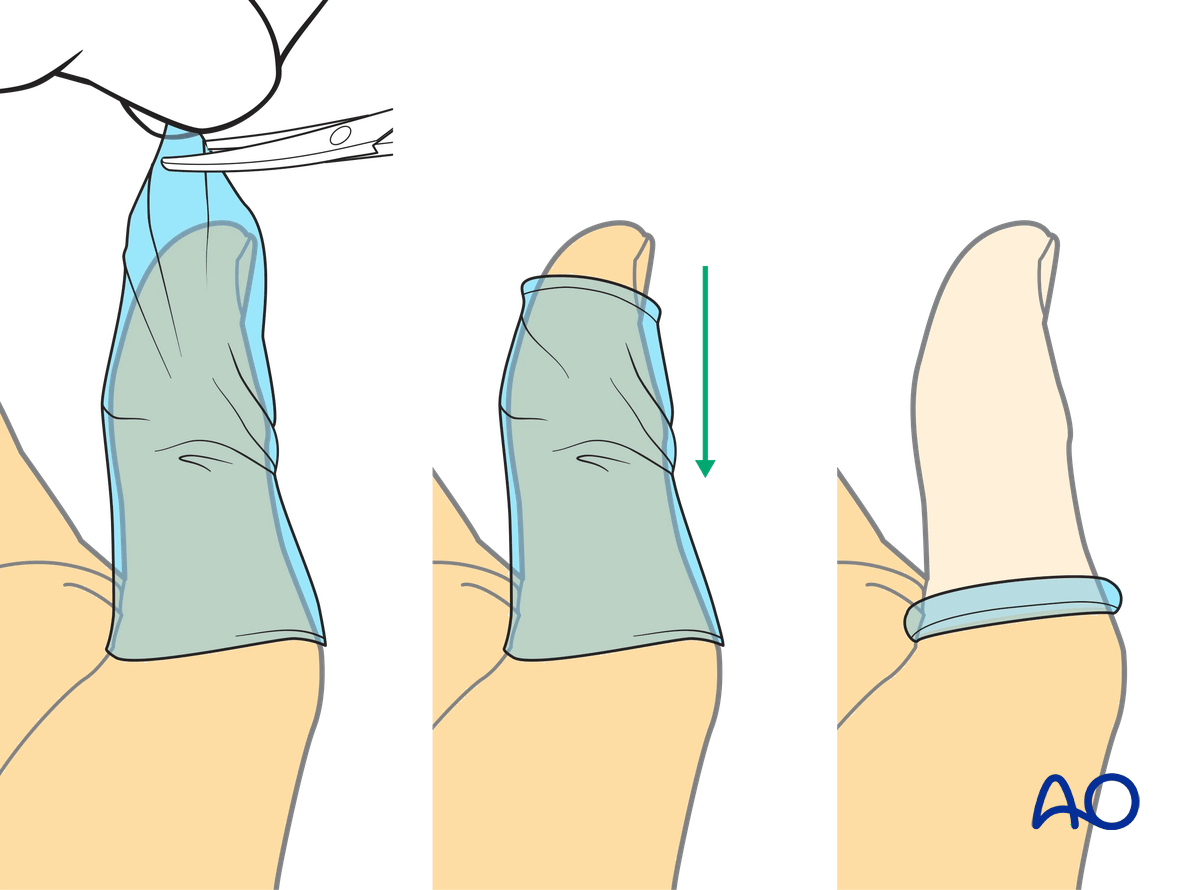
Alternatively, exsanguination and tourniquet application at the level of the proximal phalanx can be easily performed by rolling up the finger of a sterile glove.
C-arm positioning
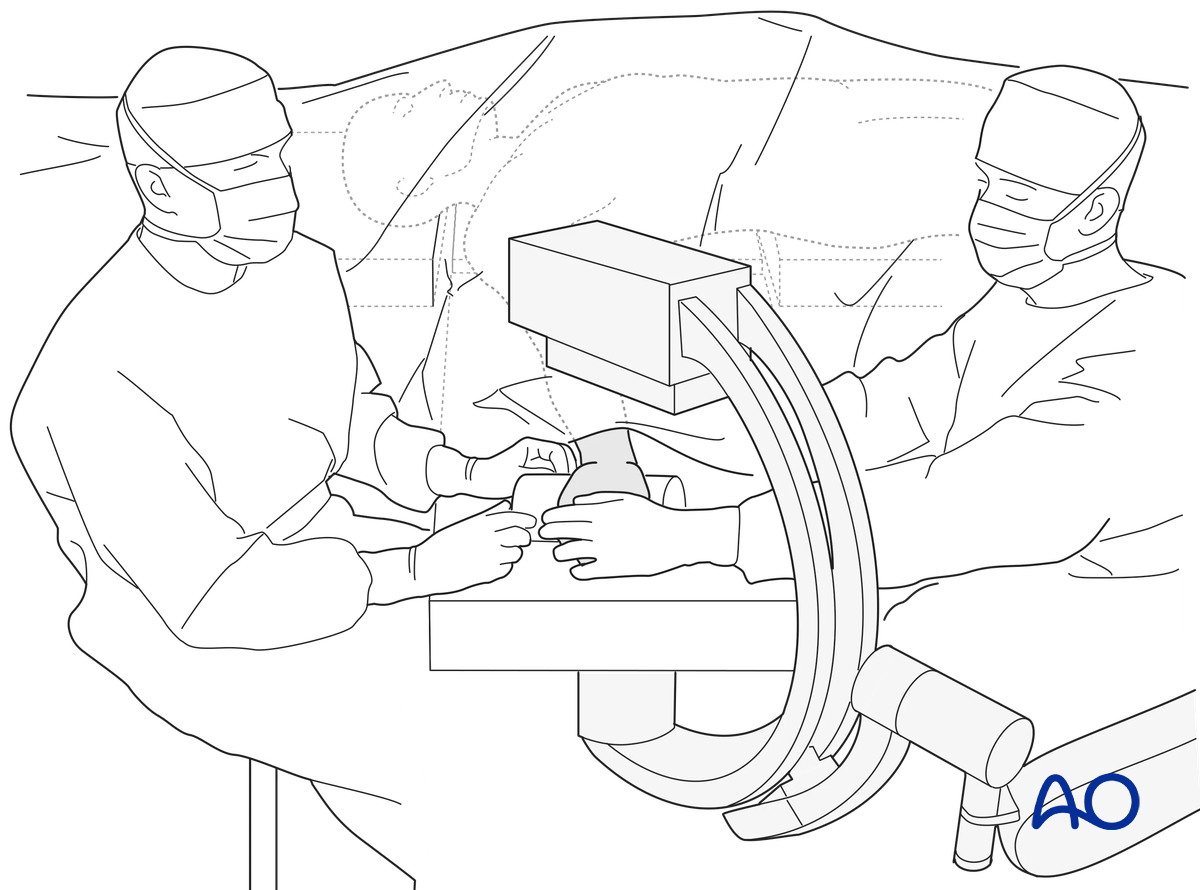
The image intensifier should be positioned to not interfere with the operating surgeon’s access to the surgical field.
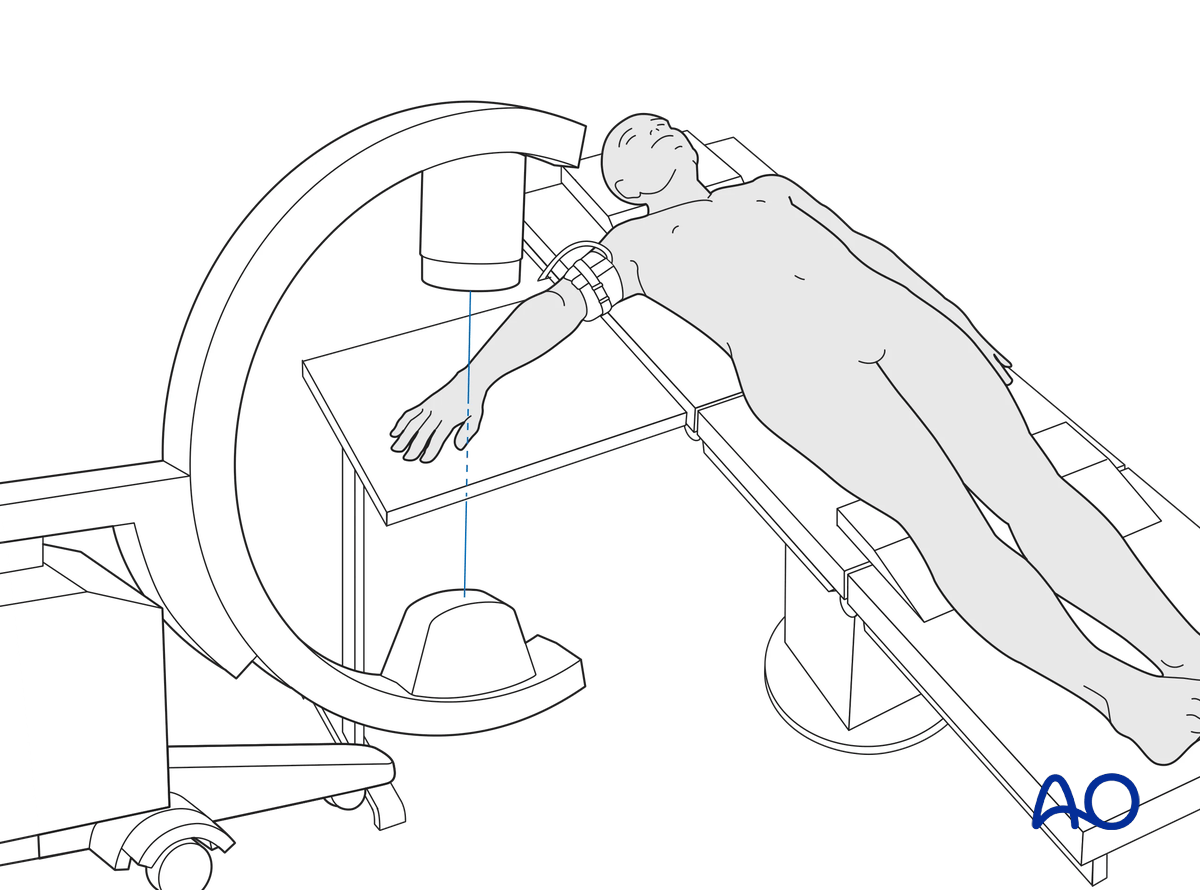
If available, the use of a small image intensifier is recommended.
Skin disinfecting and draping
Disinfect the entire hand, wrist, and arm with the appropriate antiseptic right up to the limits of the tourniquet cuff. This allows full exsanguination.
Preparation of the entire upper limb allows repositioning during surgery.
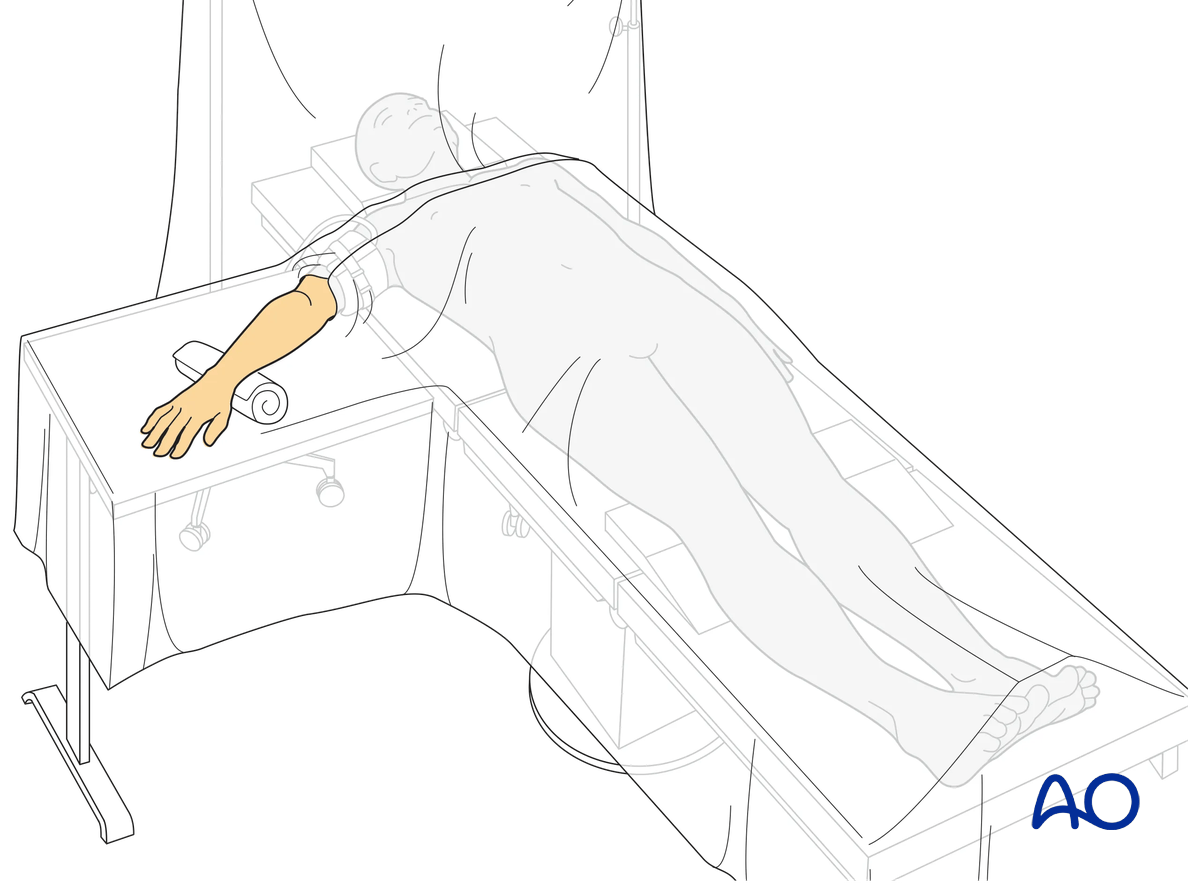
A protective specific tourniquet exclusion drape can be used to avoid tracking of antiseptic solution under the tourniquet while in use: if alcohol-based antiseptic is used, skin damage can occur from prolonged contact with soaked material during surgery.
Colorless antiseptics are recommended as this allows for intra- and postoperative assessment of skin color in conditions such as burns and injuries associated with vascular lesions.
A single-use occlusive hand drape with an expandable arm opening is recommended to isolate the upper limb.
Drape the image intensifier.
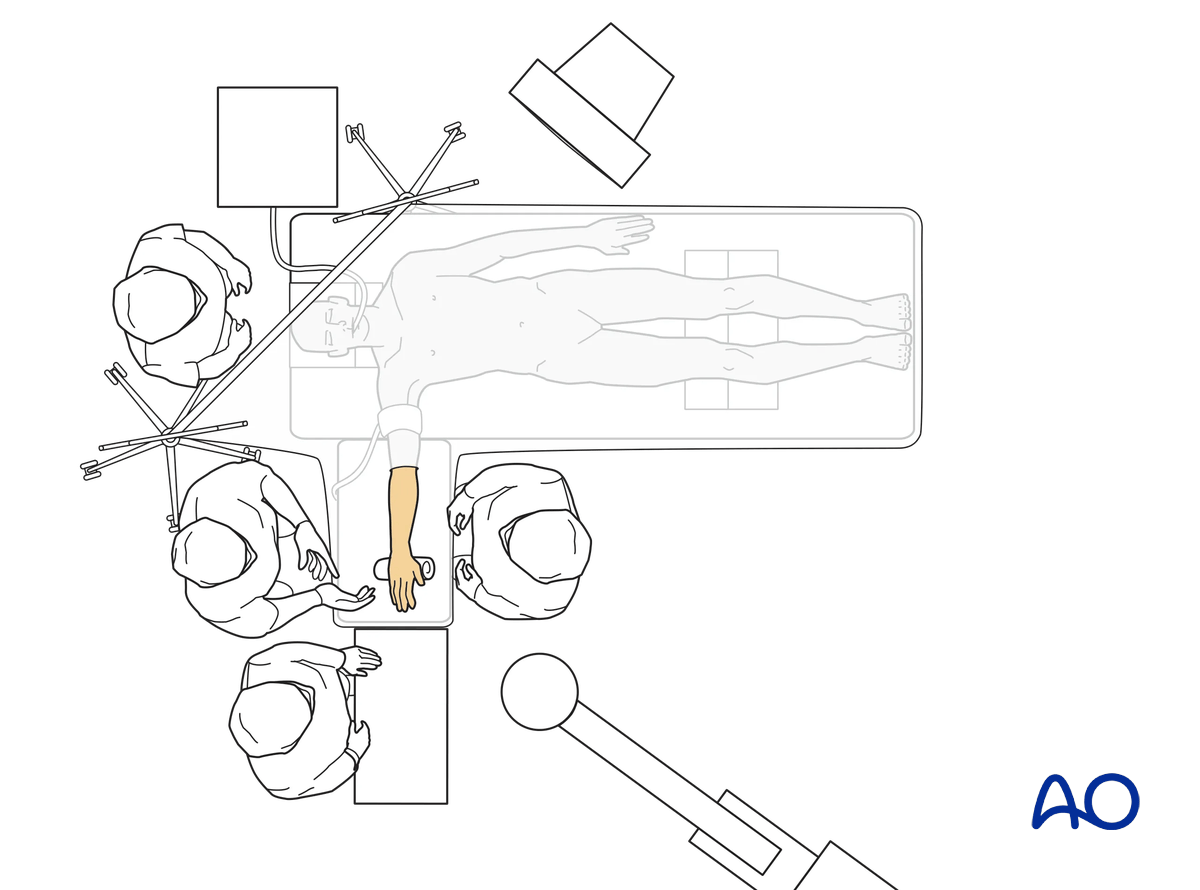
Operating room set-up
The surgeon sits beside the patient’s head to gain a good view and access to the dorsum of the hand. If a palmar approach needs to be performed, the surgeon sits on the opposite side of the arm table.
The assistant sits opposite the surgeon. The ORP sits at the end of the hand table.
Place the image intensifier screen in full view of the surgical team and the radiographer.