

Bridging plate fixation
1. Indications
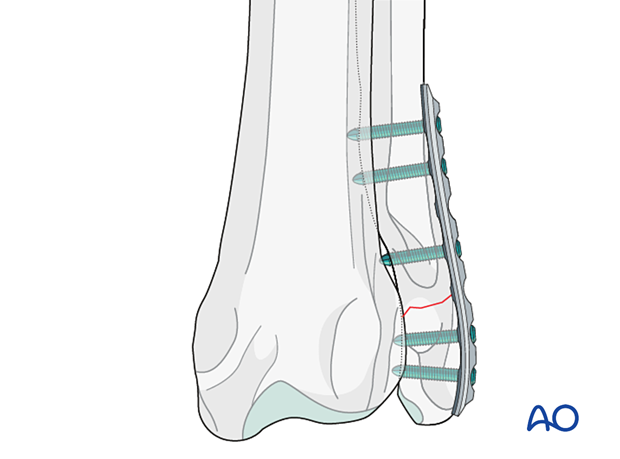
The goal of 23-A1 fracture treatment is anatomical reduction of the ulna. In most cases, this is best achieved with compression plate fixation. In rare cases, in which there is a degree of comminution of the ulna, it may be more appropriate to consider bridging plate fixation of the distal and proximal fragments.
Fixation of isolated distal ulnar fracture offers stability and is mainly indicated in large, giant breed, and performance working dogs.
2. Preparation and approach
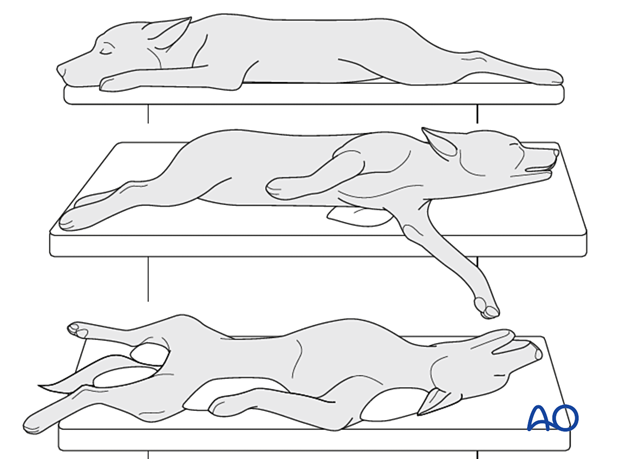
The patient can be in sternal, lateral, or dorsal recumbency.
In lateral recumbency, the nonaffected leg should be in contact with the table.
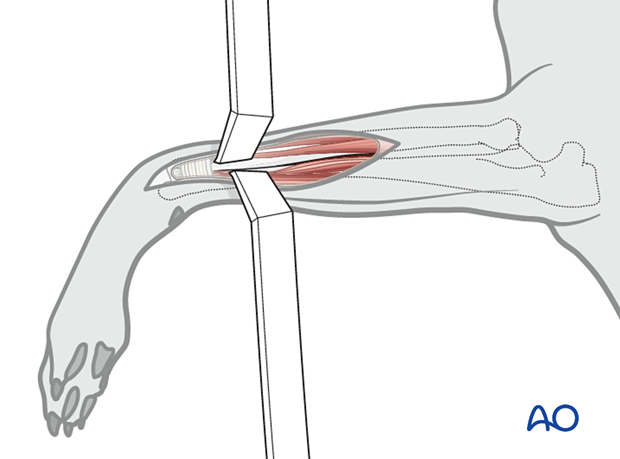
A lateral approach to the distal ulna is performed.
3. Reduction
The goal is to achieve anatomical reduction.
The proximal fragment is connected to the radius through interosseous ligament and is stable, not requiring manipulation.
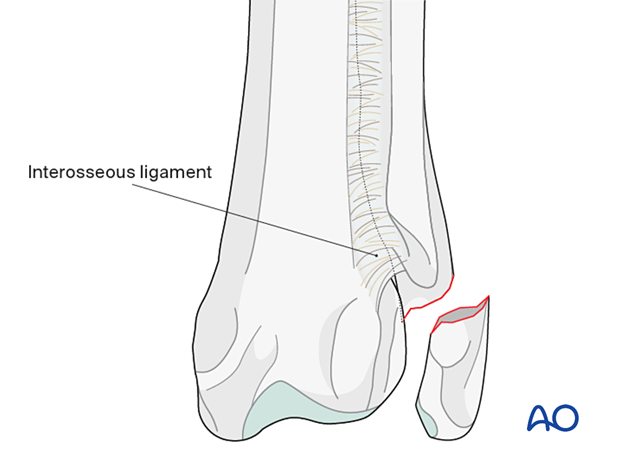
The distal fragment is manipulated with pointed reduction forceps to achieve reduction.
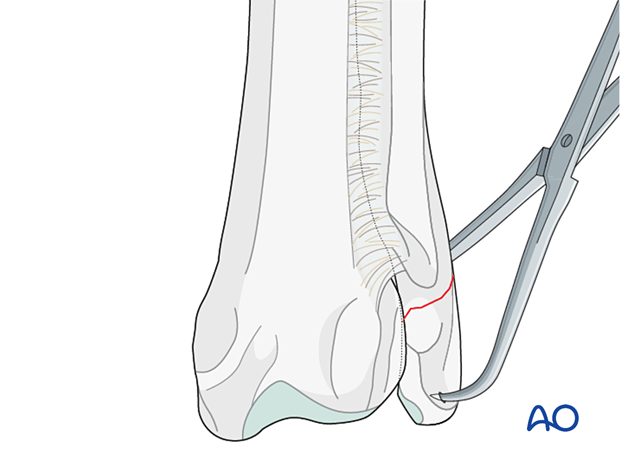
Option 1
A temporary K-wire inserted in the distal fragment can be used as a joystick to achieve reduction and then driven into the proximal fragment.
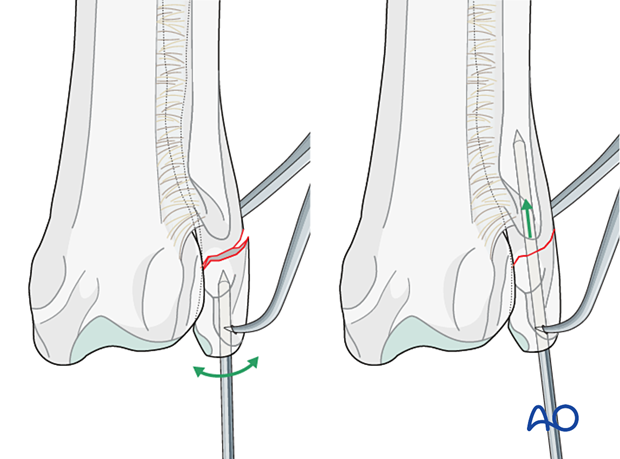
Option 2
Alternatively, the plate can be fixed in the distal fragment first and then used to achieve reduction on the proximal fragment.
In this case, the plate should be contoured before application.
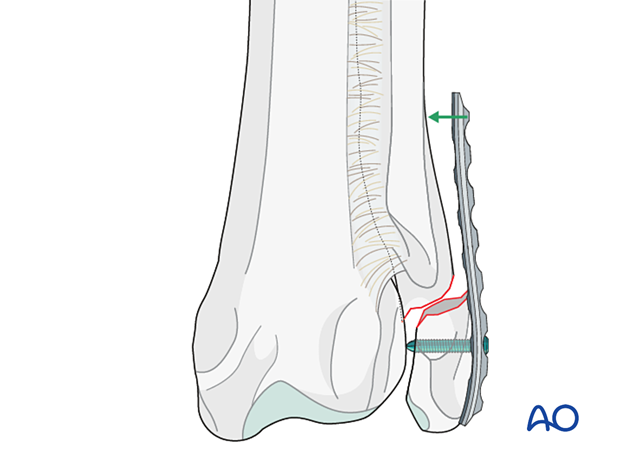
4. Fixation
Plate selection
Usually a 6- or 8-hole locking plate is used.
Two or three screws should be used in the distal fragment, and usually three screws are used in the proximal one.
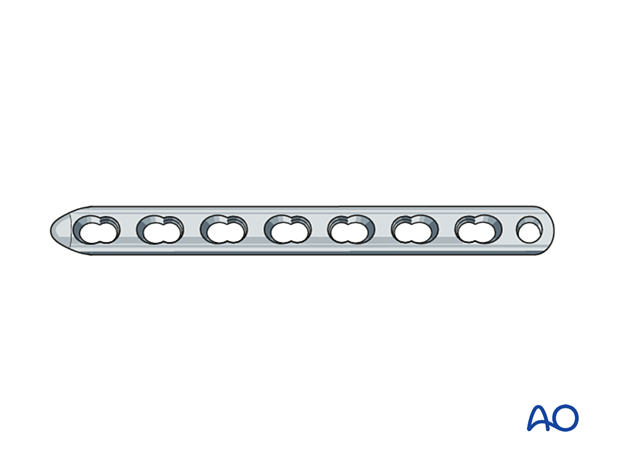
Plate contouring
A plate of appropriate size is contoured to fit the shape of the distal ulna and the styloid process.
Accurate contouring is not essential in locking plates.
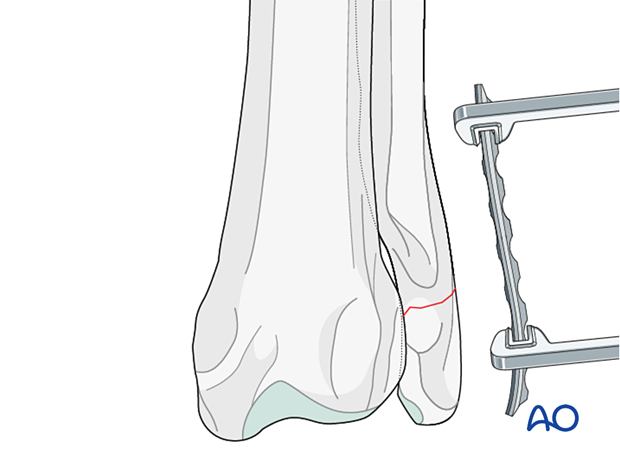
Fixation with a locking compression plate
Reduction and apposition should be maintained with bone forceps holding the plate during plate fixation.
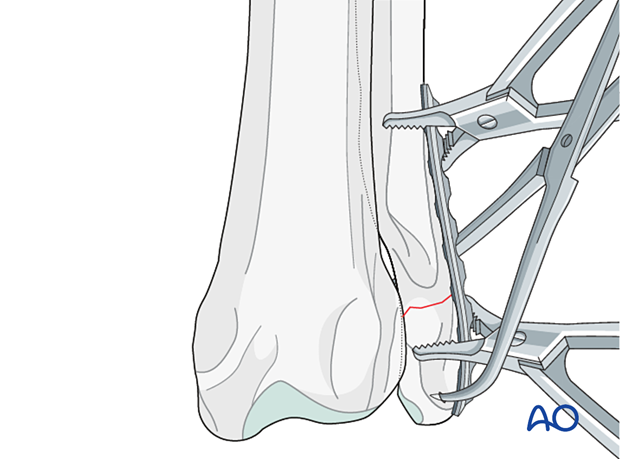
Screw insertion
The order of screw insertion is not critical with fully locking screw plates.
A minimum of two screws should be inserted in the distal fragment and three in the proximal one.
5. Aftercare
Phase 1: 1–3 days after surgery
The aim is to reduce edema, inflammation, and pain.
Following appropriate internal fixation, there should be no absolute need for external coaptation for a 23-A1 fracture. If bandaging is used to decrease edema and protect the surgical wound, it should be removed after 24–48 hours to reduce the risk of complications.
Integrative medical therapies, anti-inflammatory medications, and analgesics are recommended.
10–20 minutes of ice therapy is recommended every 8 hours in most cases.
The patient can immediately bear weight, but with strict control of activities.
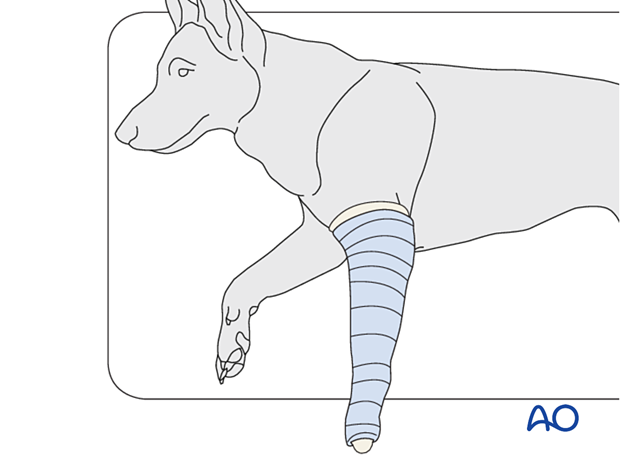
Phase 2: 4–10 days after surgery
The aim is to resolve hematoma and edema, control pain, and prevent muscle contracture. Anti-inflammatory and analgesic medications may still be needed.
Rehabilitation and integrative medical therapies can be used.
A careful evaluation is recommended if the patient is not starting to use the limb within a few days after surgery.
Phase 3: > 10 days after surgery
The sutures are removed 10–14 days after surgery.
Immature patients should be radiographed every 4 weeks.
A radiographic assessment is performed every 4–6 weeks until bone healing is confirmed, more frequent assessment may be necessary for skeletally immature patients.


