

Lag screw with or without antirotational K-wire fixation
1. Indications
The goal of 23-B1 fracture treatment is anatomical reduction.
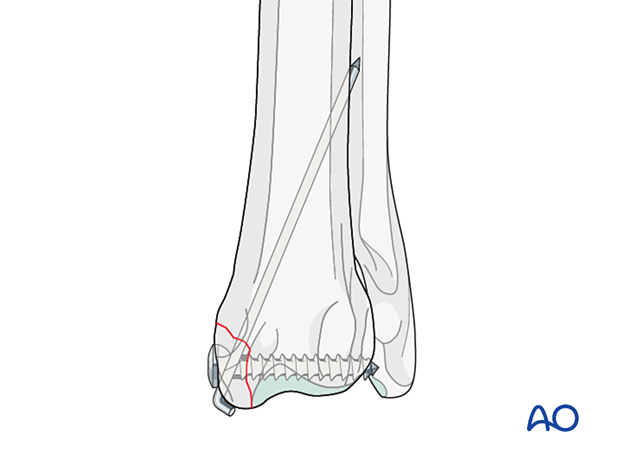
This technique is used for interfragmentary compression for larger bone fragments. The reduction is obtained with the insertion of a K-wire in the distal fragment, from the radial styloid process across the fracture line. A screw is inserted across the fracture plane in lag fashion and tightened to achieve interfragmentary compression.
2. Preparation and approach
The patient can be in dorsal or lateral recumbency.
In lateral recumbency, the affected leg should be in contact with the table.
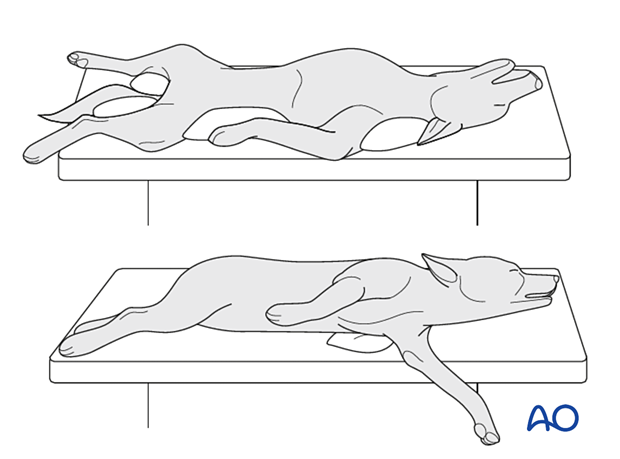
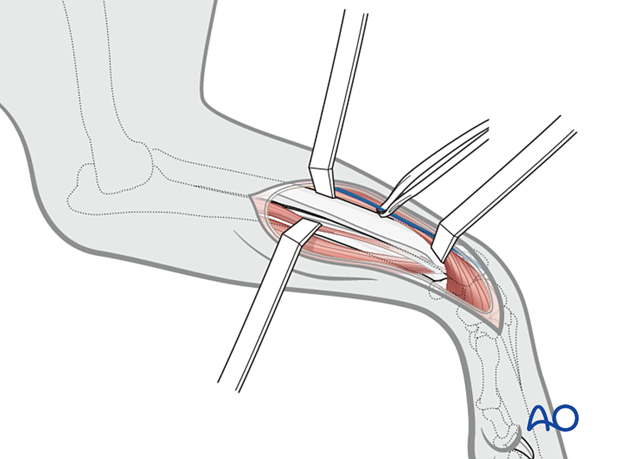
A craniomedial approach to the distal radius is performed.
3. Reduction
The goal is to achieve anatomical reduction.
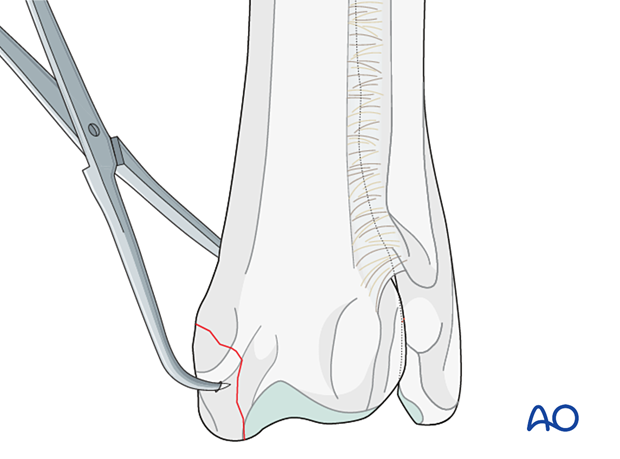
Anatomical reduction is obtained with the help of one pointed reduction forceps placed across the fracture line.
Option
Alternatively, the K-wire can be inserted in the distal fragment first and then used as a joystick to achieve reduction.
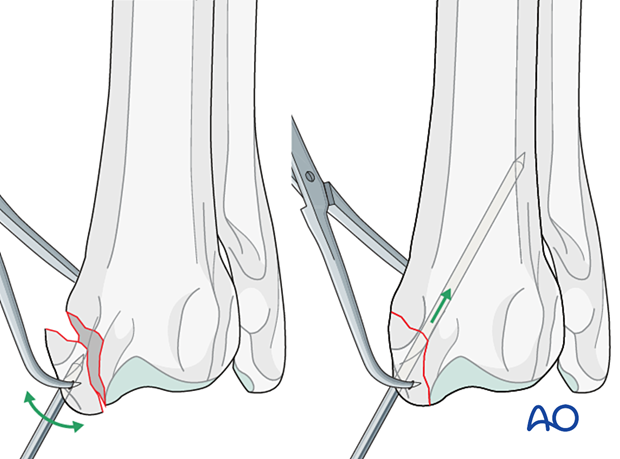
4. Fixation
Implant selection
An appropriately sized K-wire and lag screw are selected.
In some cases, the fragment is too small and it is not possible to place the antirotational K-wire, and a single lag screw can provide enough stability.
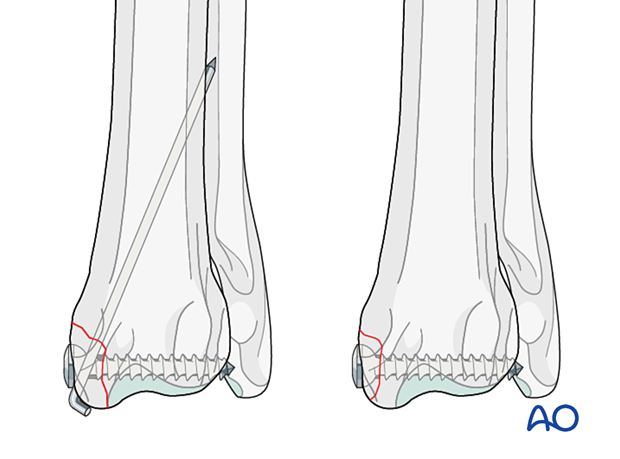
K-wire insertion
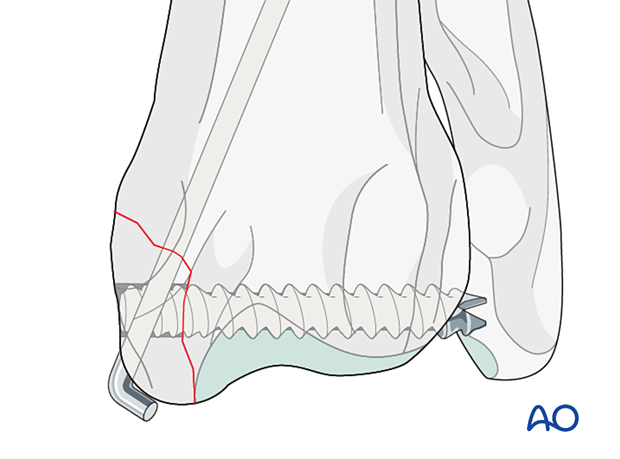
A single K-wire is inserted normograde from the radial styloid process across the fracture line into the proximal fragment engaging the lateral cortex, leaving enough room for a screw application.
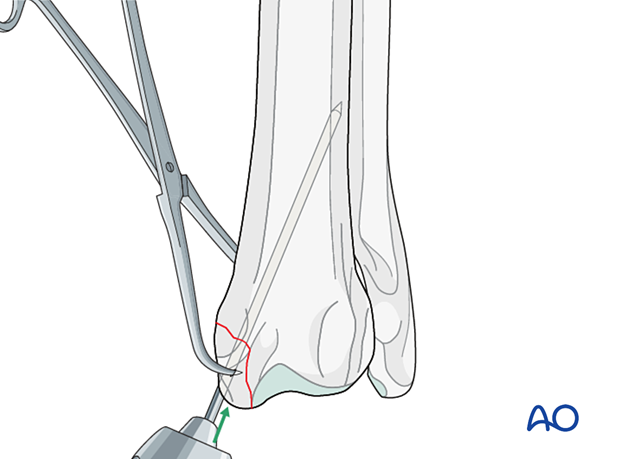
Lag screw technique
Once the fracture has been reduced, the appropriately sized screw is selected. The correct drill bit for the glide hole is used to drill a hole from the radial styloid process to the fracture line.
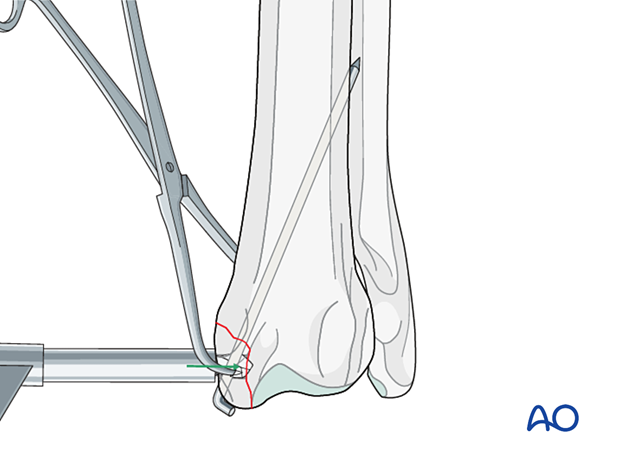
An appropriately sized drill guide is inserted into the glide hole and the correct drill bit for the threaded hole is used to drill a hole into the lateral cortex of the proximal fragment.
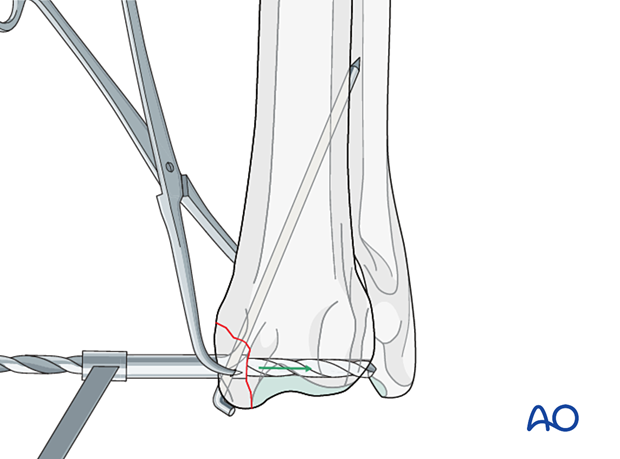
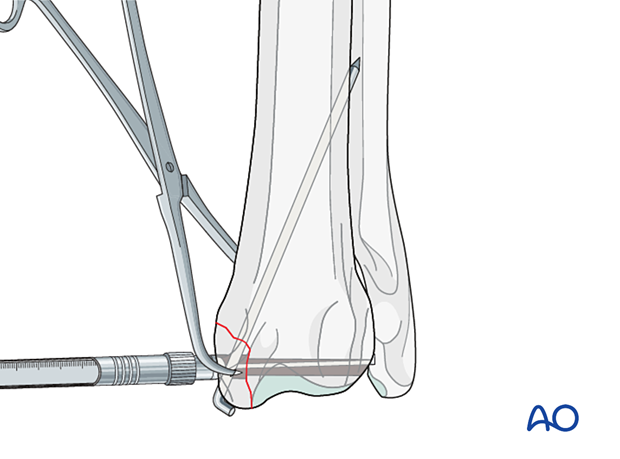
The hole depth is measured with a depth gauge, and the appropriate self-tapping screw is inserted and tightened.
Cannulated screw in lag technique
Cannulated screws have a hollow center that can be used over a guide wire. The guide wire is placed in the position of the proposed screw. Drilling, measurement of screw length, and screw insertion all require cannulated instrumentation when using this technique.
This technique offers several advantages, including the ability to redirect the guide wire for optimum screw location, enhanced temporary stability of the fracture while definitive screw placement occurs, and the ability to place the screw through a percutaneous or limited open approach.
5. Aftercare
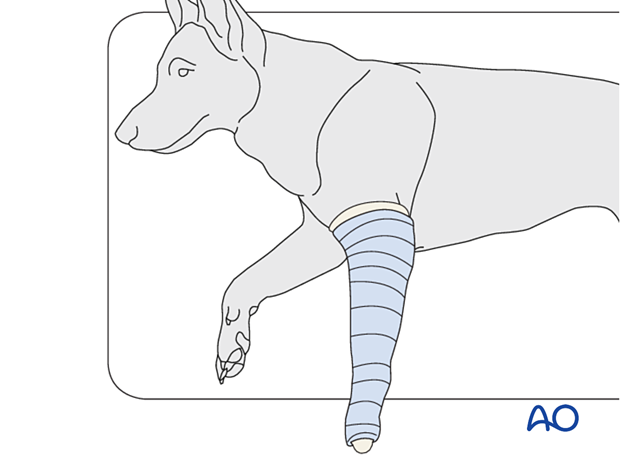
A Robert Jones or modified Robert Jones bandage can be applied for 1–3 days to decrease the edema and protect the surgical incision.
Phase 1: 1–3 days after surgery
The aim is to reduce edema, inflammation, and pain.
Integrative medical therapies, anti-inflammatory medications, and analgesics are recommended.
10–20 minutes of ice therapy is recommended every 8 hours in most cases.
The patient can immediately bear weight, but with strict control of activities.
Phase 2: 4–10 days after surgery
The aim is to resolve hematoma and edema, control pain, and prevent muscle contracture. Anti-inflammatory and analgesic medications may still be needed.
Rehabilitation and integrative medical therapies can be used.
A careful evaluation is recommended if the patient is not starting to use the limb within a few days after surgery.
Phase 3: > 10 days after surgery
The sutures are removed 10–14 days after surgery.
Immature patients should be radiographed every 4 weeks.
A radiographic assessment is performed every 4–6 weeks until bone healing is confirmed, more frequent assessment may be necessary for skeletally immature patients.


