

Extensor block pinning or K-wire fixation (with joint transfixation)
1. General considerations
Introduction
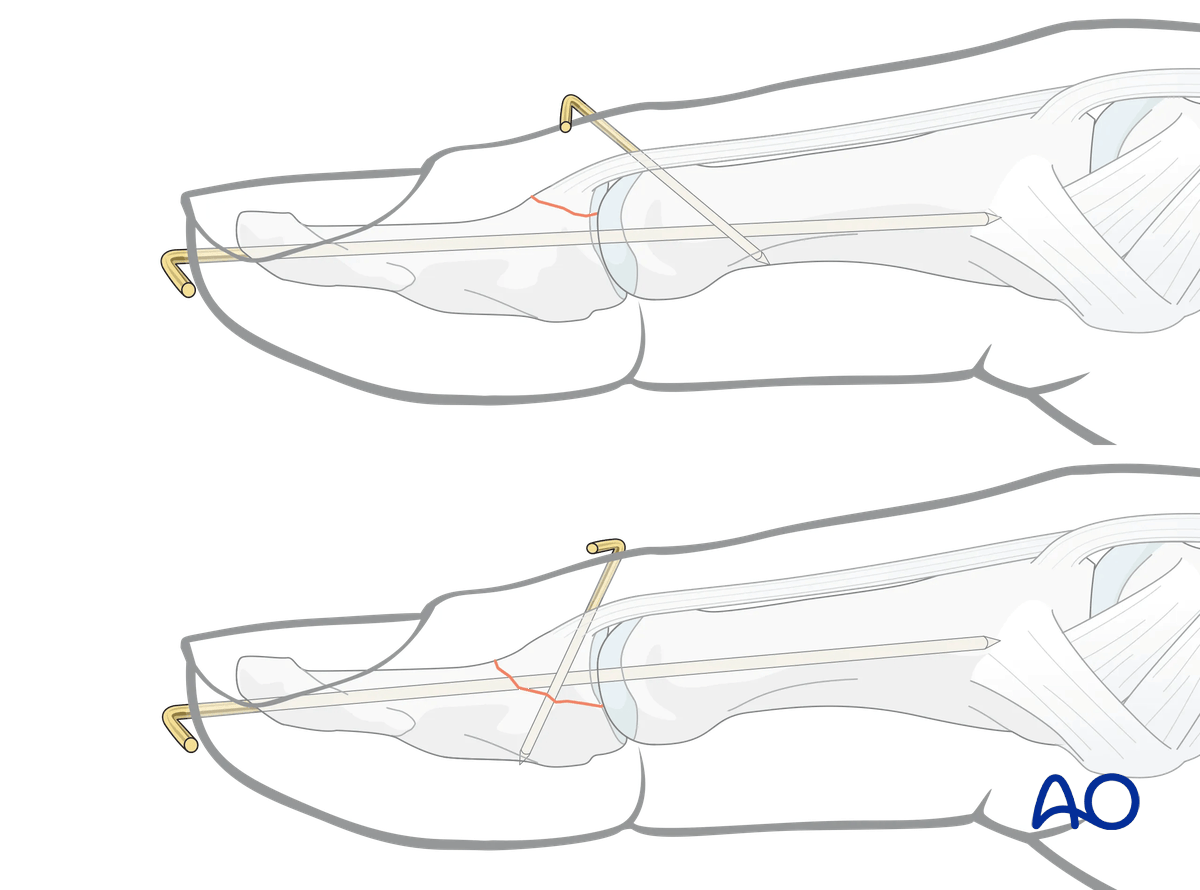
Both extensor block pinning and K-wire fixation stabilize the dorsal fragment if the distal phalanx is still dislocated after closed reduction. Additionally, the IP joint is transfixed with an axial K-wire.
Extensor block pinning can be used in case of smaller displaced dorsal fragments. It leaves the dorsal base, including the nail matrix, untouched.
If there is a large displaced dorsal fragment (>50% of the articular surface), the fragment can be fixed with a K-wire.
Operative treatment: caveat
Indications for surgical intervention are:
- Open fractures
- Palmar subluxation of the IP joint

Surgical management of these fractures is difficult and has many potential complications. The soft tissues are only precariously vascularized, and the fragments are very small and prone to further comminution. Healing can often be slow.
Potential risks of percutaneous pinning
The commonest risk of percutaneous K-wire immobilization is infection.
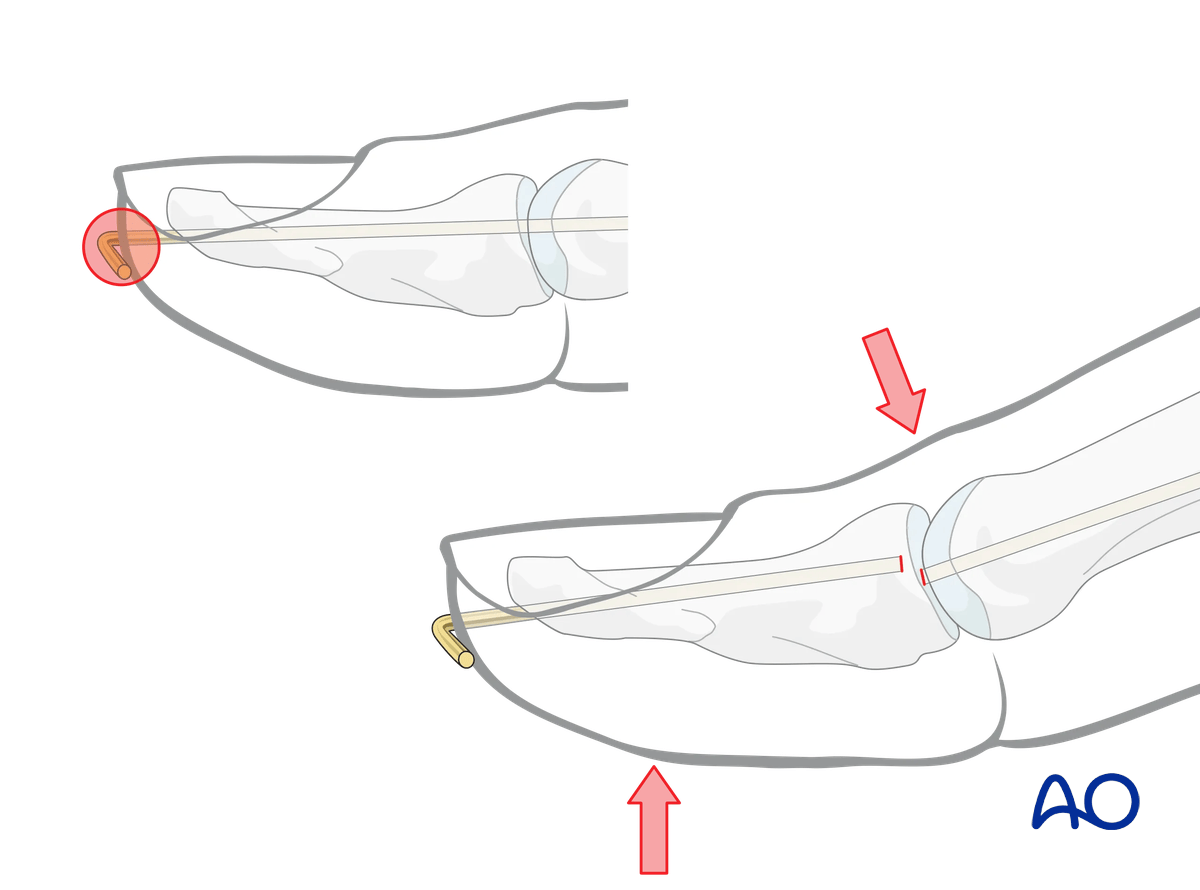
Breakage of the K-wire at the level of the IP joint can be avoided by using a wire of 1.2 or 1.4 mm diameter and counseling the patient to avoid stresses at the IP joint. The K-wire should be protected with a splint.
2. Surgical anatomy
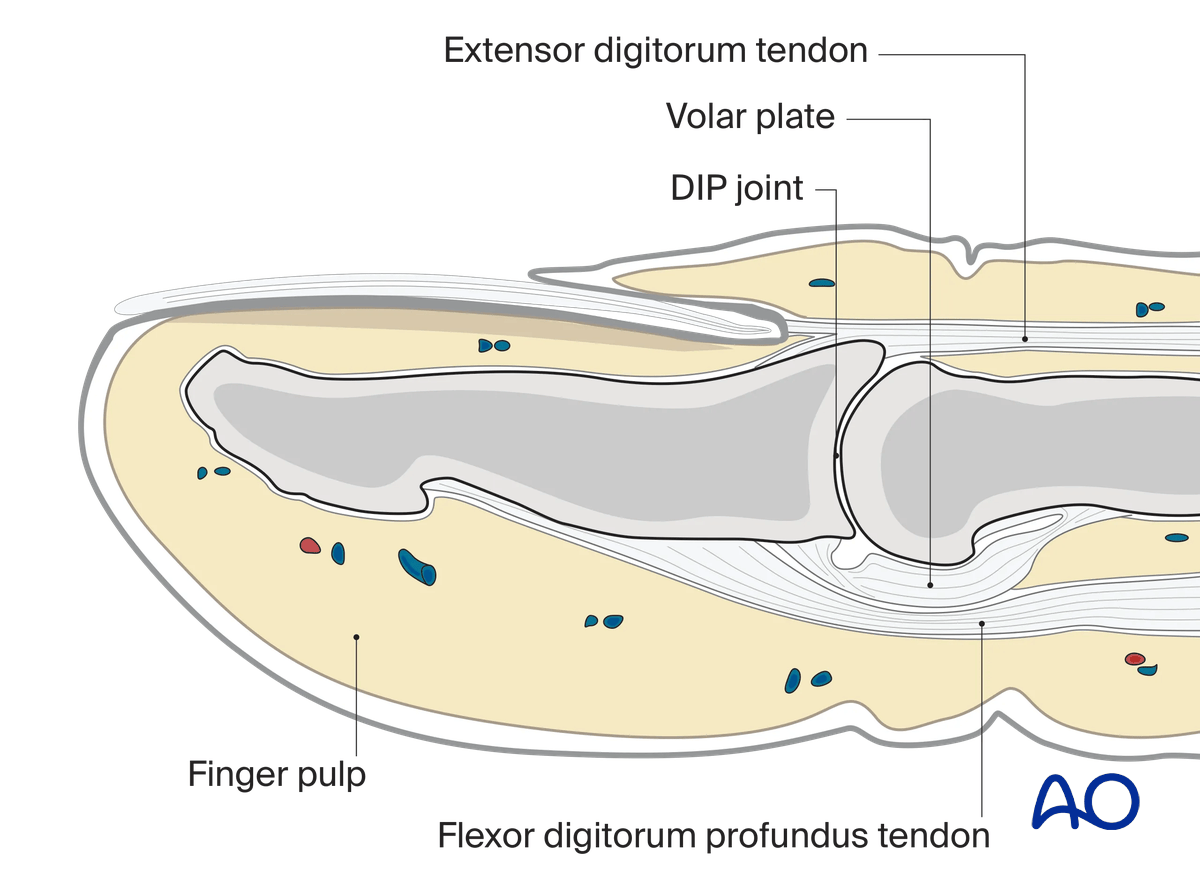
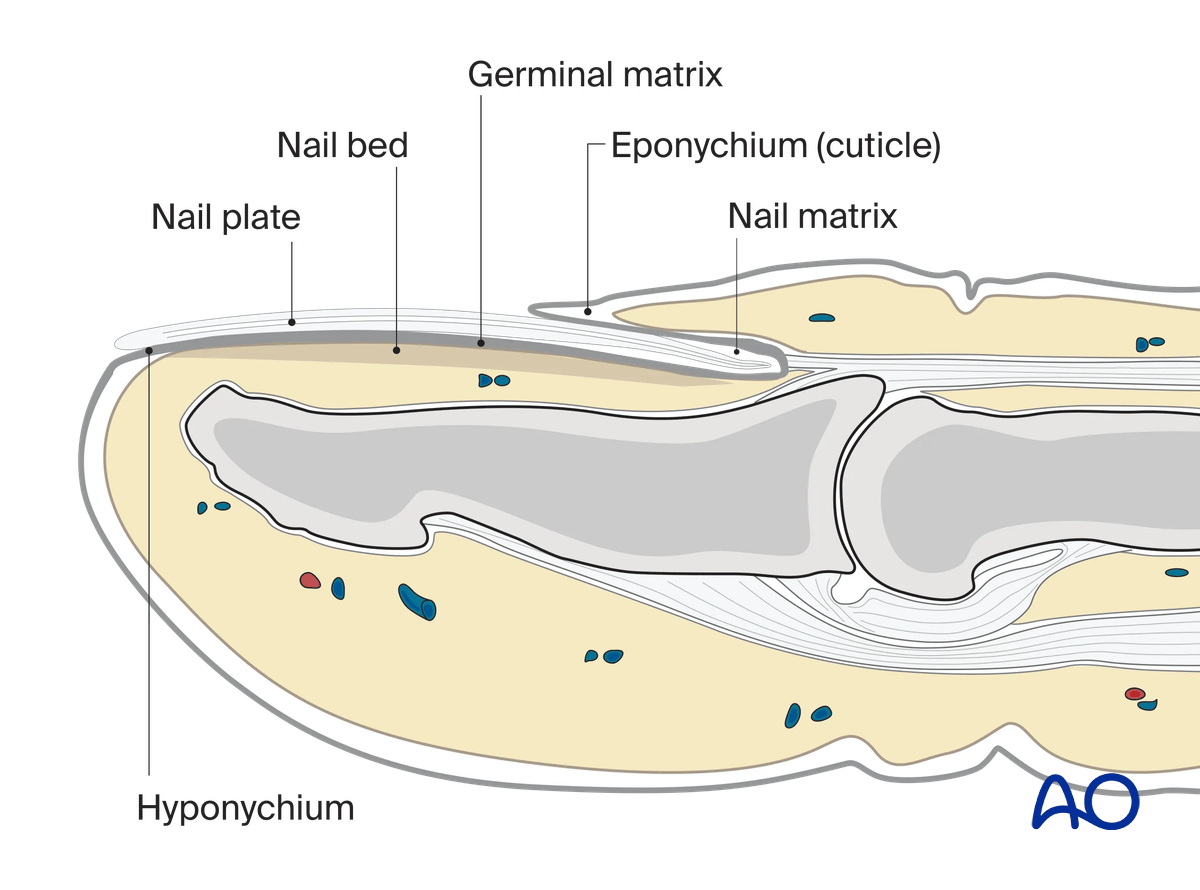
The base of the distal phalanx has a prominent dorsal crest at the insertion of the extensor tendon. The tendon is also adherent to the interphalangeal (IP) joint capsule.
On the palmar surface is the insertion of the flexor pollicis longus tendon.
The flexor tendon occupies the whole width of the base of the distal phalanx. It is made up of two different fibers. The superficial fibers attach to the lateral aspects of the phalanx. The deep fibers run centrally and attach more distal in the palmar aspect of the phalanx.
The volar plate is very flexible, allowing hyperextension of the IP joint and pulp-to-pulp pinch.
The vascularity of the extensor tendons is more precarious than that of the flexor tendons. This prolongs extensor tendon healing time.
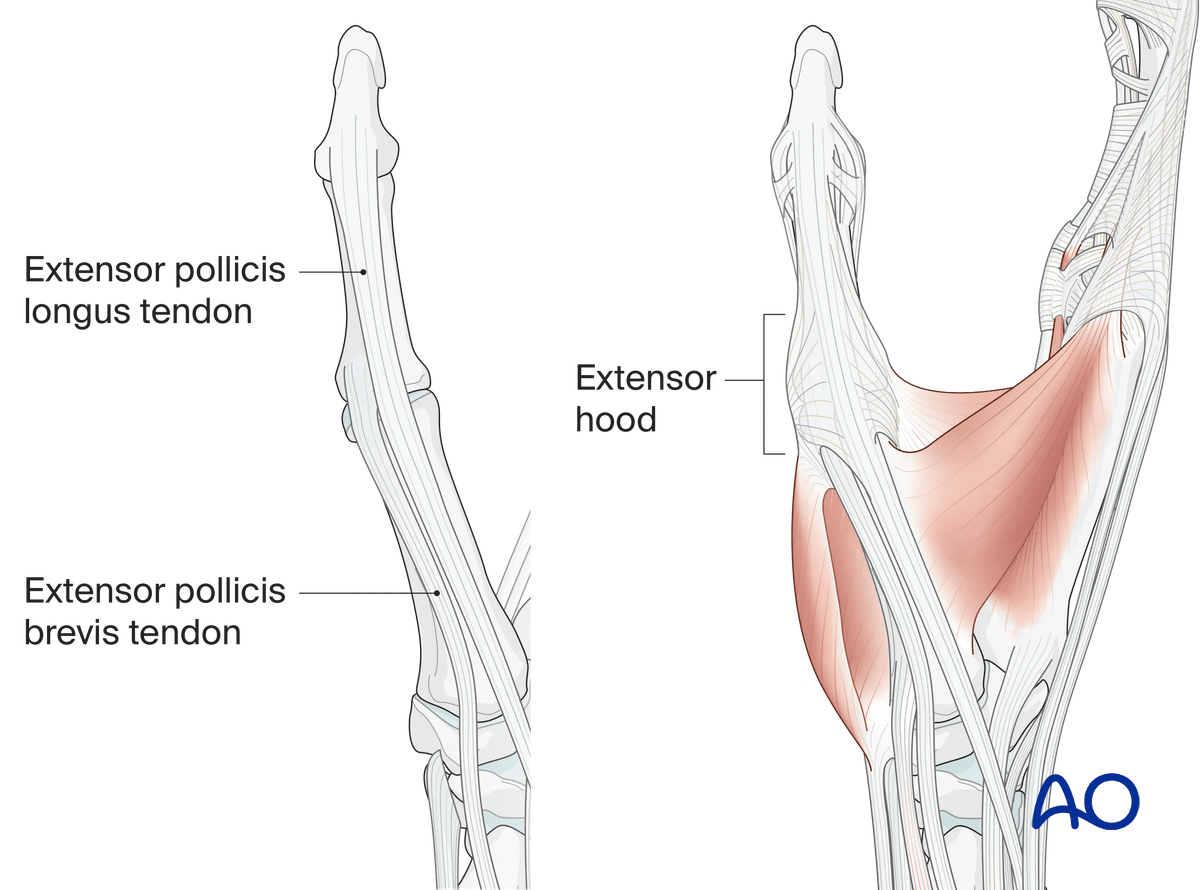
The extensor hood of the thumb consists of the radially located extensor pollicis brevis tendon (insertion: base of the proximal phalanx) and the ulnarly located extensor pollicis longus tendon (insertion at the base of the distal phalanx).
Both tendons are held in position by the sagittal bands at the level of the MCP joint and the extensor hood at the level of the proximal phalanx.
At the level of the MCP joint the abductor pollicis aponeurosis radiates into the extensor hood.
3. Patient preparation
This procedure is usually performed with the patient in a supine position with the arm on a radiolucent side table.
4. Marking K-wire track for joint transfixation
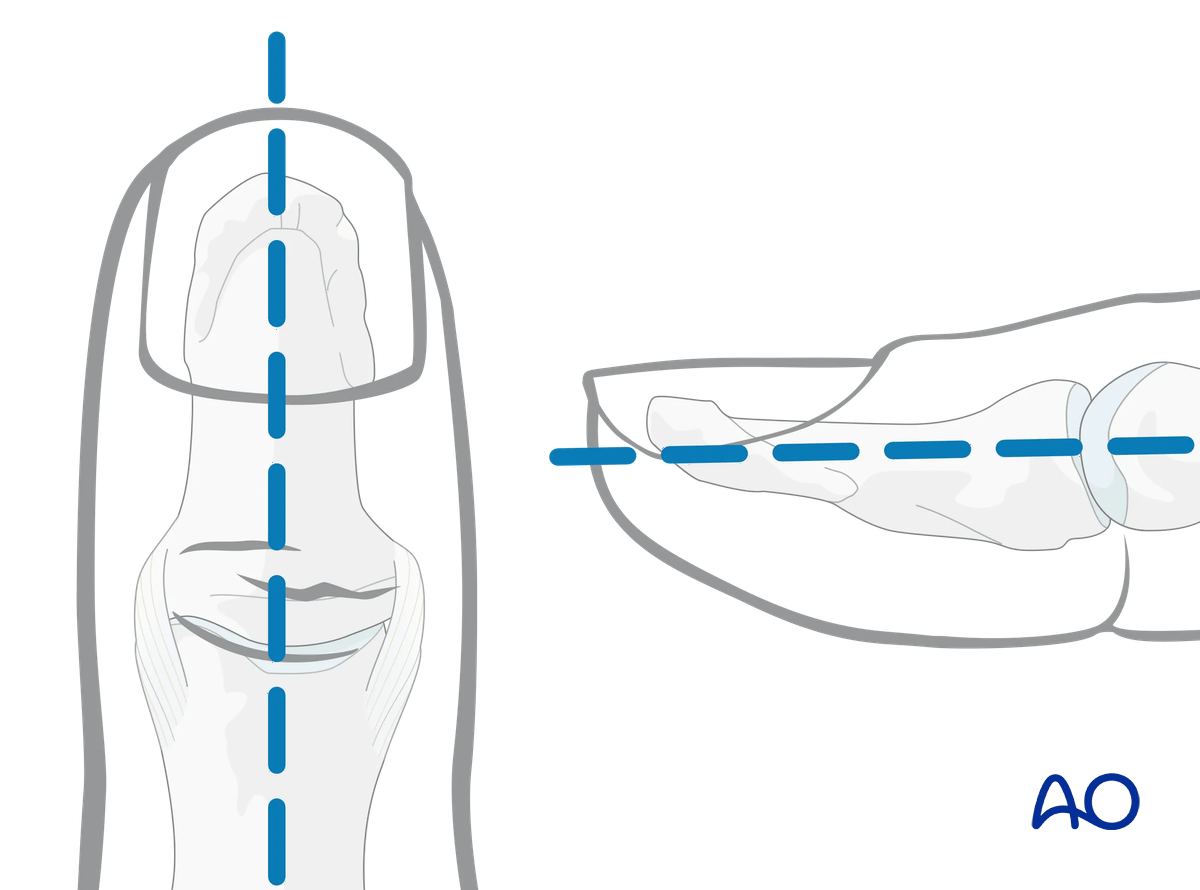
To avoid unnecessary radiation from image intensification, mark the planned track of the axial K-wire on the distal phalanx in both the AP and the lateral aspects.
5. Extension block pinning
Insertion of K-wire
Determine the precise location of the IP joint with an image intensifier.
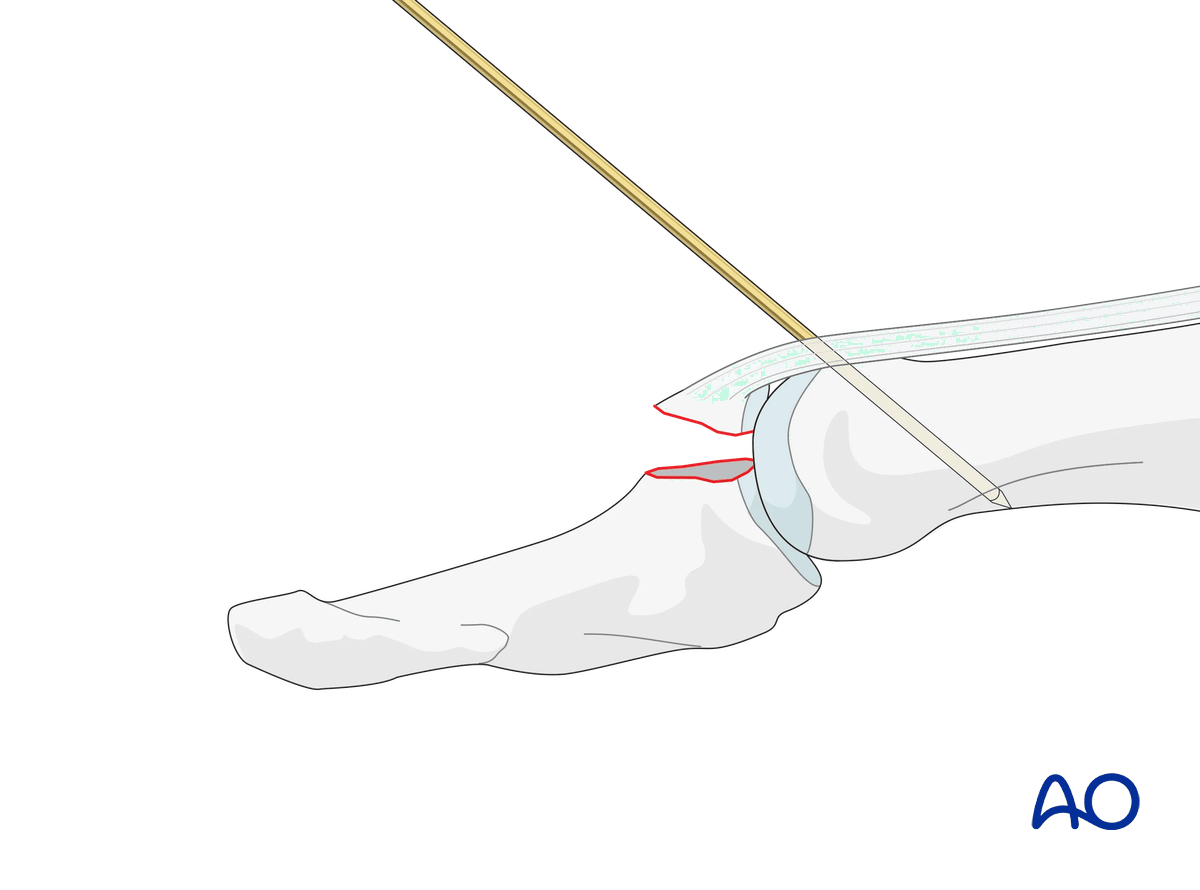
Use a drill guide or a 16G hypodermic needle to insert a 1.4 mm K-wire at an angle of approximately 45° through the terminal extensor tendon into the head of the proximal phalanx. Engage the far cortex.
This K-wire serves as an extension block.
Reduction
Insert an axial K-wire through the tip of the distal phalanx up to the IP.
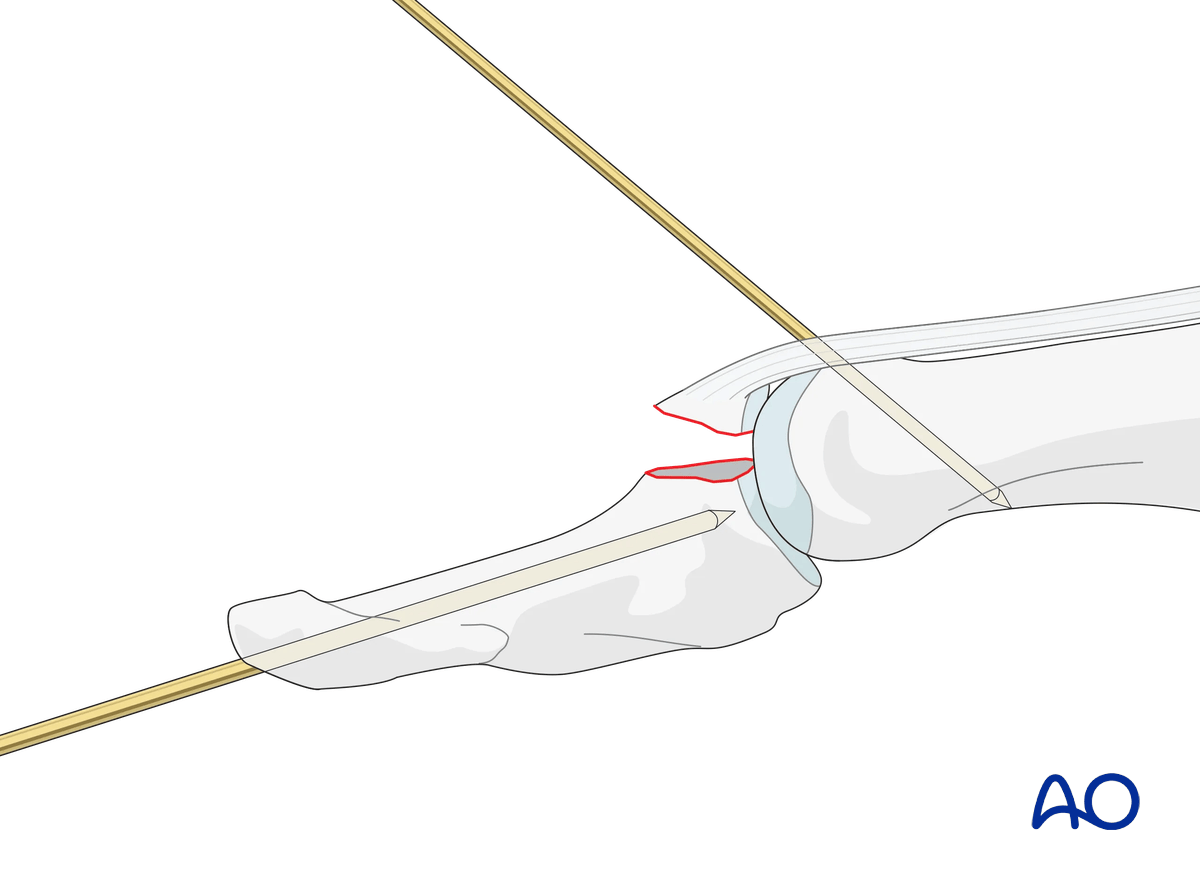
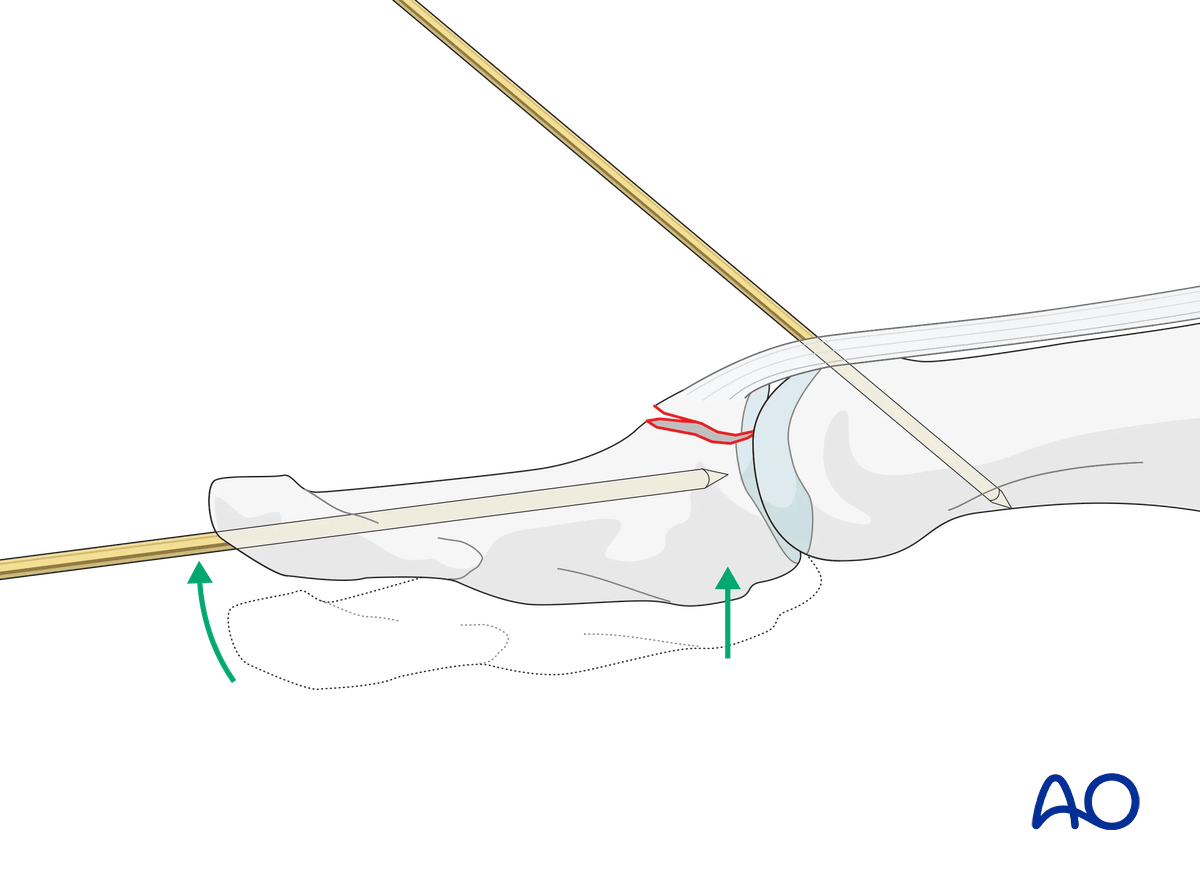
Carefully reduce the fracture by extending the IP joint and shifting the distal fragment.
The axial K-wire may be used as a reduction tool.
Confirm IP joint reduction with an image intensifier in the lateral view.
Joint transfixation
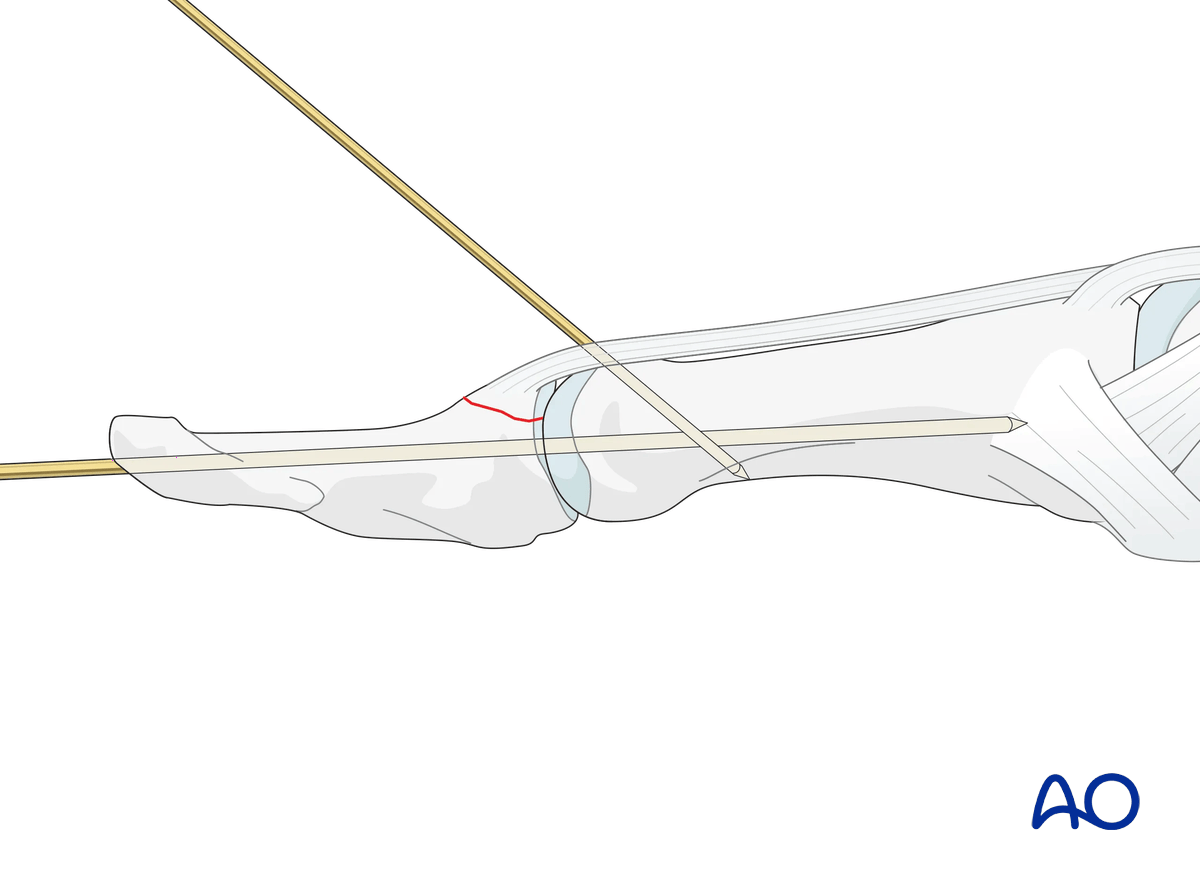
Advance the tip of the axial K-wire across the IP joint into the base of the proximal phalanx. Be careful not to penetrate the MCP joint.
6. Fracture fixation with a K-wire
Insertion of fixation K-wire
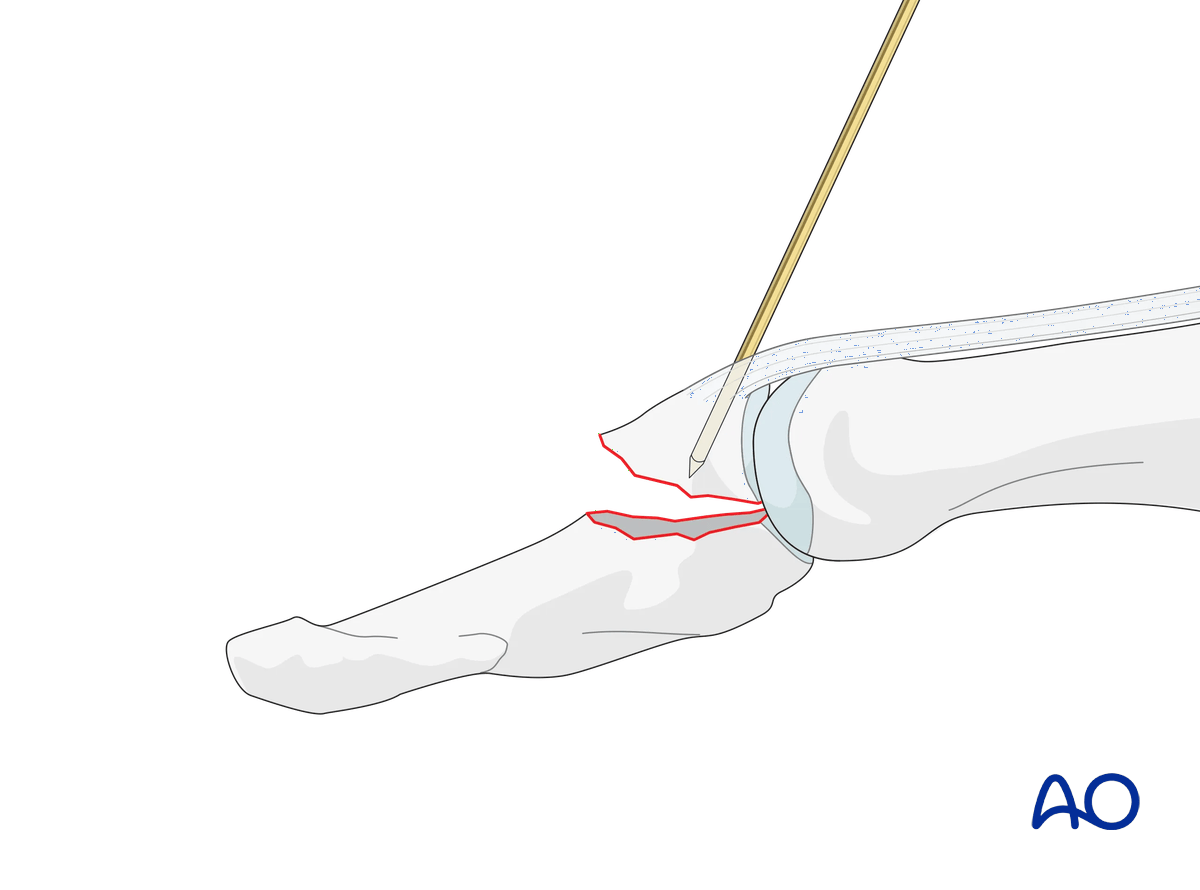
Use image intensification to determine the precise location of the IP joint and the avulsed fragment.
Insert a 1.2 mm K-wire into the avulsed fragment.
Reduction
Insert a second K-wire through the tip of the distal phalanx up to the IP.
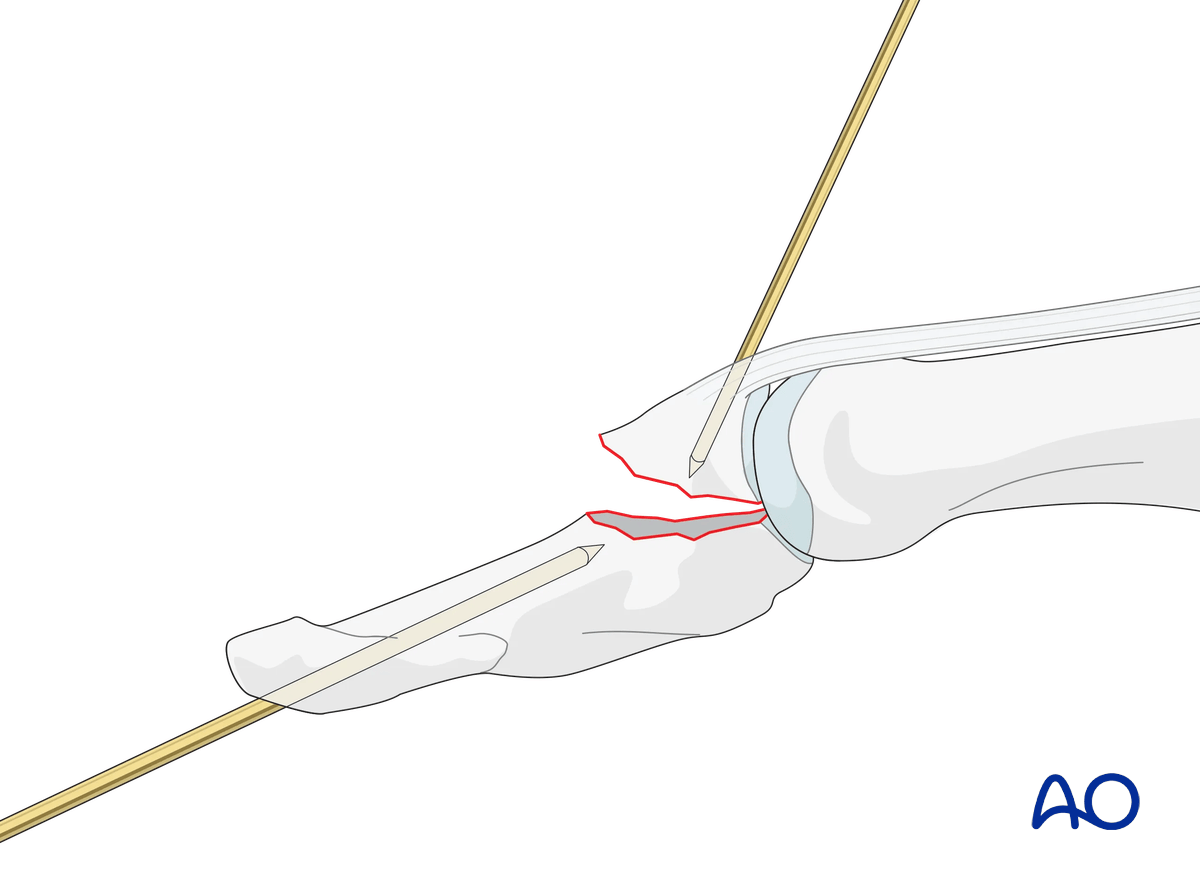
Use the axial K-wire as a reduction tool to extend the IP joint and reduce the fracture.
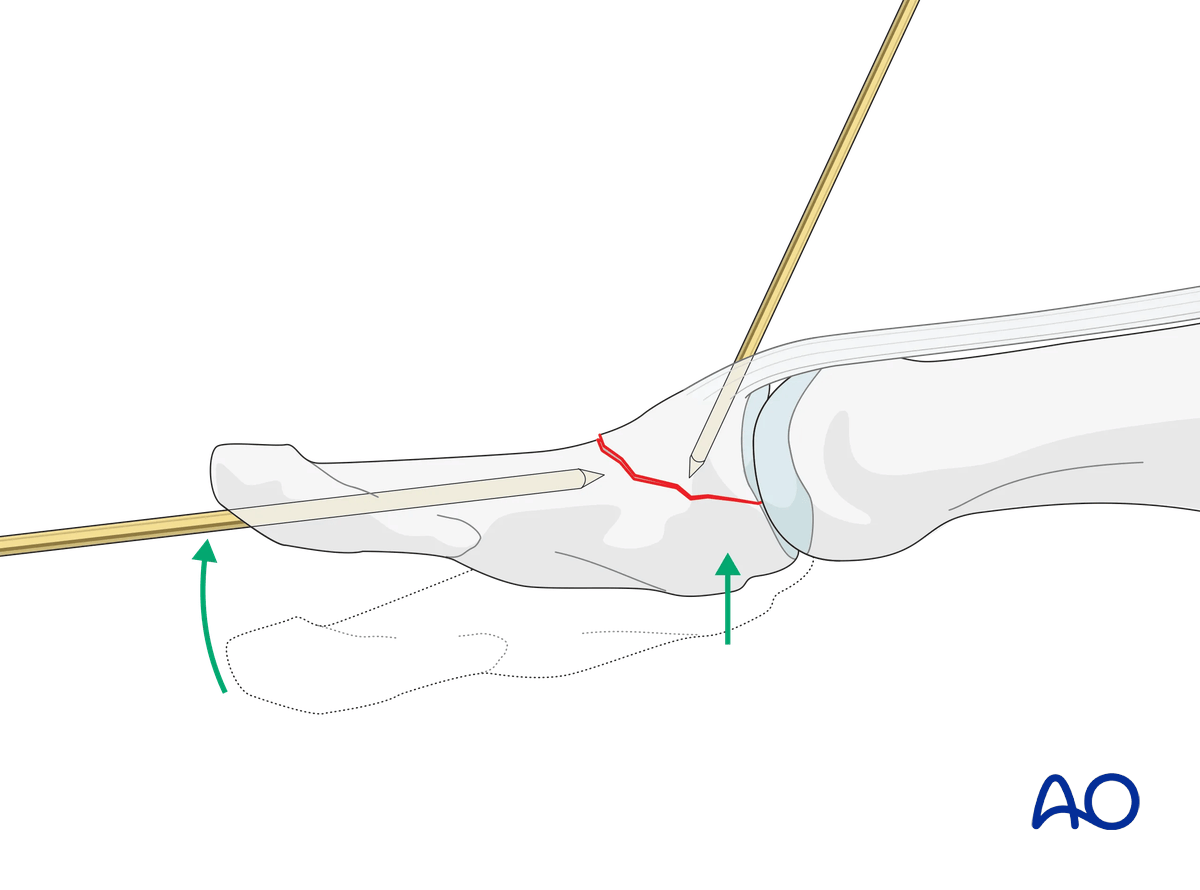
K-wire fixation
Advance the first K-wire into the main fragment, fixing the fracture. Engage the far cortex.
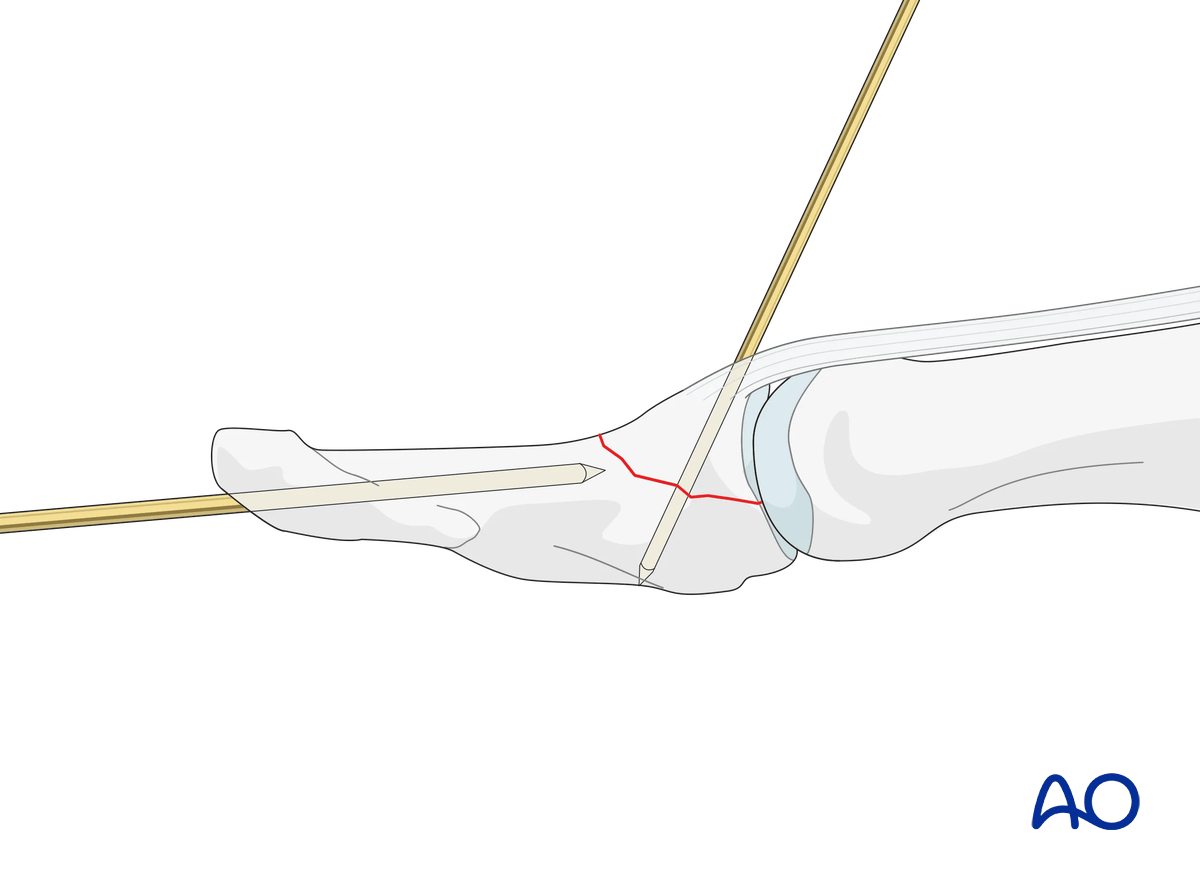
Joint transfixation
Advance the tip of the axial K-wire across the IP joint into the base of the proximal phalanx. Be careful not to penetrate the MCP joint.
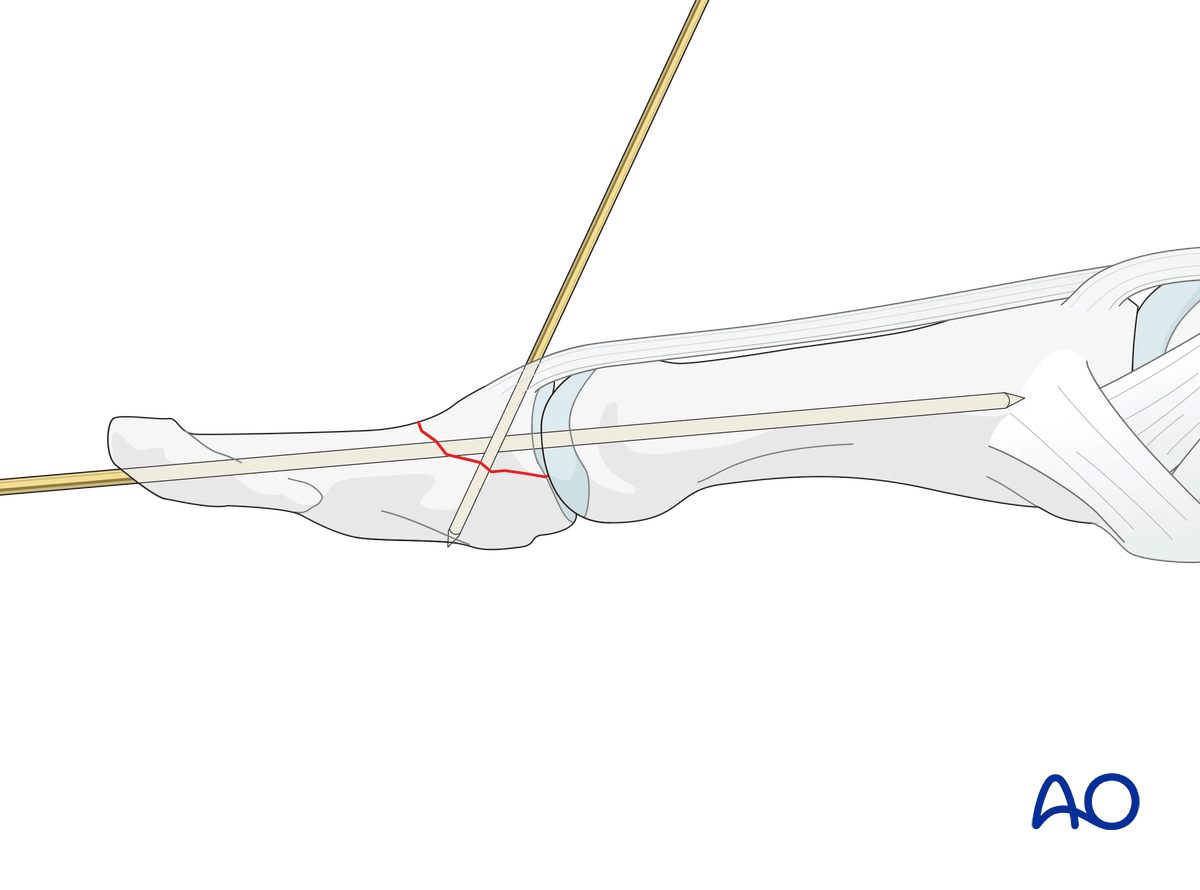
7. Cutting the K-wires
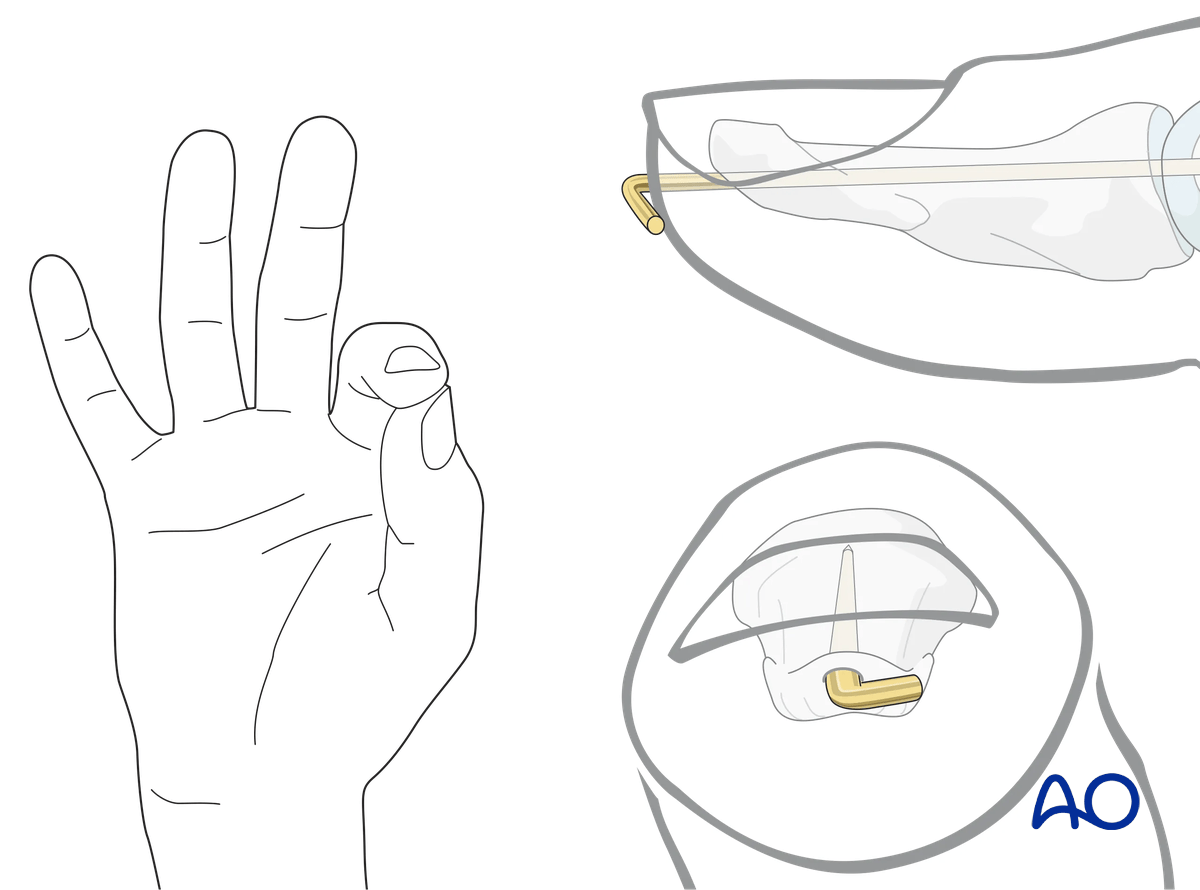
Cut the K-wire so that it protrudes through the skin.
Leaving the K-wire to protrude through the skin in this way has the advantage of its being easy to remove. The disadvantages are patient discomfort and risk of pin-track infection.
Make sure that the bent end does not irritate or compress the skin.
8. Splinting
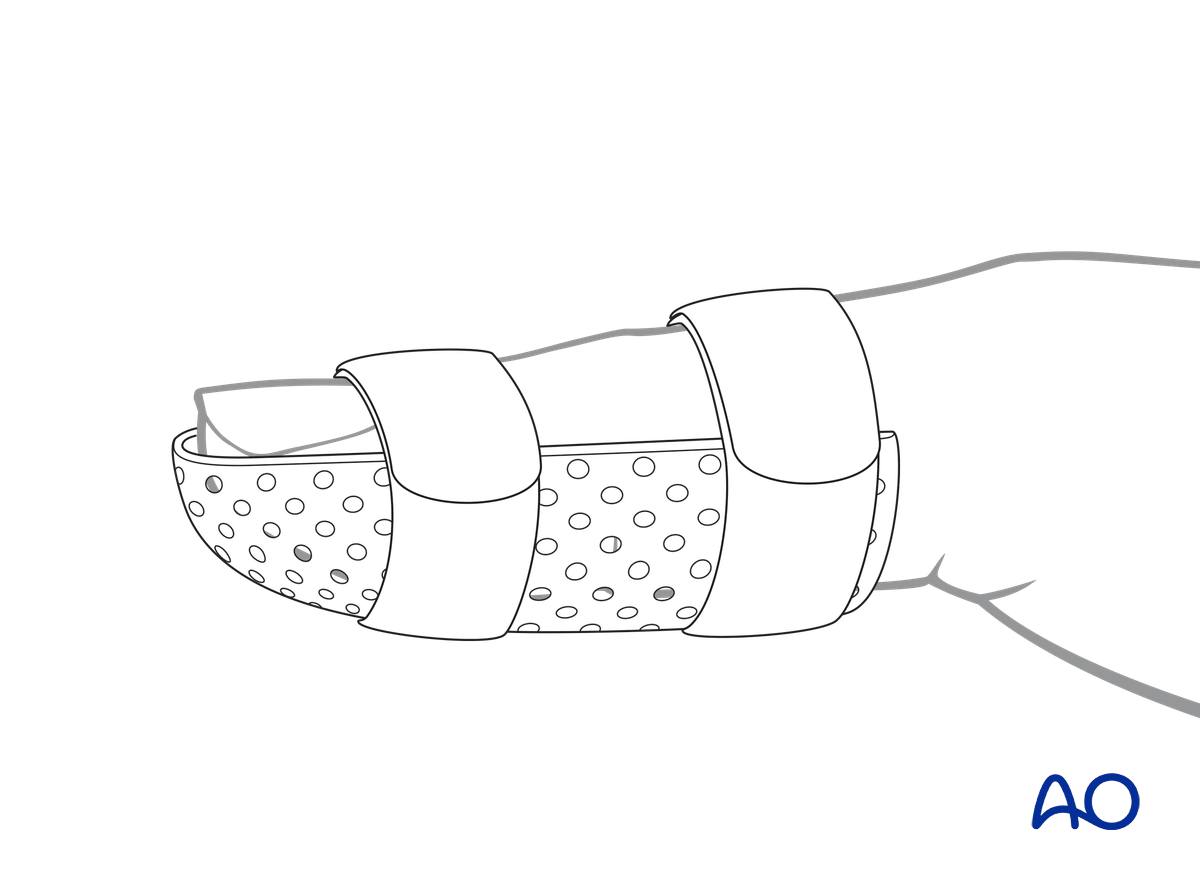
Apply an IP joint splint, leaving the MCP joint free, to protect the K-wire from breakage.
A custom thermoplastic splint has the advantage that it is adapted better to the shape of the thumb and is easier to change.
9. Aftercare
Healing phases
The aftercare can be divided into four phases of healing:
- Inflammatory phase (week 1–3)
- Early repair phase (week 4–6)
- Late repair and early tissue remodeling phase (week 7–12)
- Remodeling and reintegration phase (week 13 onwards)
Full details on each healing phase can be found in the chapter Postoperative treatment of thumb injuries.
Management of swelling
The splint allows for movement at the MCP joint and helps with pain and edema control. The arm should be actively elevated to help reduce the swelling.
Mobilization
Aftertreatment depends on the size of the fragment, the bone quality, and the stability gained by the fixation.
Hand therapy is recommended to prevent soft-tissue atrophy and joint contracture, which leads to a poor outcome, and subsequent treatment is difficult.
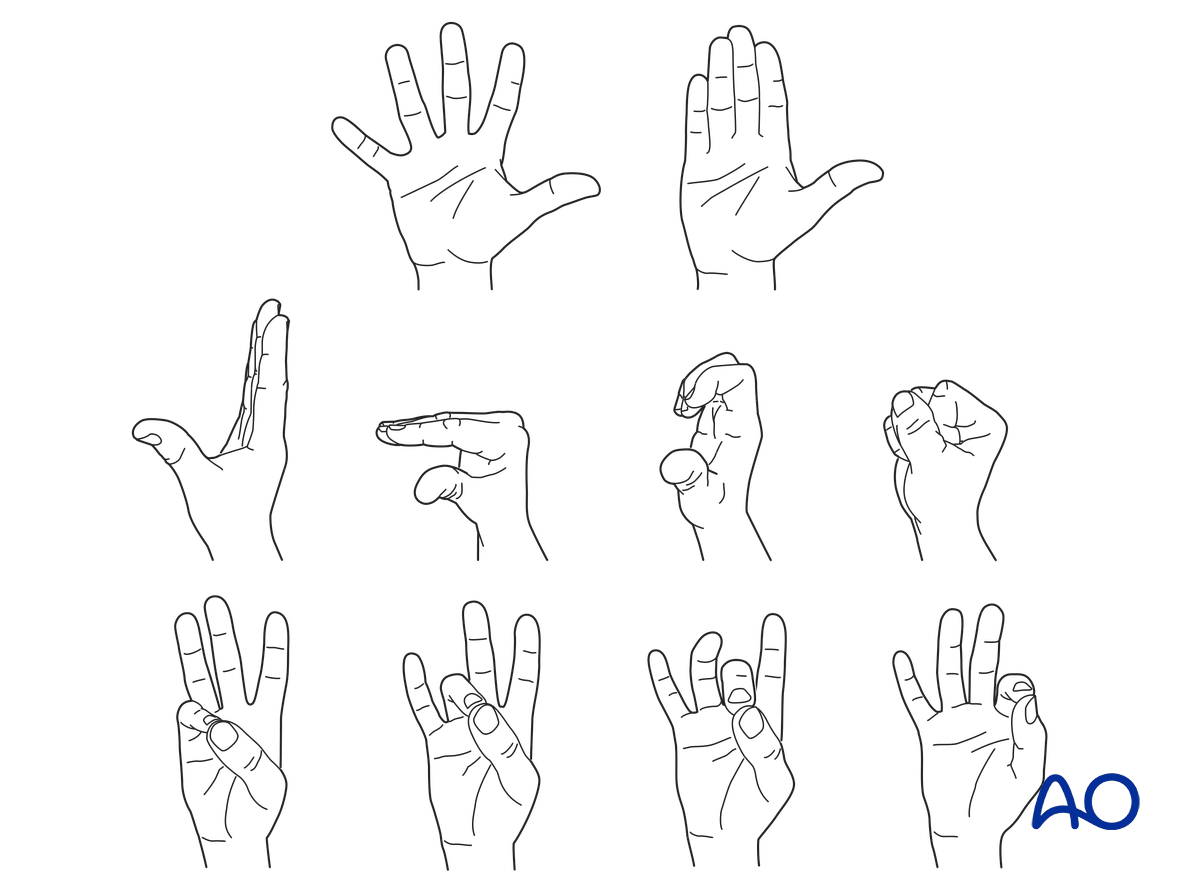
Functional exercises of the nonimmobilized joints should be started immediately to keep uninjured joints mobile.
Active motion of the IP joint is permitted after removal of the K-wire. Passive motion should be postponed for 8–10 weeks to avoid the risk of recurrent mallet deformity.
K-wire removal
Depending on the injury, the K-wires may be removed, usually after 6 weeks.
At this stage, X-rays should be taken to confirm healing.


