Radiopalmar approach to the metacarpal base of the thumb
1. Introduction
Indications
This approach, also known as the Wagner approach, is indicated for:
- Intraarticular fractures of the first carpometacarpal (CMC) joint, such as the Bennett or Rolando injuries
- Irreducible or chronic CMC joint dislocations
- Basal metacarpal fractures
- Trapezial fractures
AO teaching video
Thumb—Trapeziometacarpal joint—Radiopalmar approach
Renato M Fricker, Klaus Lowka, Regula Steiger
This video demonstrates the radiopalmar approach to the thumb and the trapeziometacarpal joint.
2. Surgical anatomy
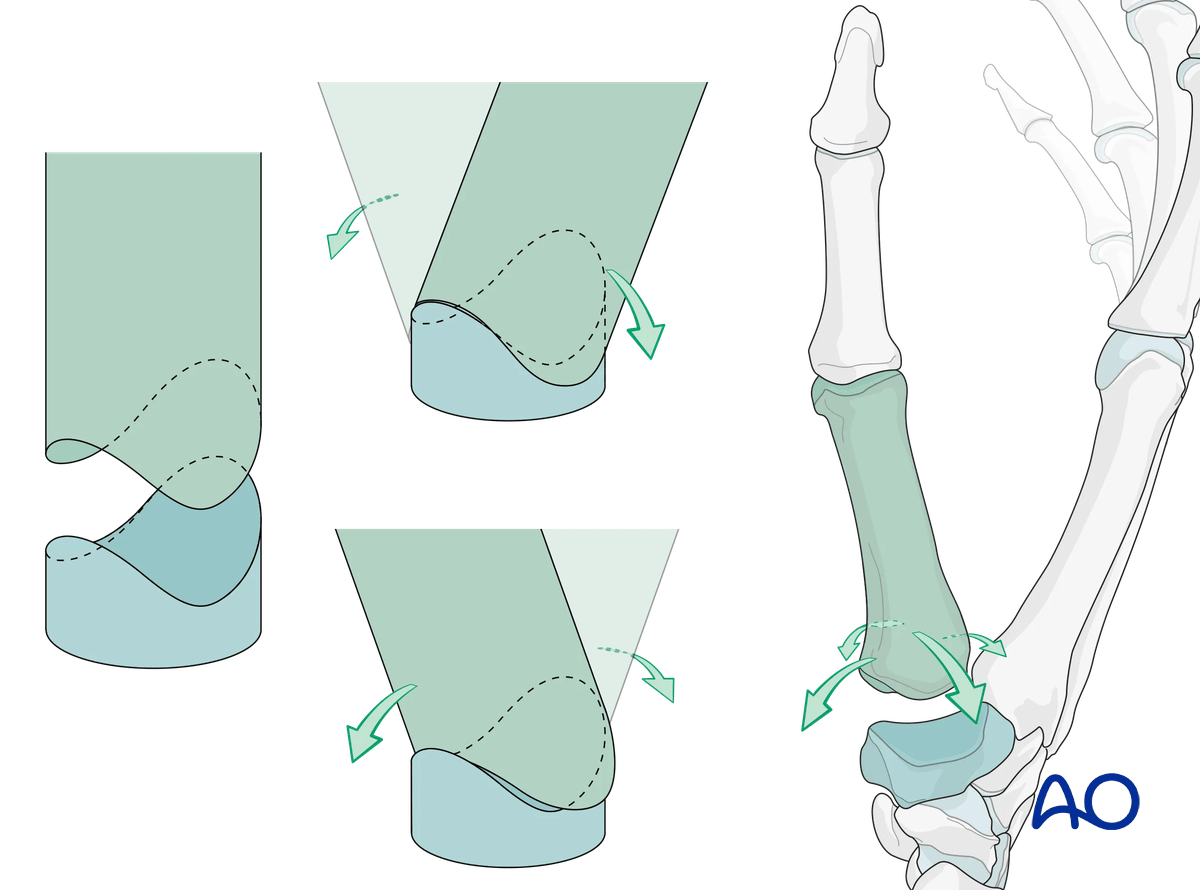
The joint surfaces of the trapezium and thumb metacarpal resemble two reciprocally interlocking saddles.
This articular geometry, the ligamentous support system, and the thumb muscles all work synergistically to enable opposition of the thumb to the fingers.
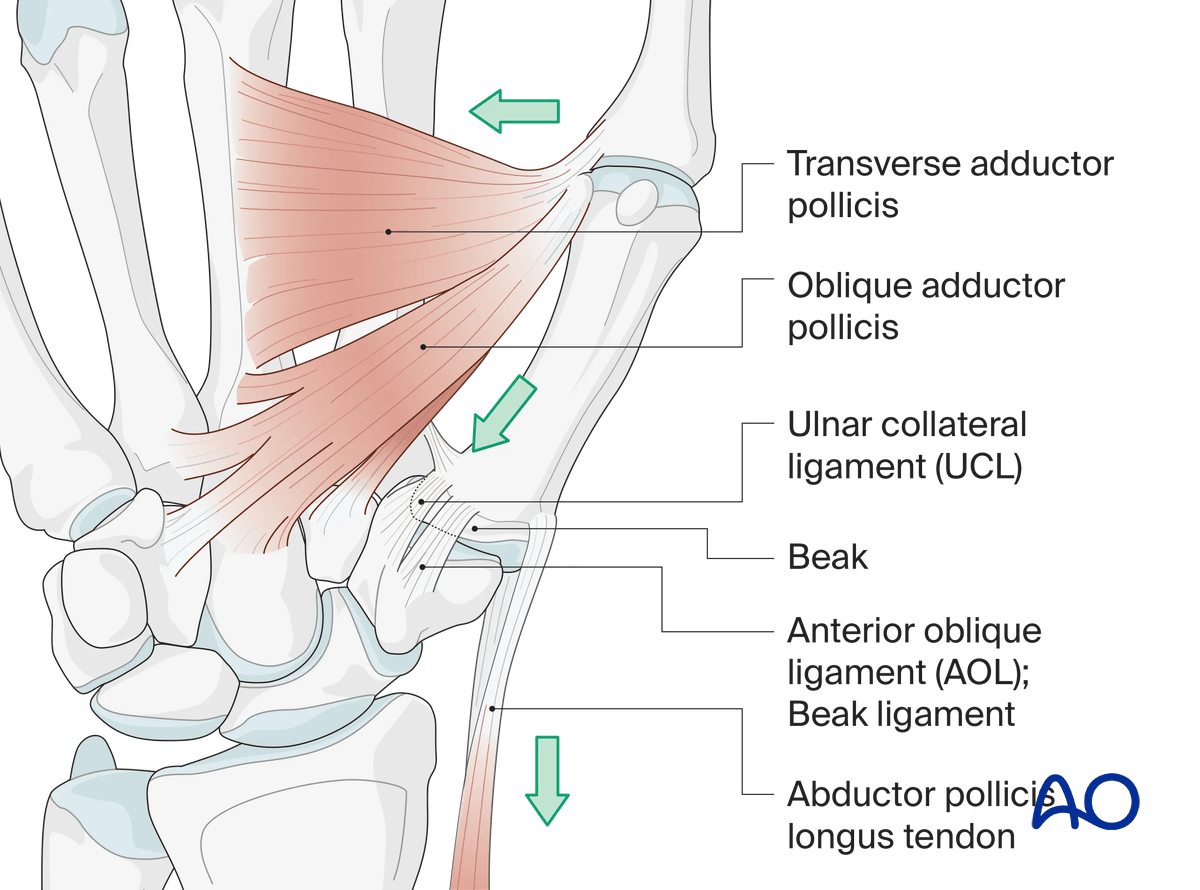
The strong ulnar collateral ligament is essential as a stabilizer of the base of the thumb metacarpal: it inserts into the articular margin of the volar beak on the ulnar aspect of the first metacarpal base.
The abductor pollicis longus (APL) tendon inserts on the radial side of the metacarpal base.
The APL exerts a force which pulls the thumb in a palmar and ulnar direction.
These muscle forces and the strong attachments of the ulnar collateral ligament create the typical deformity at the base of the thumb in Bennett’s fractures.
3. Skin incision
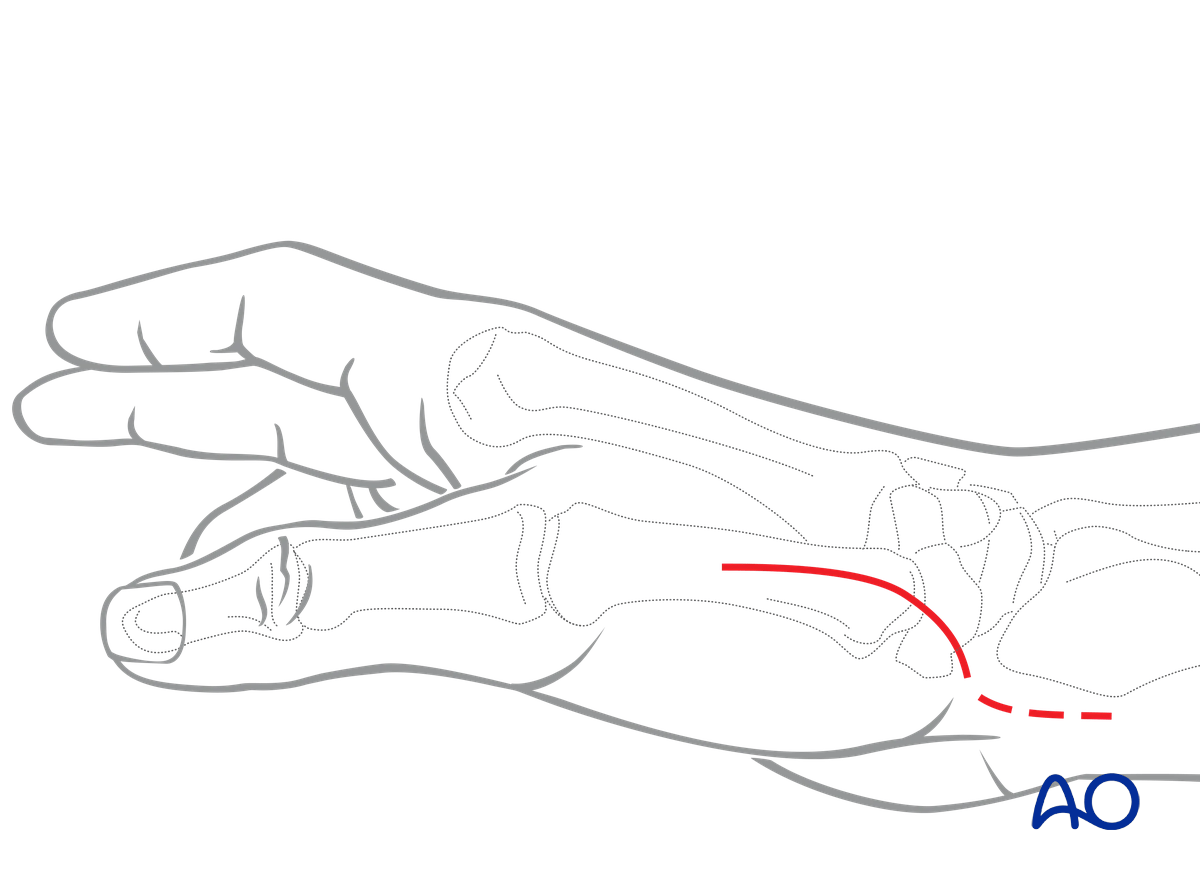
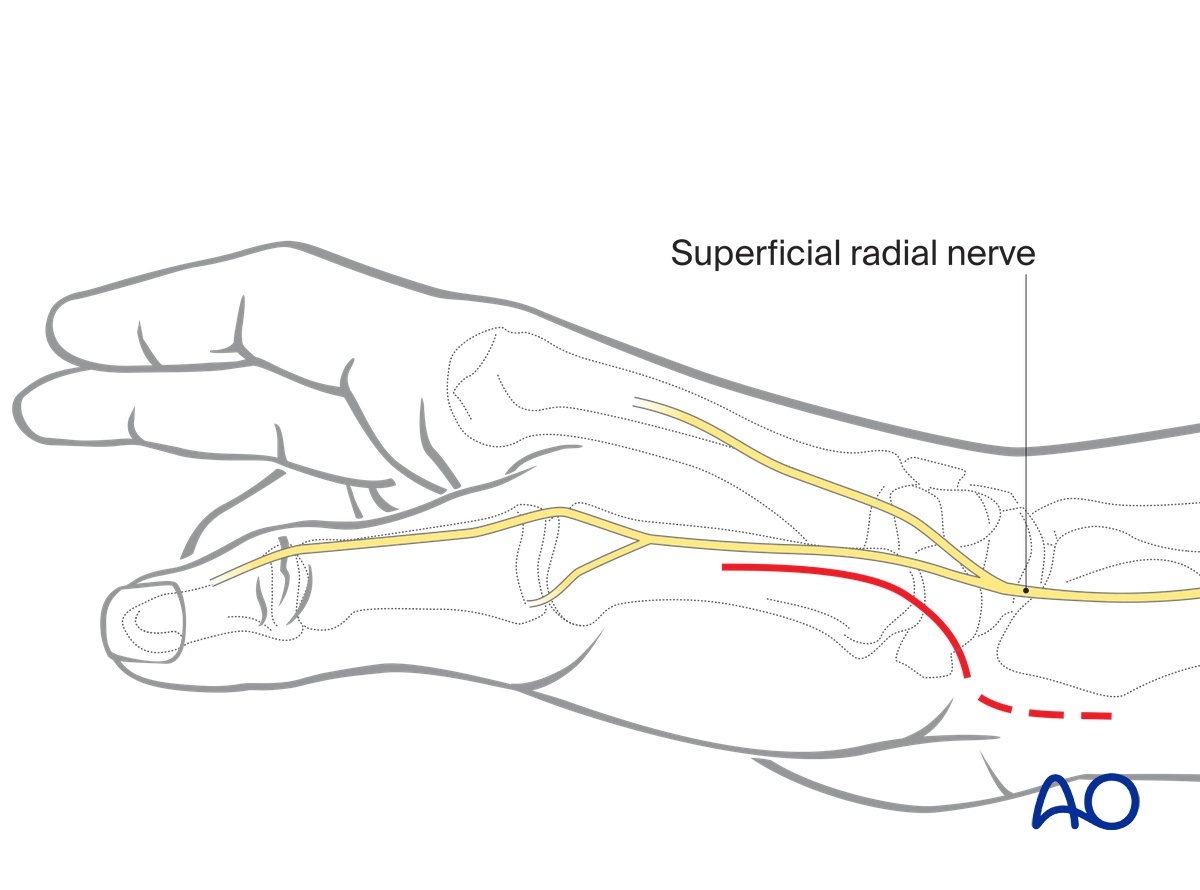
Perform a straight incision in the radial aspect of the thenar eminence at the transition between the dorsal and palmar (glabrous or non-hairy) skin. It starts in the middle of the metacarpal and curves palmarly about 1 cm distal to the wrist crease.
If needed, the incision can be extended proximally between the flexor carpi radialis (FCR) tendon and radial artery (modified Henry interval). This allows for the harvest of a distally based APL tendon graft, eg, for CMC ligament reconstruction.
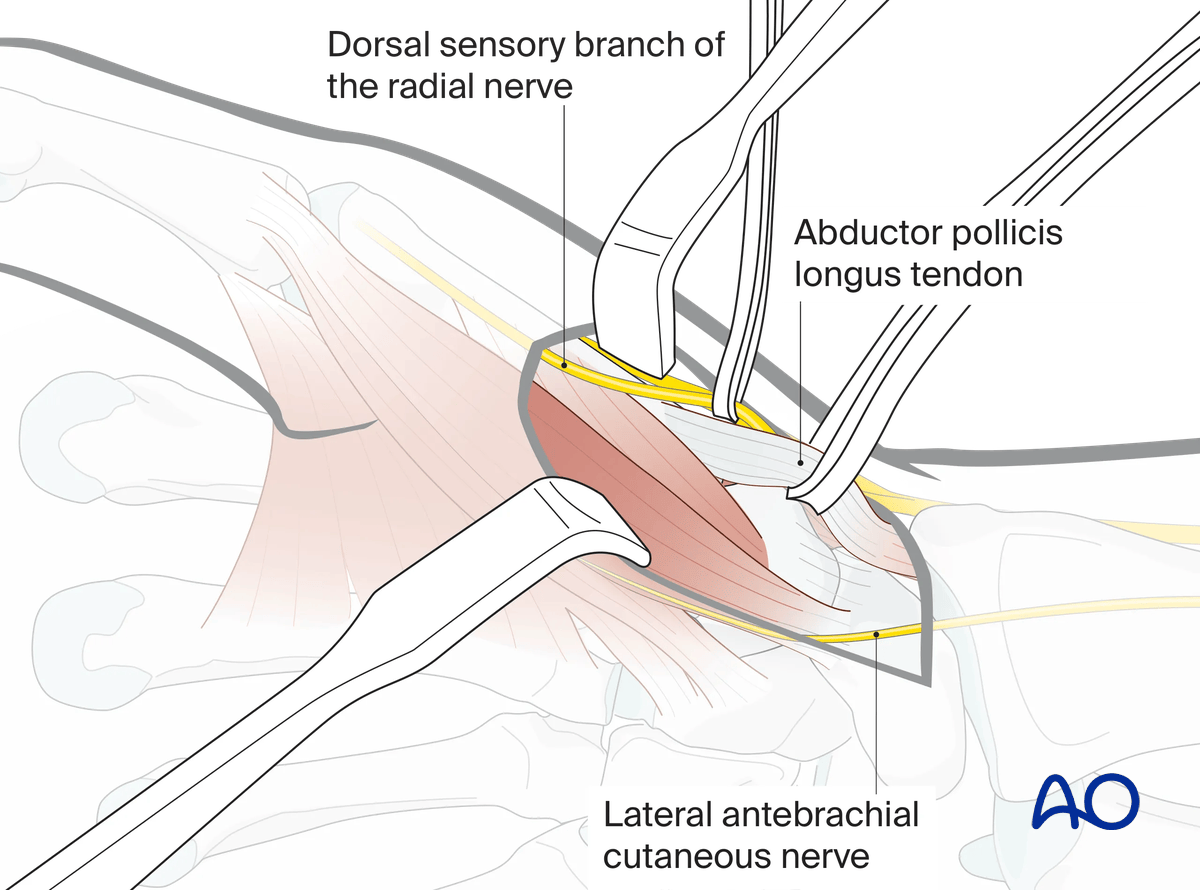
The dorsoradial sensory branch of the superficial radial nerve is located dorsal to the incision and should be identified and protected. There might be distal branches of the lateral antebrachial cutaneous nerve.
4. Elevation of the flap
Elevate the flaps of skin and subcutaneous tissue by blunt dissection, identifying and protecting the dorsal sensory branches of the superficial radial nerve and the APL tendon. Gentle retraction with elastic vessel loops aids exposure.
Both structures can be retracted in a dorsal direction.
5. Detachment of the thenar muscles
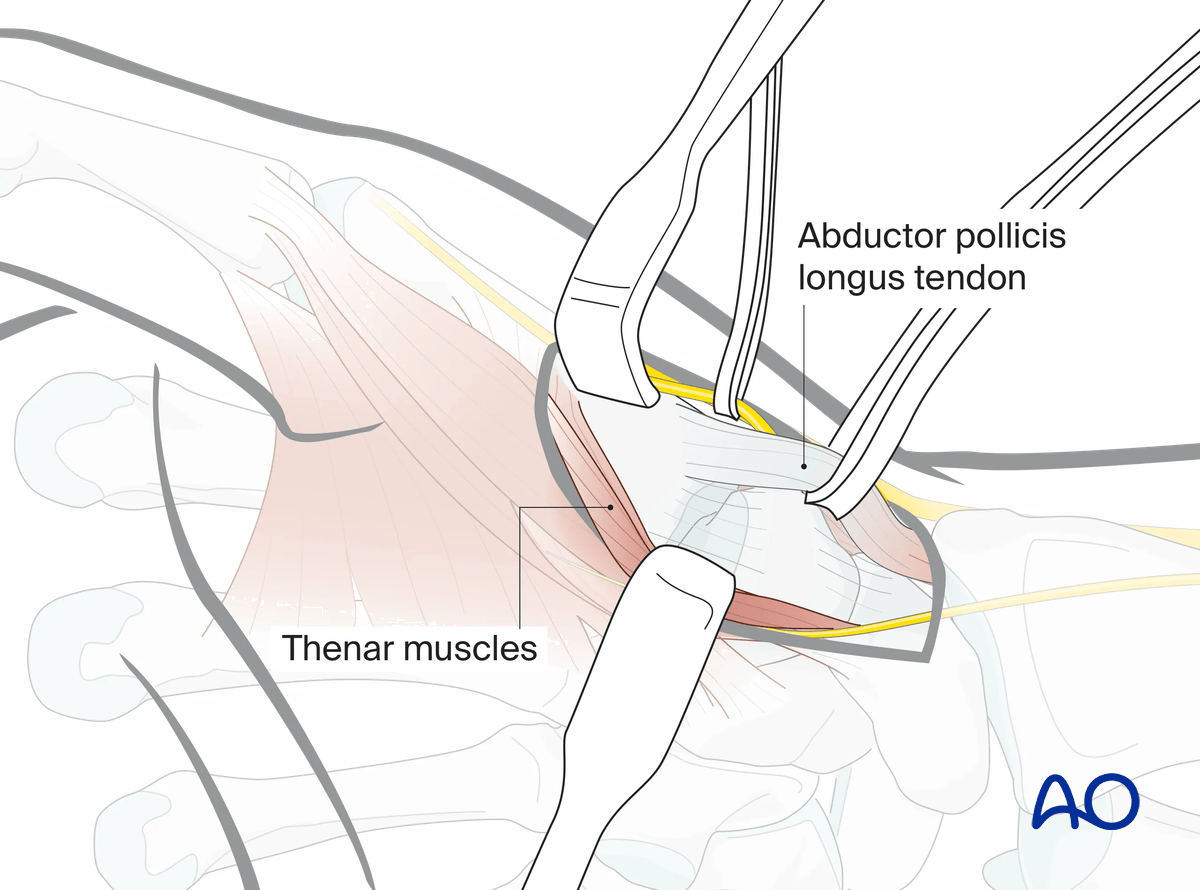
After retracting these structures, the thenar muscles are exposed. Detach them from their origins at the base of the first metacarpal with a sharp periosteal elevator and reflect them in a palmar direction.
6. Capsulotomy
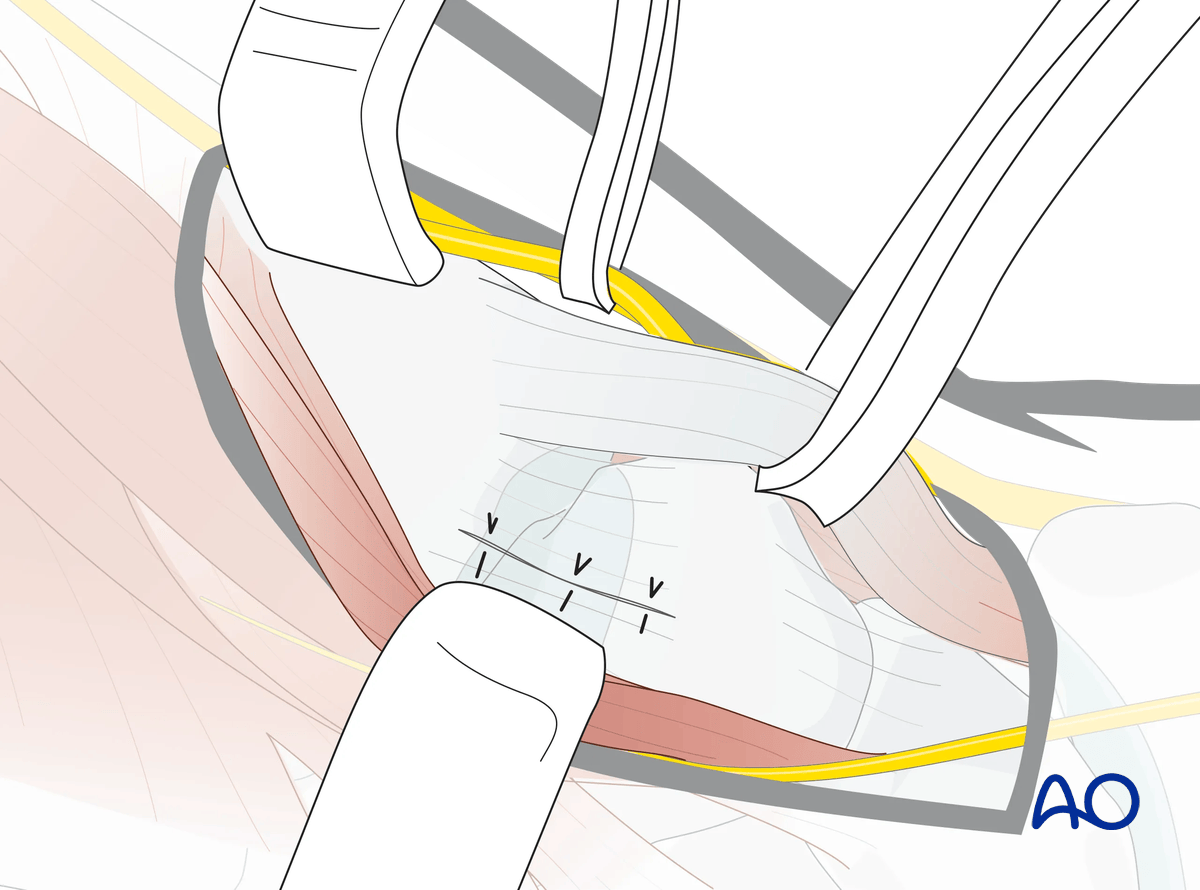
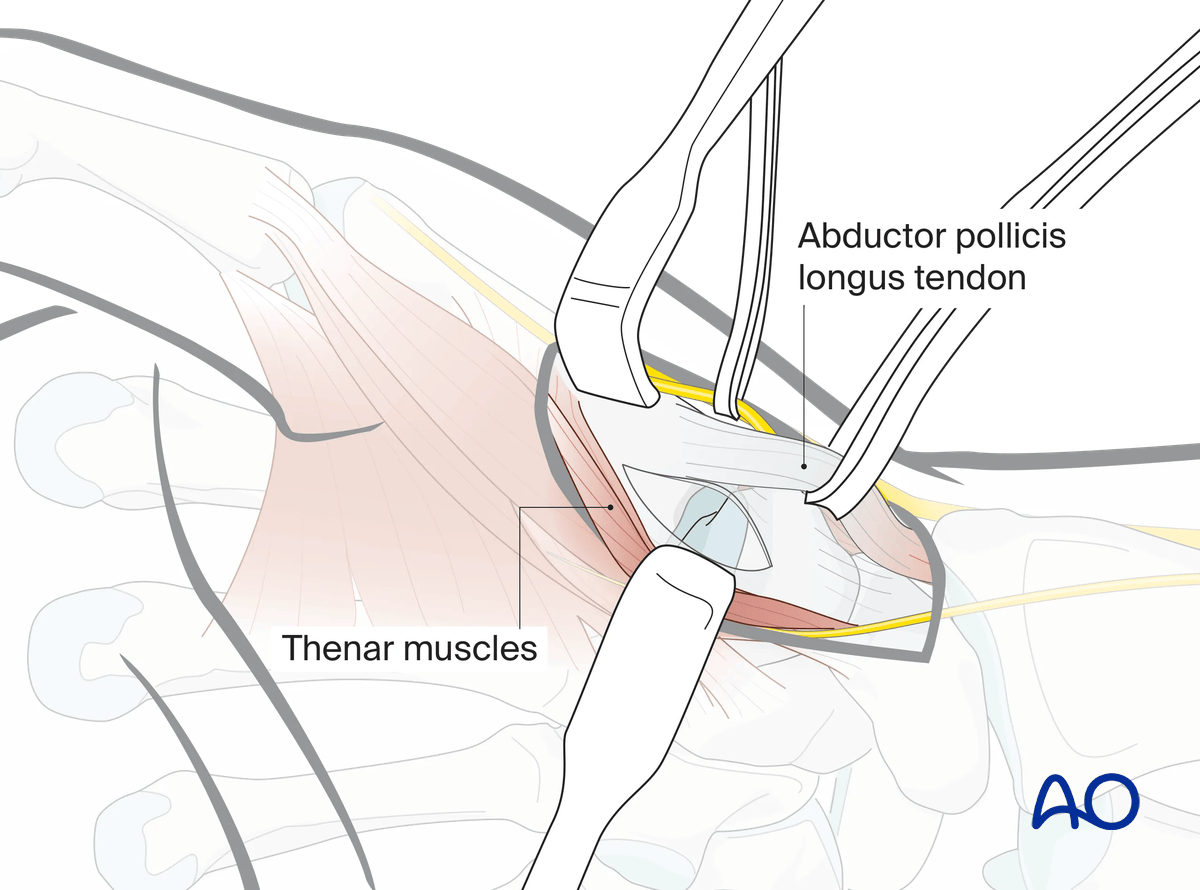
Perform a transverse or longitudinal capsulotomy to expose the joint.
7. Inspection of the joint
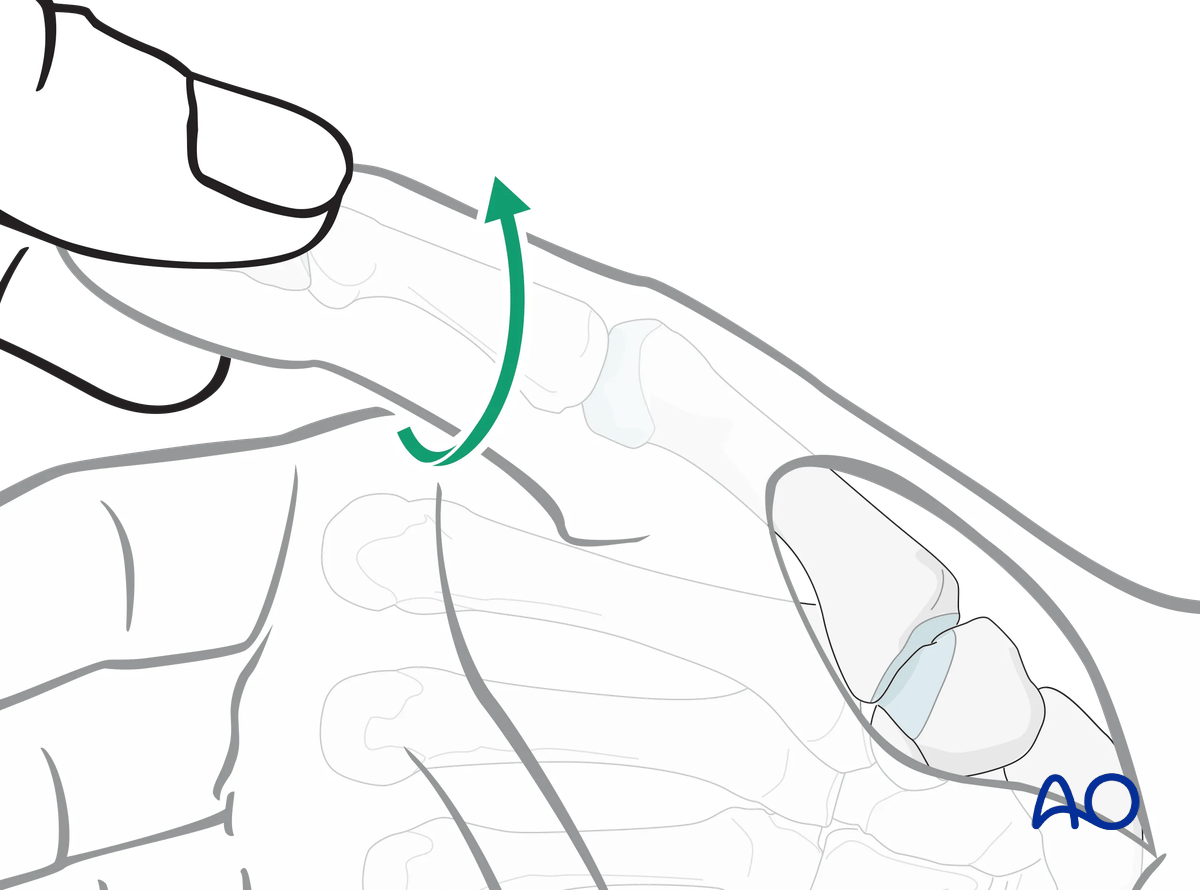
Inspect the joint by rotating the thumb into pronation and supination, whilst exerting longitudinal traction. This maneuver also helps to assess the fracture geometry, and to reduce fracture fragments.
8. Wound closure
Close the capsule together with detached thenar muscle with fine resorbable sutures (either interrupted or uninterrupted).