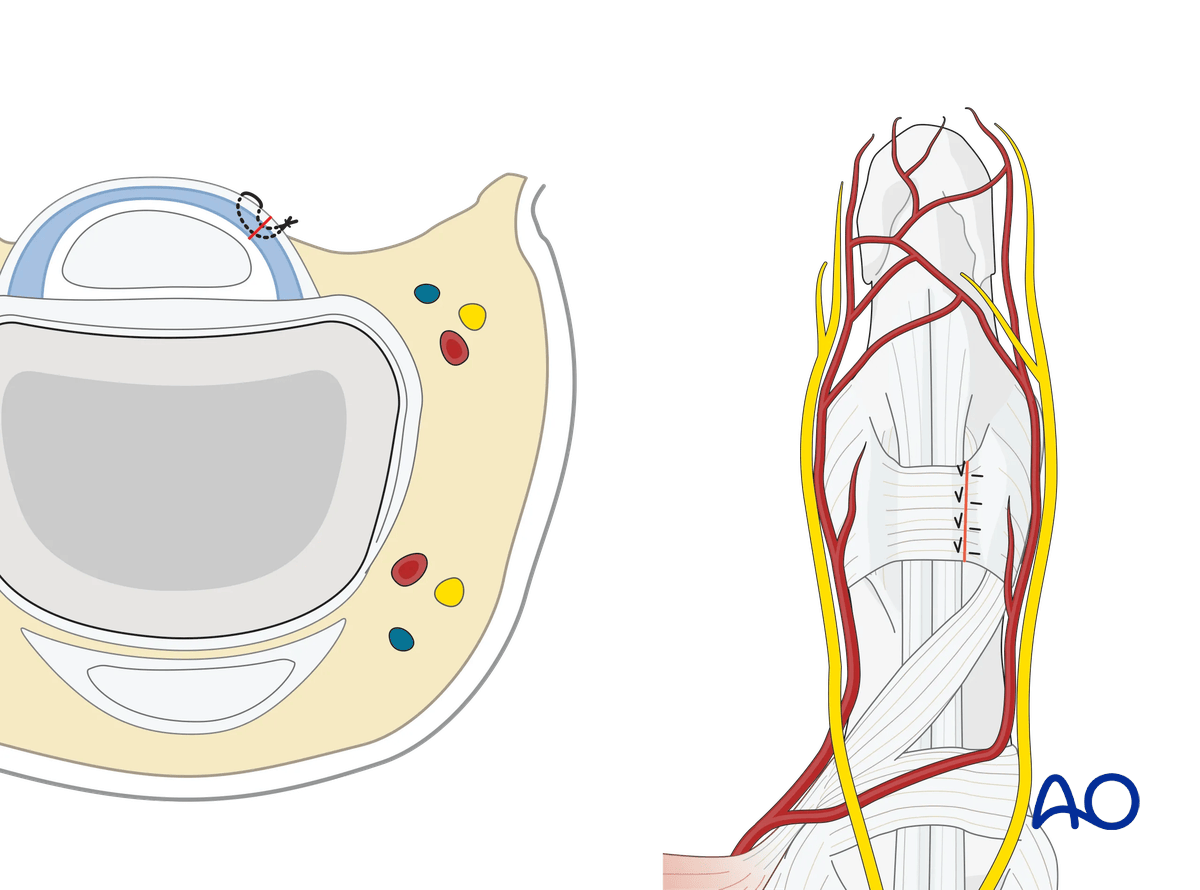
Palmar approach to the IP joint of the thumb
1. Indications
The palmar approach to the interphalangeal (IP) joint is indicated for intraarticular fractures of the palmar base of the distal phalanx, eg, caused by avulsion injuries of the flexor pollicis longus tendon.
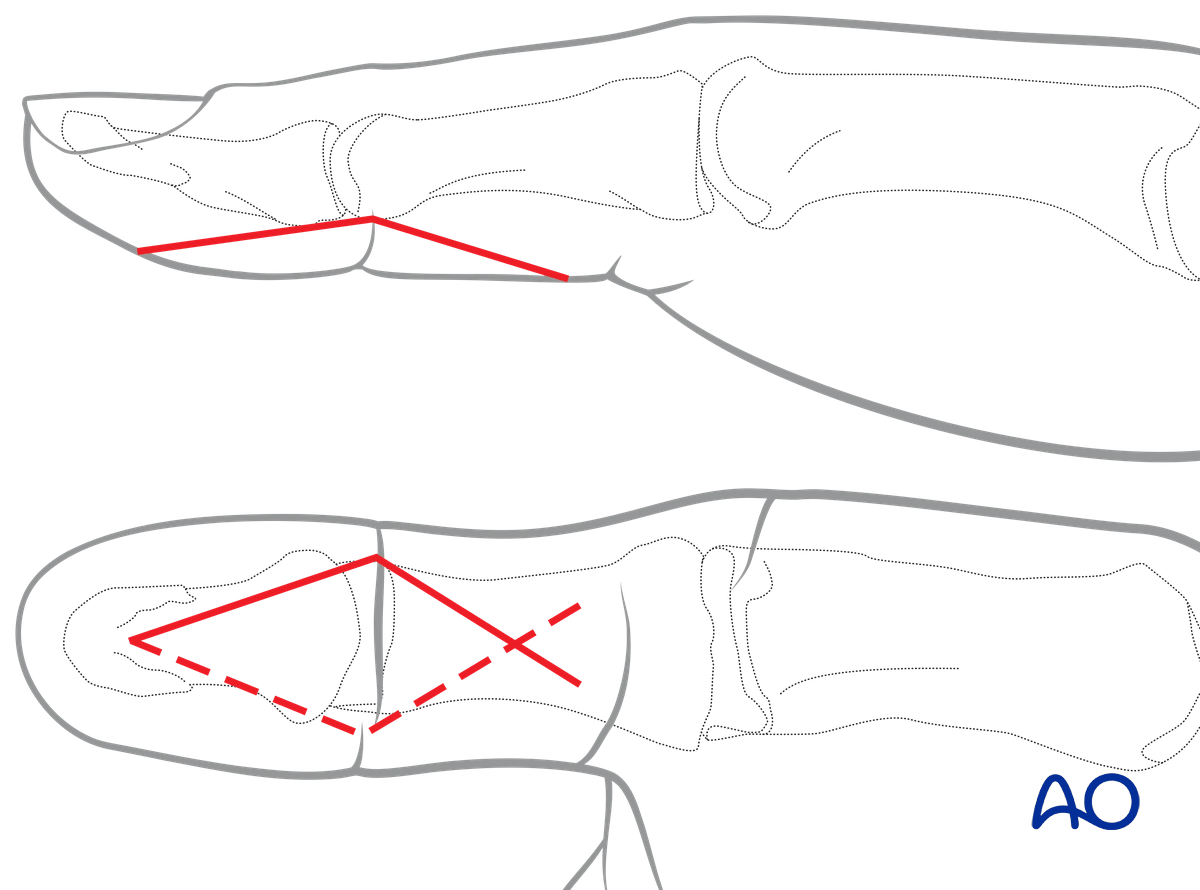
2. Surgical anatomy
The base of the distal phalanx has a prominent dorsal crest at the insertion of the extensor tendon. The tendon is also adherent to the IP joint capsule.
The flexor pollicis longus tendon is inserted into the palmar surface of the distal phalanx.
The flexor tendon occupies the whole width of the base of the distal phalanx. It is made up of two different fibers. The superficial fibers attach to the lateral aspects of the phalanx. The deep fibers run centrally and attach more distally on the palmar aspect of the phalanx.
The volar plate is very flexible, allowing hyperextension of the IP joint and pulp-to-pulp pinch.
The vascularity of the extensor tendon is more precarious than that of the flexor tendons. This prolongs extensor tendon healing time.
The digital nerve and artery should be identified and protected.
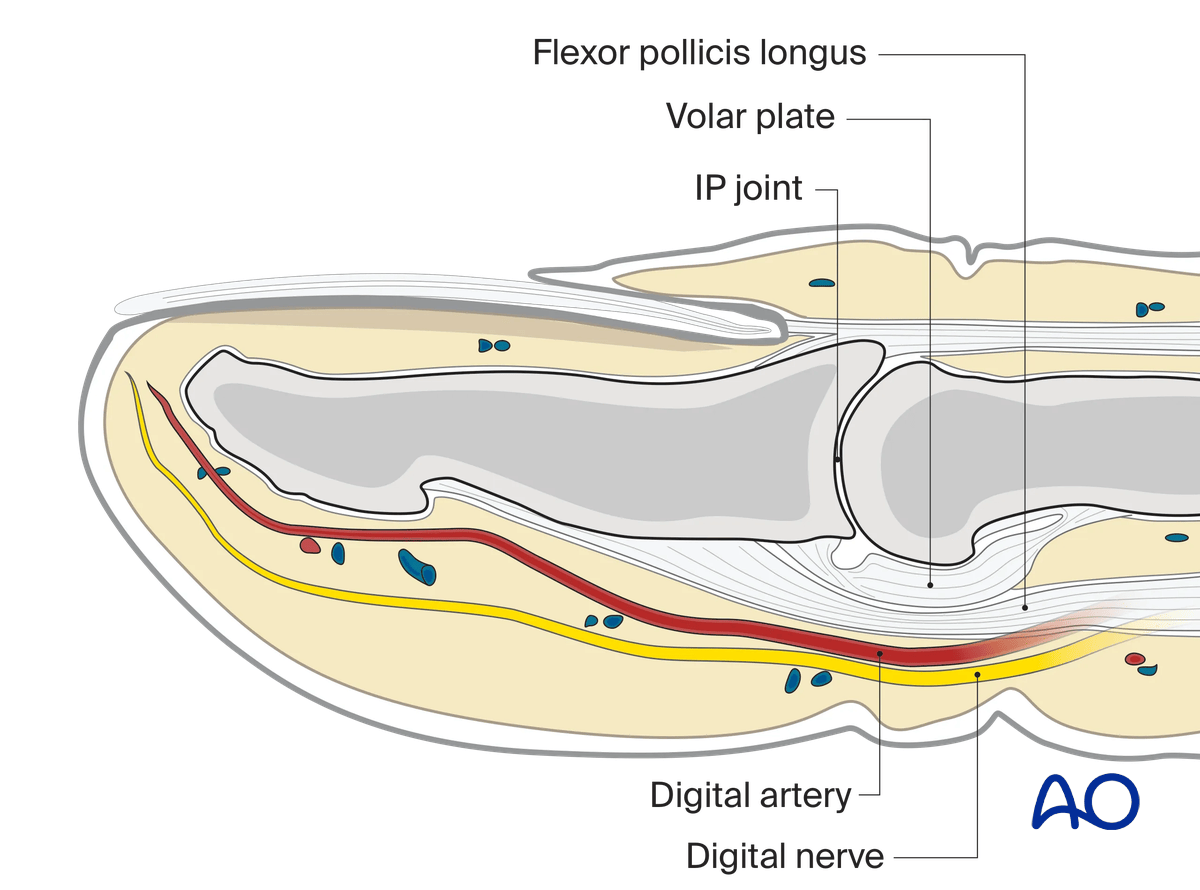
3. Skin incision
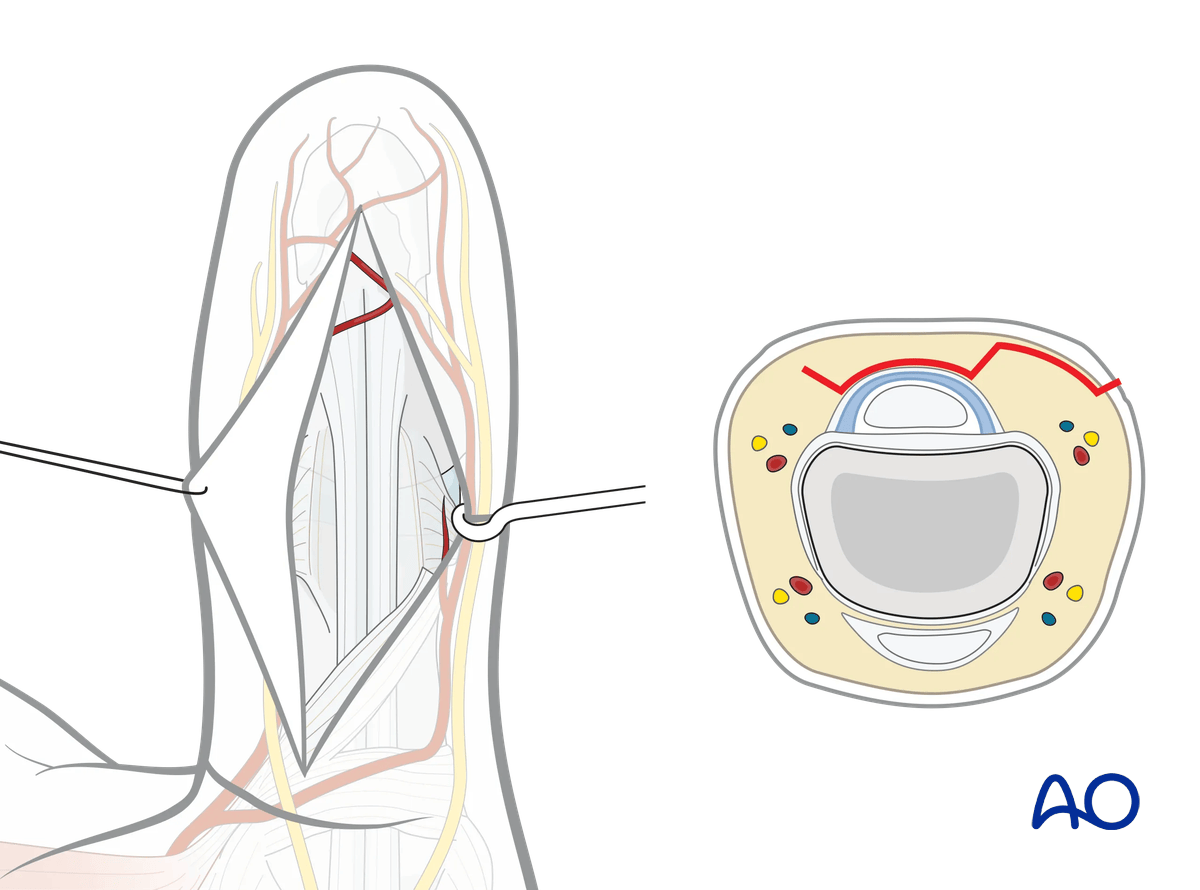
Make a carefully planned palmar angled skin incision (Bruner zigzag), using the flexor skin crease as a guide, as illustrated. The apex of the angle should be at the distal flexor crease, level with the IP joint.
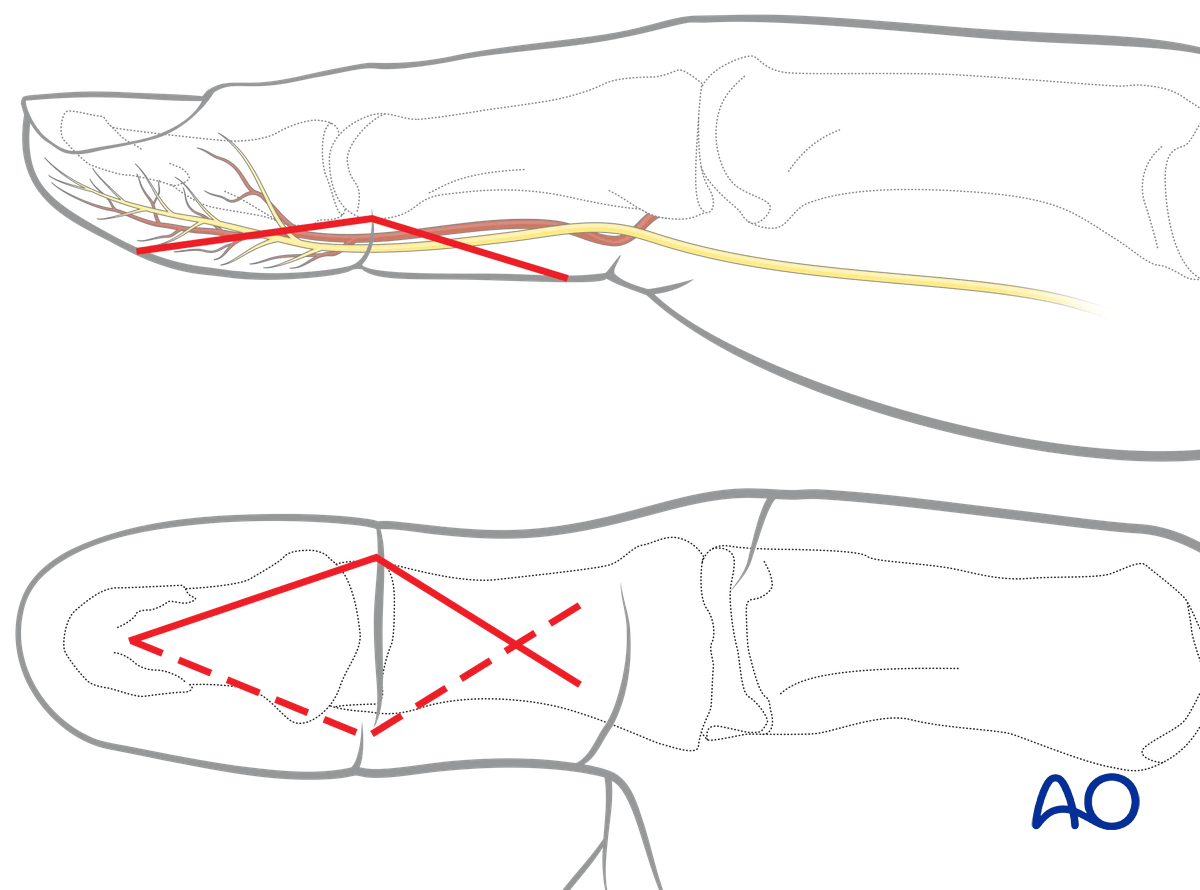
Elevate the angled skin flap by sharp dissection in the thin subcutaneous tissue and retract the apex. Identify and carefully mobilize the digital arteries and nerves within the skin and subcutaneous fascial flaps.
The flexor pollicis longus tendon and the oblique and A2 pulleys are now visible.
4. Further dissection
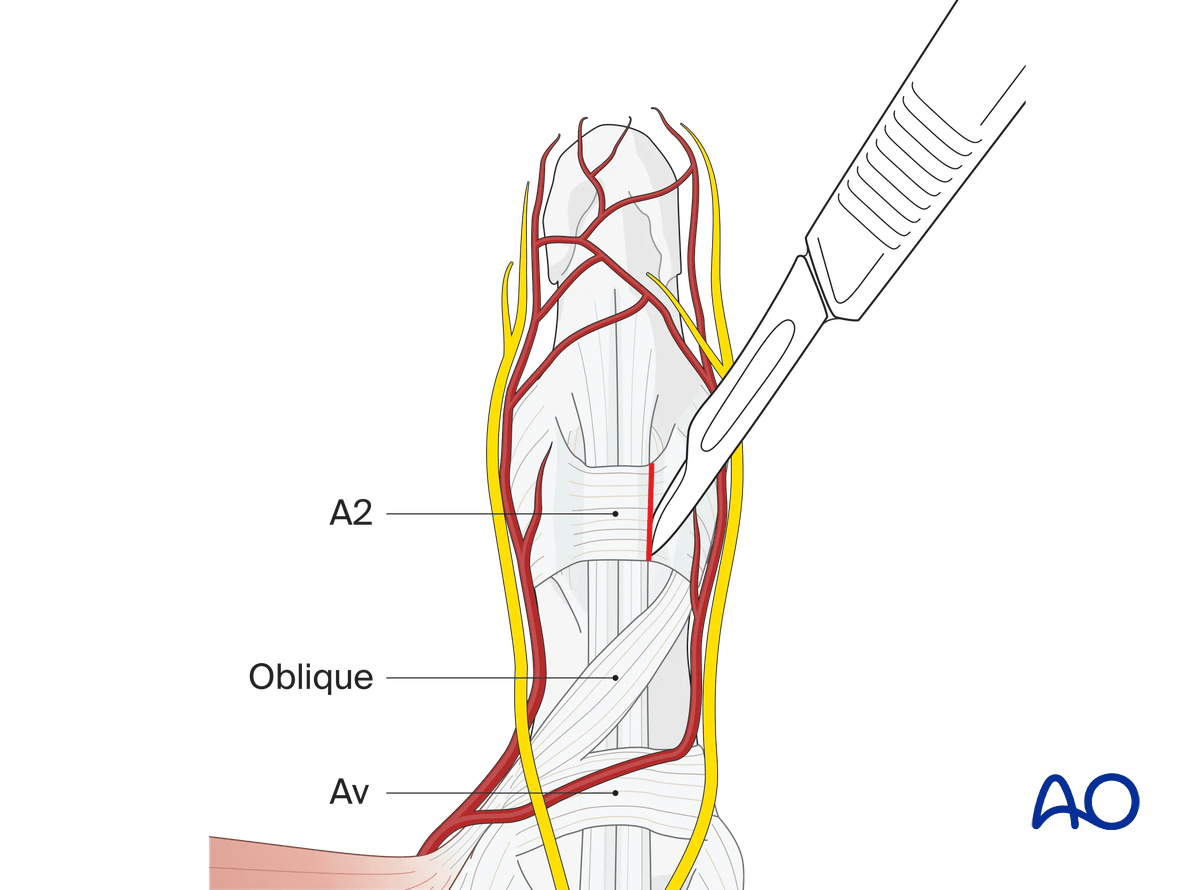
Make a blunt dissection of the pulp.
Divide the A2 pulley laterally near its bony attachment, leaving enough for later reattachment (at least 2 mm).
5. Elevation of the pulley flap
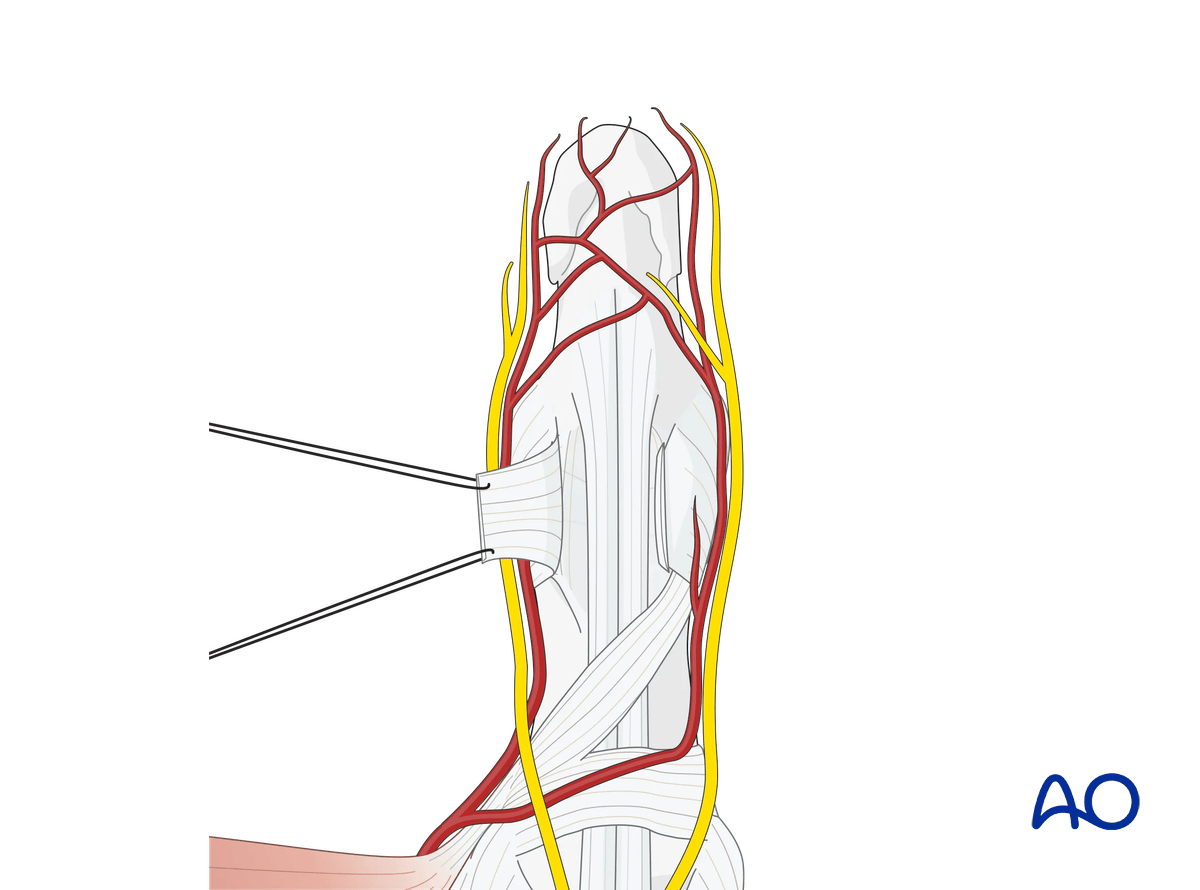
Elevate the pulley flap and retract it to expose the flexor tendon. By retraction of the tendon, the palmar aspect of the IP joint and the distal phalanx is exposed.
6. Wound closure
Reattach the A2 pulley using fine mattress sutures before skin closure.
Alternatively, the A2 pulley can be left unrepaired as it does not contribute significantly to the control of thumb flexion. This also avoids additional scarring.
Close the skin in a standard manner.