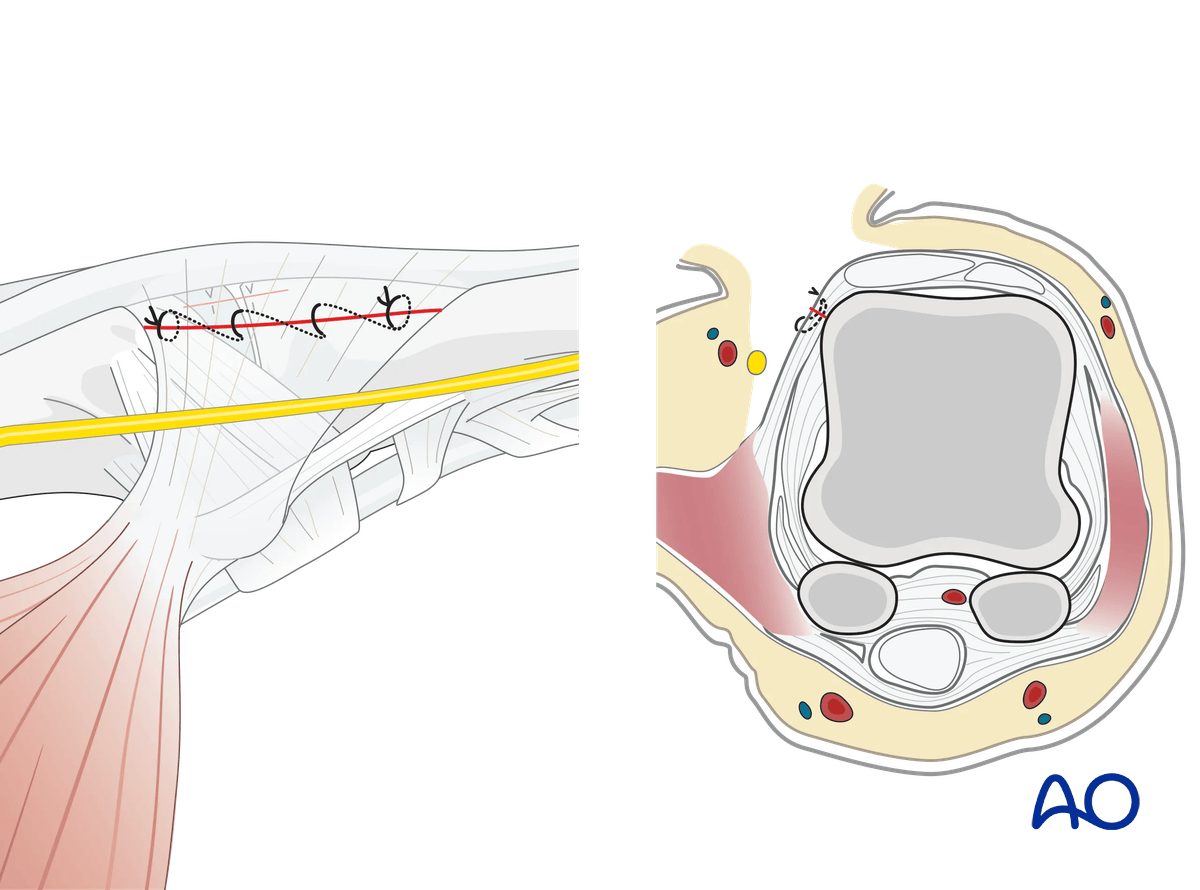
Dorsoulnar approach to the metacarpophalangeal joint of the thumb
1. Indications
This approach is indicated for:
- Intraarticular fractures of the ulnar margin of the head of the first metacarpal
- Intraarticular fractures of the base of the proximal phalanx
- Avulsion fractures of the base of the proximal phalanx
- Avulsion of the attachment of the ulnar collateral ligament to the base of the proximal phalanx of the thumb (Stener’s lesion, “gamekeeper’s thumb”, or “skier’s thumb”).
2. Surgical anatomy
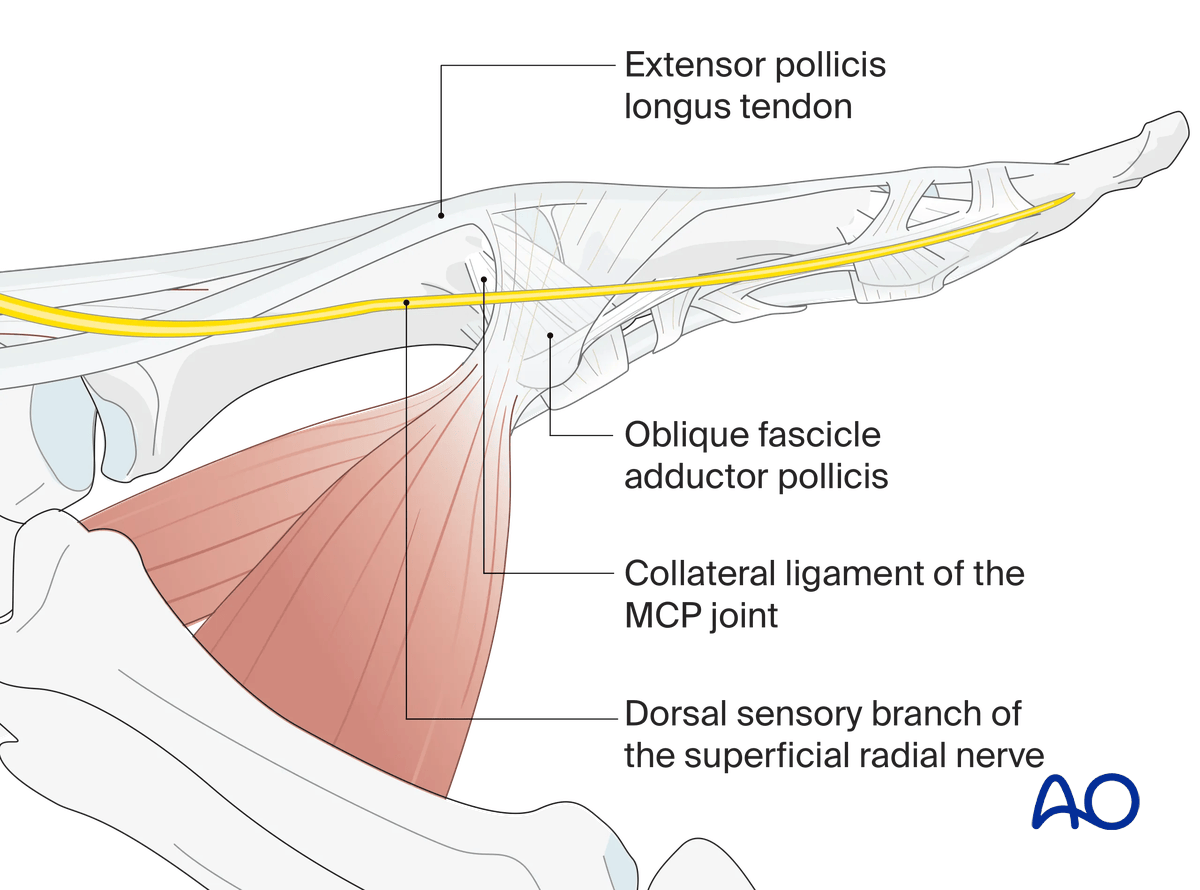
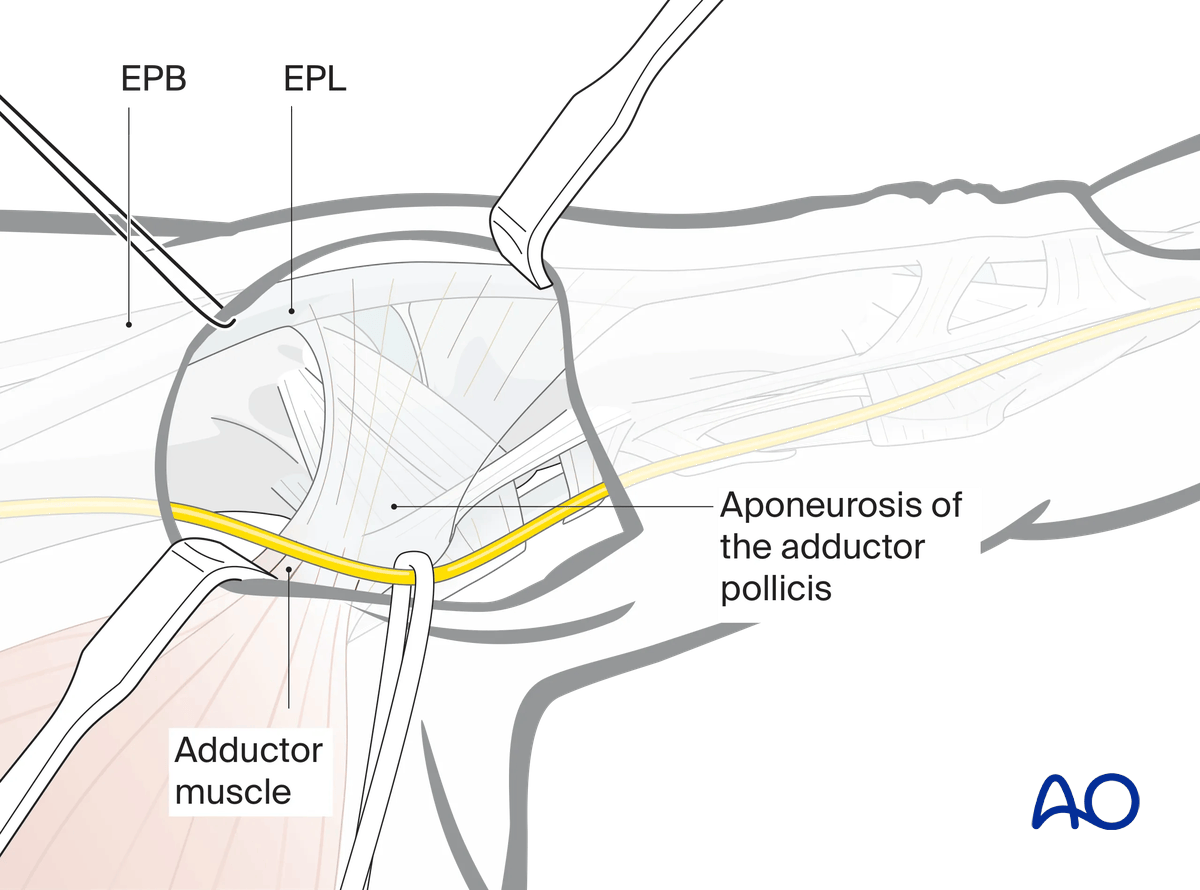
The transverse and oblique fibers of the adductor pollicis aponeurosis , insert into the extensor hood of the thumb on the ulnar aspect of the metacarpophalangeal (MCP) joint The ulnar collateral ligament is deep to the aponeurosis.
3. Skin incision
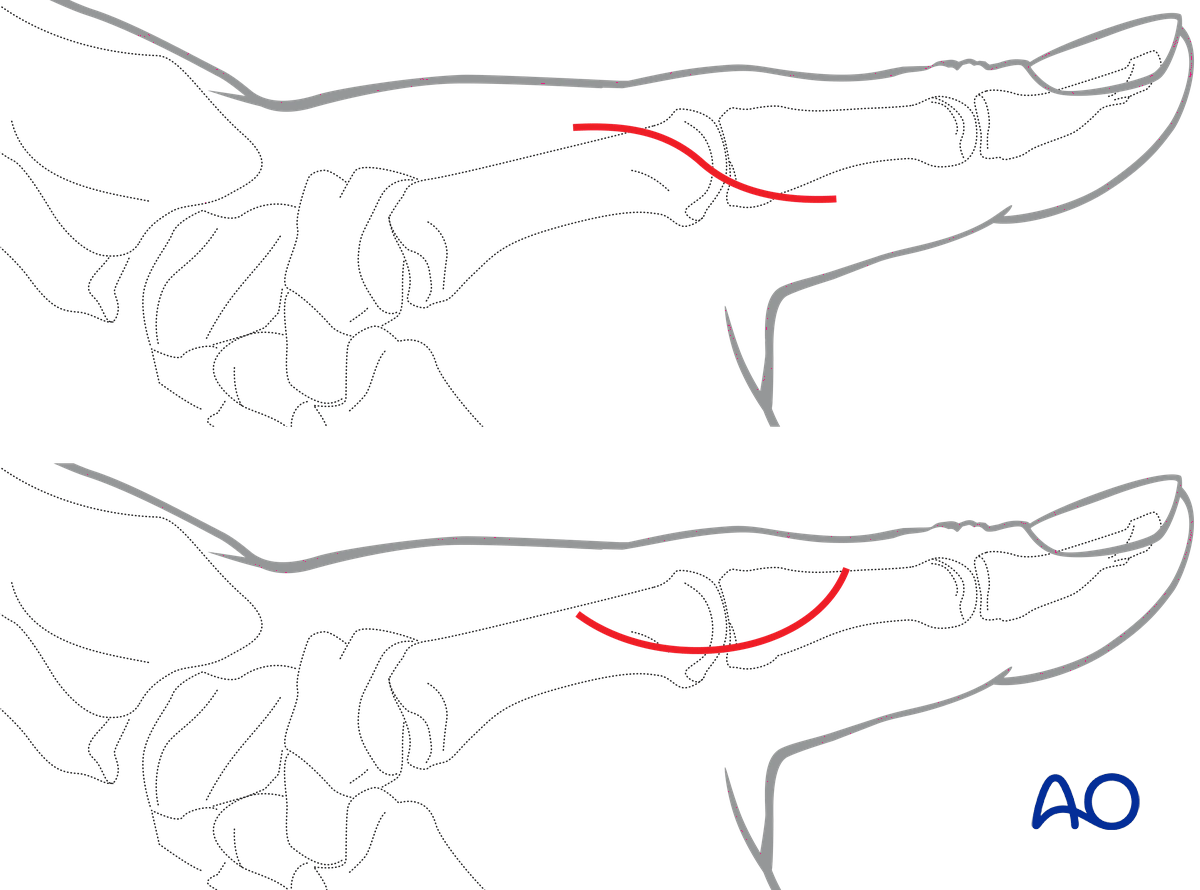
An incision starting dorsally, about 2 cm proximal to the MCP joint is extended in a palmar direction around the ulnar aspect of the joint, to about 1 cm distal to the joint.
Either a ‘lazy-S’ or curved incision may be used.
4. Identifying the structures
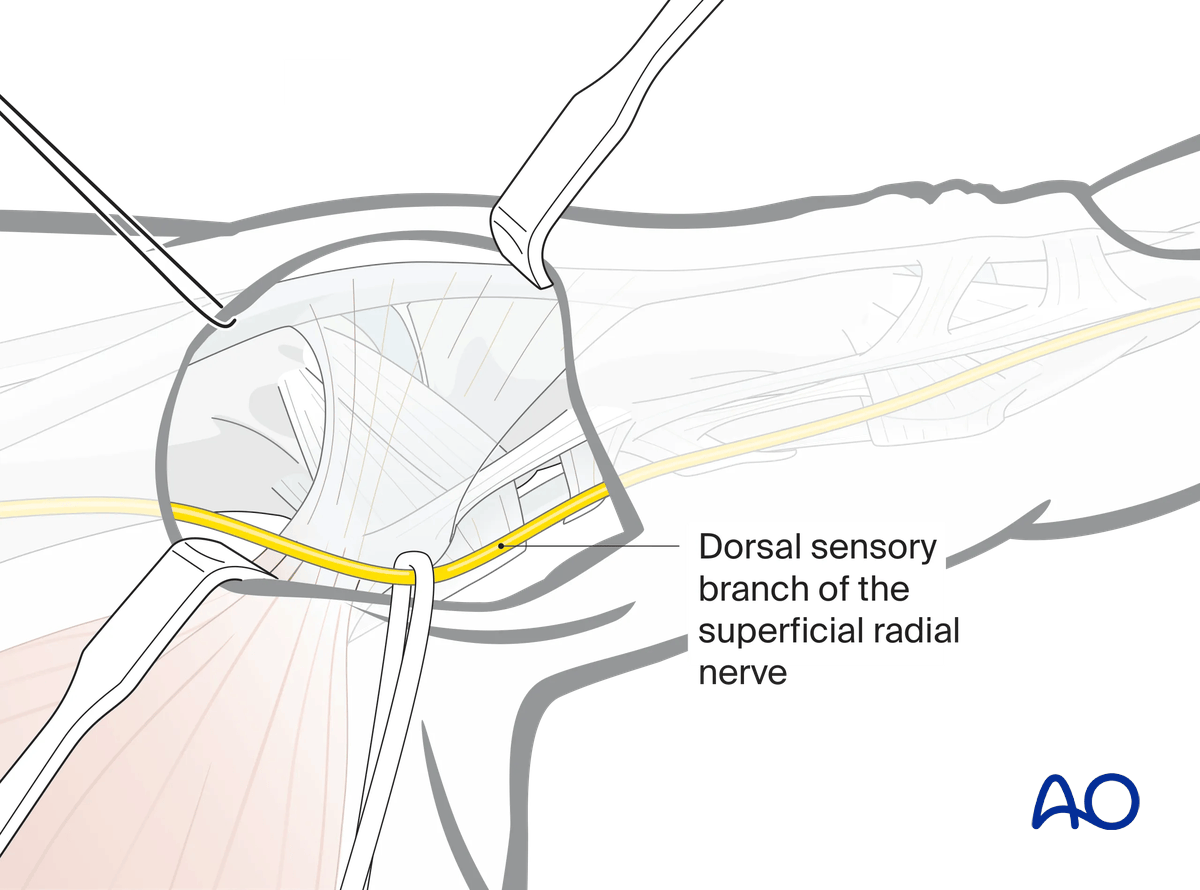
Identify and mobilize the divisions of the dorsoulnar sensory branch of the superficial radial nerve. A vessel loop may be used to protect the nerve.
Retract the nerve in either the palmar or dorsal direction.
Palmar retraction of the nerve facilitates optimal protection of the nerve by division and retraction of the aponeurosis of the adductor pollicis (if this is otherwise indicated).
Identify the adductor pollicis muscle with its aponeurosis, as well as the tendons of the extensor pollicis longus (EPL) and extensor pollicis brevis (EPB).
5. Division of the adductor aponeurosis
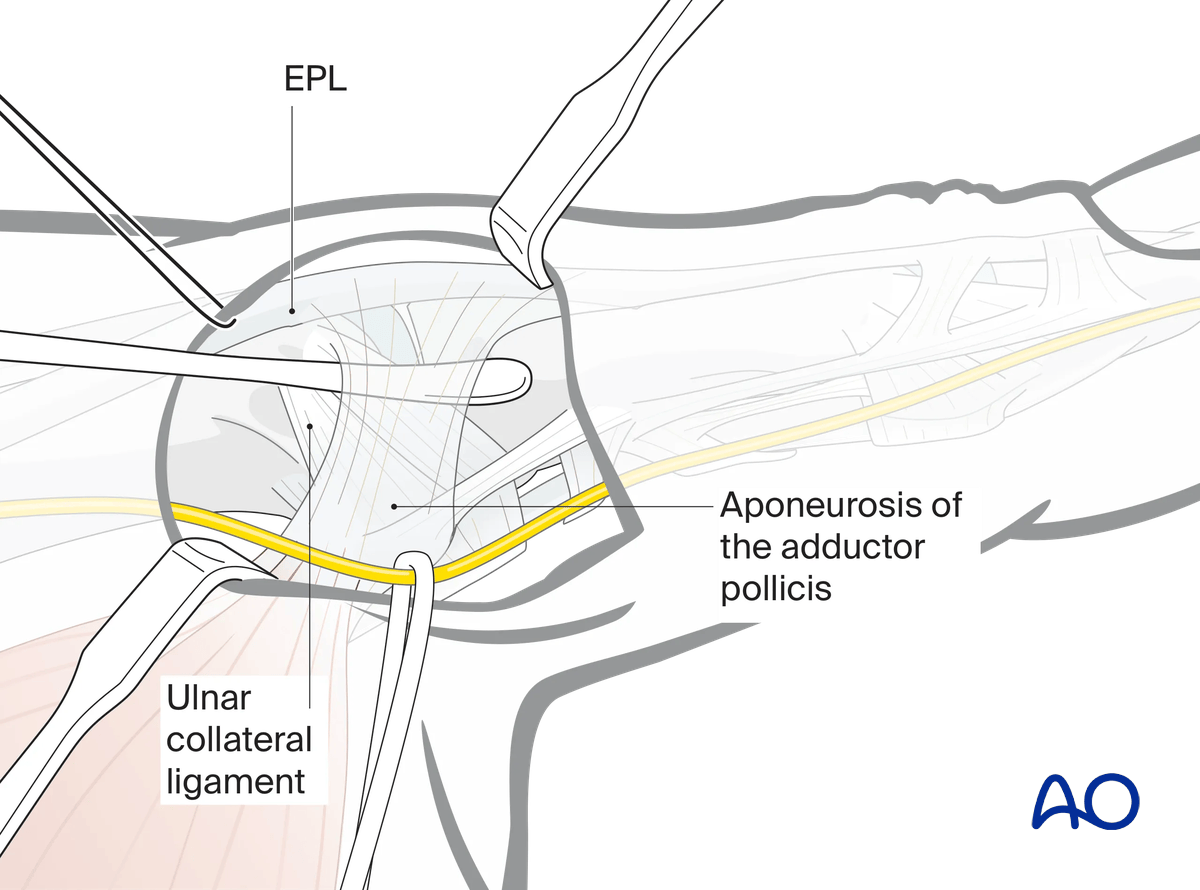
Elevation of the aponeurosis
Insert a dissector deep to the aponeurosis of the adductor pollicis longus (APL) between it and the ulnar collateral ligament and dorsal capsule.
This protects the underlying structures when the adductor aponeurosis is divided.
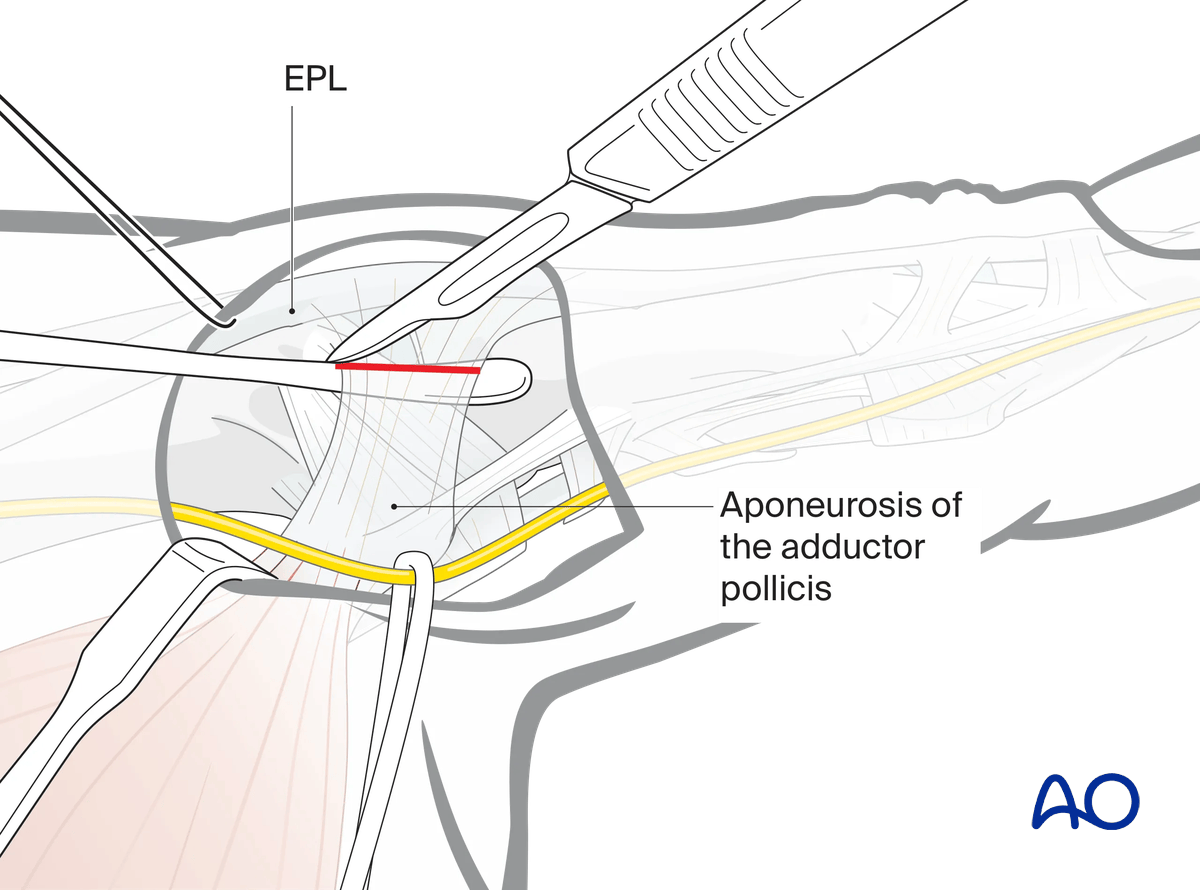
Dissection
Make a longitudinal incision to divide the adductor aponeurosis close to its insertion into the EPL tendon.
6. Exposure of the ulnar collateral ligament
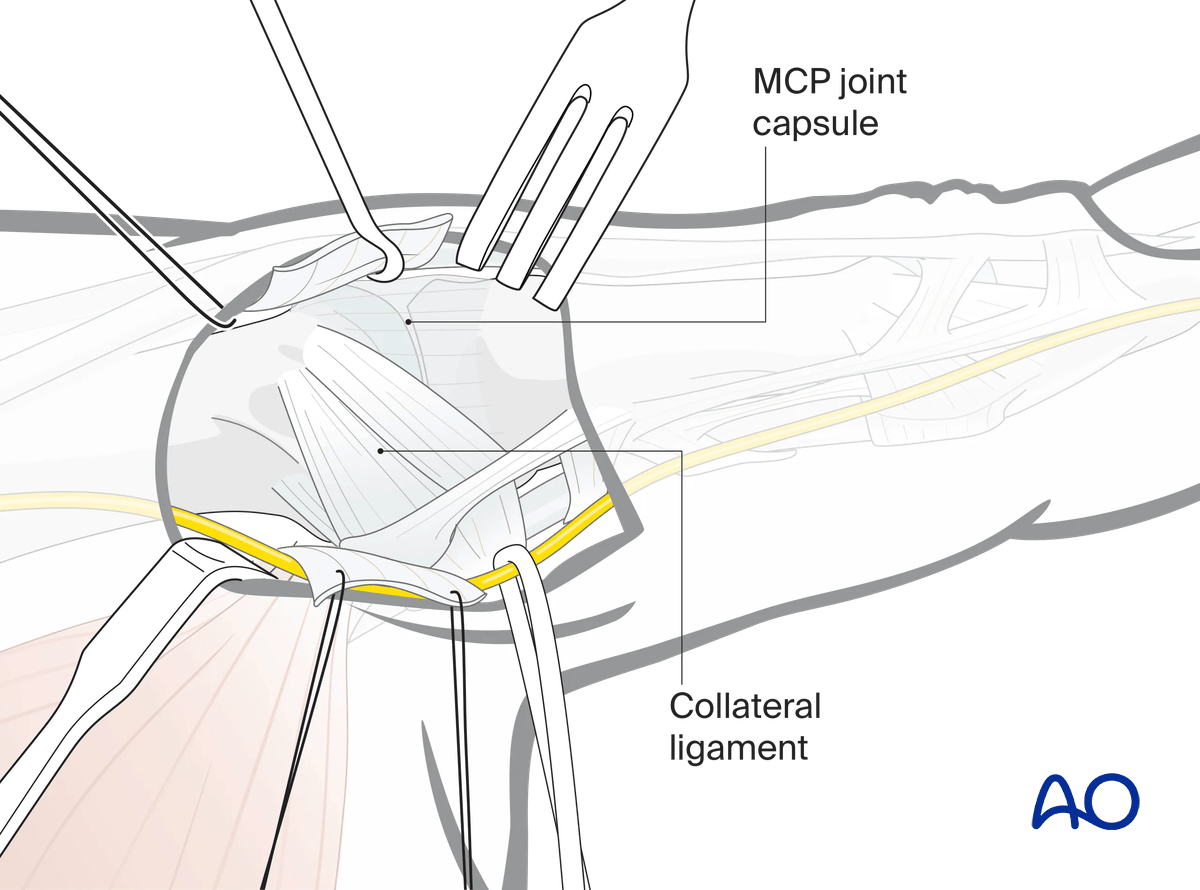
Retract the aponeurosis in a palmar direction using fine sutures, additionally protecting the dorsoulnar branch of the superficial radial nerve …
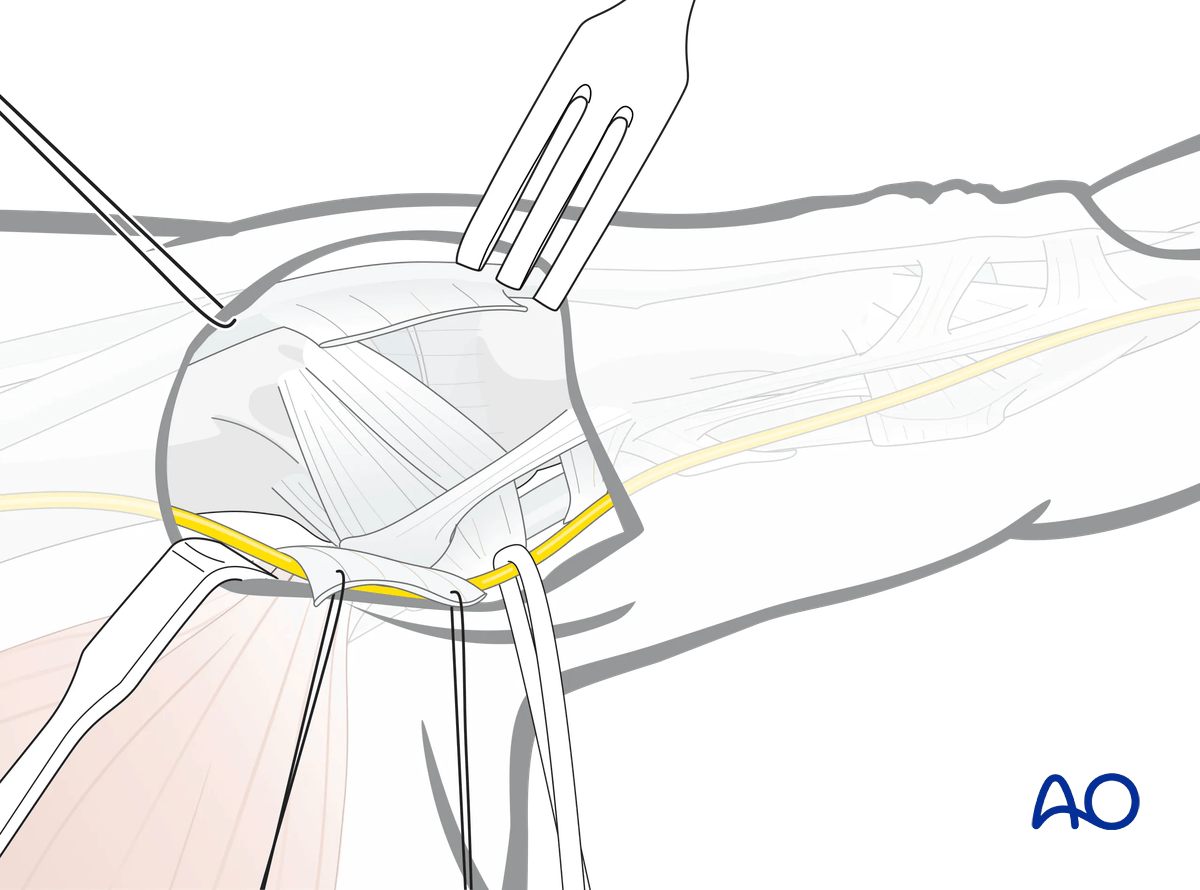
... and pull the EPL dorsally with a small retractor, exposing the ulnar collateral ligament and dorsal MCP joint capsule.
Pearl: aponeurosis flap for nerve protection
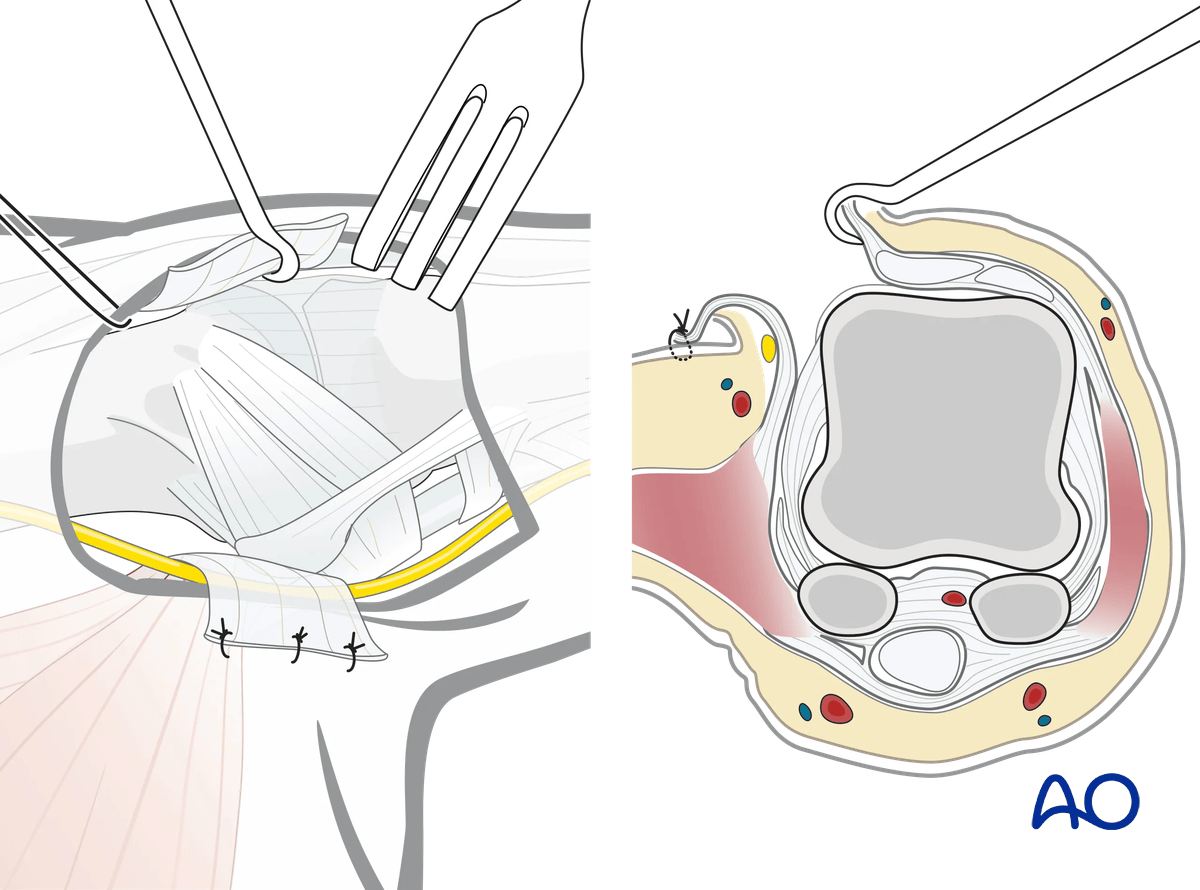
7. Capsulotomy
Make a longitudinal dorsal capsulotomy along the dorsal edge of the main collateral ligament, avoiding disinsertion of the proximal attachment of the collateral ligament into the metacarpal tubercle.
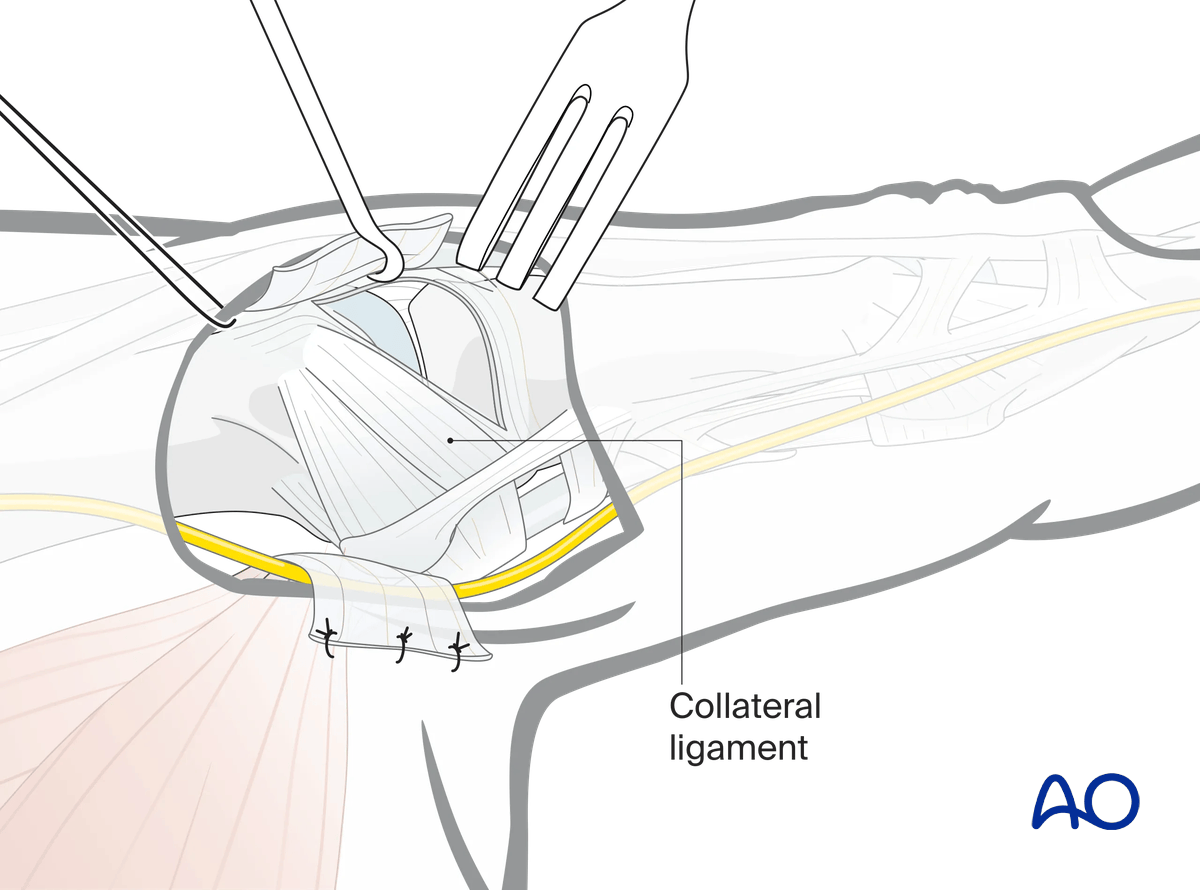
8. Wound closure
Close the capsule and then reattach the adductor aponeurosis using fine sutures (eg, PDS 4-0 or 5-0 either interrupted or uninterrupted).